

Loading, please wait...
Loading, please wait...

The clinical application of checkpoint blockade in mCRPC continues to present significant challenges for oncologists worldwide. Historically, investigators believed that androgen deprivation therapy uniformly invigorates antitumor immunity. Consequently, early studies hypothesized that suppressing androgen receptor activity would automatically convert immunologically cold prostate tumors into responsive phenotypes. However, extensive clinical trials have contradicted this oversimplified assumption. While androgen receptor signaling undeniably intersects with immune surveillance, the biological consequences remain highly context-dependent. Modern translational research reveals that androgen ablation alters tumor antigen visibility, thymic output, and peripheral T-cell trafficking. Nevertheless, these dynamic shifts fail to produce sustained clinical responses in unselected patient cohorts. Instead, therapeutic androgen blockade induces complex cellular adaptations across distinct anatomic compartments. Furthermore, systemic hormonal suppression frequently activates alternative immunosuppressive pathways within metastatic sites. Therefore, clinicians must reevaluate the traditional paradigm of prostate cancer immunology. Rather than viewing hormonal manipulation as a universal immunotherapy sensitizer, practitioners should appreciate the heterogeneous tumor-immune states that emerge during disease progression. This conceptual shift provides a rational framework to guide future clinical investigations. Specifically, deciphering how androgen receptor signaling interacts with local immune cellularity will uncover why single-agent checkpoint inhibitors fail in advanced disease.
Androgen receptor-directed therapy triggers profound remodeling across diverse cellular compartments in metastatic prostate cancer. When clinicians initiate potent antiandrogen therapy, initial suppression of androgen receptor signaling temporarily enhances cytotoxic T-cell infiltration. However, this transient inflammatory influx rarely translates into tumor eradication. Instead, the surrounding stroma mounts powerful counter-regulatory mechanisms that enforce profound immune exclusion. For instance, cancer-associated fibroblasts continuously secrete dense extracellular matrix proteins and profibrotic factors that physically restrict lymphocyte penetration. Concurrently, suppressive myeloid-derived suppressor cells and tumor-associated macrophages infiltrate metastatic bone and visceral niches. These myeloid populations actively produce immunosuppressive cytokines, including interleukin-6 and transforming growth factor-beta, alongside inhibitory metabolites like adenosine. Moreover, persistent metabolic stress within the tumor microenvironment promotes severe cytotoxic T-cell exhaustion and functional paralysis. Simultaneously, surviving prostate cancer clones exploit alternative survival pathways to restore androgen receptor transcription or bypass hormonal control entirely. Consequently, the tumor microenvironment rapidly transitions from a permissive inflammatory state into a calcified, immunologically hostile sanctuary. Therefore, therapy-induced remodeling establishes a resilient protective shield that neutralizes checkpoint blockade efficacy and facilitates ongoing disease progression.
Over the past decade, numerous randomized phase III trials evaluated checkpoint inhibitors across broad patient cohorts with metastatic castration-resistant prostate cancer. Clinical researchers combined programmed death-1 or programmed death-ligand 1 inhibitors with next-generation androgen receptor pathway inhibitors, poly(ADP-ribose) polymerase inhibitors, and cytotoxic taxane chemotherapy. Unfortunately, these large combination trials repeatedly failed to demonstrate significant improvements in overall survival compared with standard-of-care regimens. Furthermore, dual-checkpoint blockade combining anti-PD-1 and anti-CTLA-4 antibodies produced only modest response rates while inducing substantial immune-related adverse events. These disappointing outcomes definitively demonstrate that empirical immunotherapy combinations cannot overcome intrinsic prostate cancer resistance in unselected populations. Mechanistically, metastatic prostate cancer exhibits a remarkably low baseline tumor mutational burden and minimal human leukocyte antigen class I expression. As a result, endogenous cytotoxic T cells fail to recognize somatic neoantigens effectively. Additionally, dominant non-redundant suppressive pathways operate simultaneously within metastatic niches, rendering single-agent or dual-agent checkpoint inhibition insufficient. Thus, continuing to conduct empirical phase III combination studies without precise biological stratification wastes valuable clinical resources. Instead, oncology teams must embrace prospective biomarker selection to identify the small subset of patients who genuinely benefit from immune checkpoint modulation.
Amid repeated clinical trial setbacks, genomic precision medicine has revealed an essential exception in metastatic prostate cancer management. Currently, deficient mismatch repair and microsatellite instability-high (dMMR/MSI-H) status represents the only clinically validated predictive biomarker for checkpoint inhibitor therapy. Pathogenic alterations in mismatch repair genes, including MSH2, MSH6, MLH1, and PMS2, disrupt genomic proofreading during replication. Consequently, these tumors accumulate thousands of somatic insertions and deletions, dramatically elevating the overall neoantigen repertoire. When clinicians administer pembrolizumab to patients harboring dMMR/MSI-H tumors, durable radiographic and prostate-specific antigen responses frequently occur. However, this distinct hypermutated subset accounts for only two to three percent of all metastatic castration-resistant prostate cancer cases. Therefore, oncologists in routine clinical practice must implement comprehensive genomic sequencing or immunohistochemical screening to identify these rare individuals early. In contrast, unselected patients lacking mismatch repair deficiency derive virtually no meaningful survival advantage from checkpoint inhibition. Ultimately, dMMR/MSI-H validation confirms that checkpoint inhibitors require abundant pre-existing neoantigens to stimulate functional antitumor T cells. Clinicians must strictly reserve standard checkpoint blockade for patients with documented mismatch repair defects or confirmed hypermutation.
Beyond mismatch repair deficiency, investigators have evaluated multiple candidate biomarkers with disappointing results. For example, cyclin-dependent kinase 12 mutations, homologous recombination repair alterations, isolated programmed death-ligand 1 expression, and androgen receptor splice variant 7 do not independently predict checkpoint inhibitor efficacy. Although CDK12 inactivation generates gene fusions and neoepitopes, clinical responses remain inconsistent in prospective cohorts. Similarly, composite transcriptomic signatures and isolated high tumor mutational burden cutoffs lack rigorous prospective validation. Consequently, therapeutic innovation has pivoted toward bispecific T-cell engagers to circumvent natural immune presentation barriers. Bispecific antibodies simultaneously bind prostate-specific membrane antigen or six-transmembrane epithelial antigen of the prostate 1 alongside CD3 on T cells. By physically crosslinking cytotoxic lymphocytes to malignant cells, T-cell engagers trigger targeted lysis independent of human leukocyte antigen presentation. Early clinical studies demonstrate rapid radiographic responses and steep prostate-specific antigen declines in heavily pretreated populations. Nevertheless, these novel constructs introduce serious clinical complications, particularly severe cytokine release syndrome and immune effector cell-associated neurotoxicity. Furthermore, marked target antigen heterogeneity and transient response durations present ongoing translational hurdles. Accordingly, definitive phase III trials must balance clinical potency against treatment-related toxicities before widespread adoption occurs.
Checkpoint inhibitors fail in most metastatic prostate cancers because these tumors present an immunologically cold microenvironment. Prostate neoplasms typically carry a low tumor mutational burden and produce few recognizable neoantigens. Furthermore, dense cancer-associated fibroblasts, immunosuppressive myeloid cells, and anti-inflammatory cytokines actively exclude cytotoxic lymphocytes from metastatic niches. Consequently, releasing inhibitory immune checkpoints does not overcome the profound physical exclusion and multi-layered cellular immunosuppression operating within advanced tumors.
Currently, deficient mismatch repair or microsatellite instability-high (dMMR/MSI-H) status represents the sole clinically validated predictive biomarker for checkpoint blockade in mCRPC. Defective mismatch repair enzymes generate extensive frameshift mutations and abundant neoantigens, rendering tumors sensitive to anti-PD-1 antibodies like pembrolizumab. Although this phenotype occurs in only two to three percent of advanced cases, universal genomic sequencing ensures timely identification of eligible candidates.
Bispecific T-cell engagers bypass major histocompatibility complex restriction, but they carry substantial clinical toxicities. Specifically, rapid systemic lymphocyte activation frequently triggers cytokine release syndrome, causing high fever, hypotension, and potential neurotoxicity. Furthermore, heterogeneous expression of target surface antigens like prostate-specific membrane antigen allows resistant tumor clones to escape destruction. Consequently, ongoing clinical trials must optimize dosing schedules, mitigate systemic toxicities, and determine durable combination partners for patients.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





This clinical review details how androgen receptor signaling interacts with tumor immunity in mCRPC, why phase III immunotherapy combinations failed, and why dMMR/MSI-H remains the sole validated biomarker for checkpoint blockade.
Today
Novel BRET biosensors reveal how common environmental toxicants, including the herbicide paraquat and food additive BHT, disrupt mitochondrial protein localization. This breakthrough provides new molecular insights into cellular stress, organ failure, and metabolic disease mechanisms.
Today
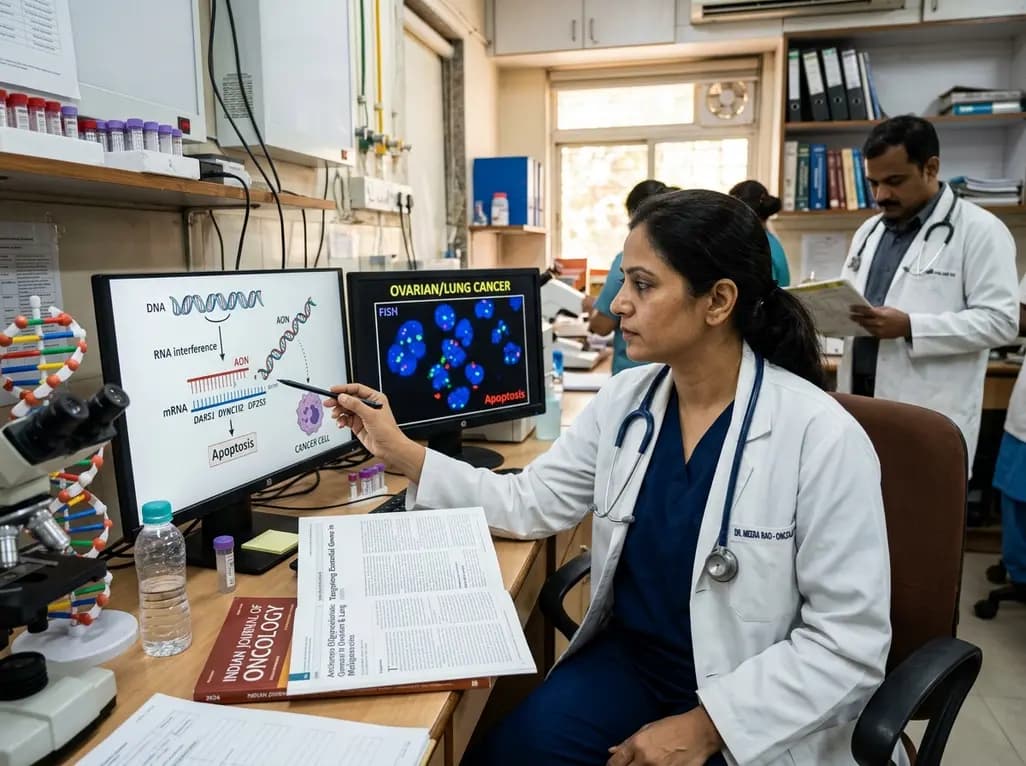
Novel preclinical research demonstrates that antisense oligonucleotides targeting essential genes such as DARS1, DYNC1I2, and EIF2S3 selectively induce apoptosis in ovarian and lung cancer cells. Conditional biomarker activation provides a viable strategy to spare normal tissue while overcoming therapy resistance.
Today

This clinical analysis examines heparin-free versus heparin-containing Impella purge solutions in patients receiving concomitant ECMO support (ECPELLA). Evidence suggests anticoagulant-free purges maintain device patency while reducing bleeding risks, offering a viable strategy alongside systemic anticoagulation.
Today

A 10-year Markov state-transition model shows minimally invasive tubular decompression dominates open laminectomy for pure lumbar spinal stenosis, yielding 5.95 vs 5.91 QALYs and saving $4,167 per patient through reduced complications and lower index costs.
Today

A preclinical study demonstrates that naringin-loaded phytosomes significantly enhance oral bioavailability and provide neuroprotective efficacy in diabetic neuropathy by dampening inflammation, reducing oxidative stress, and relieving neuropathic pain.
Today
