

Loading, please wait...
Loading, please wait...

Clinicians treating refractory epilepsy are increasingly turning to cenobamate as an effective add-on therapy. However, managing Cenobamate pharmacokinetic interactions requires careful attention due to the significant variability observed in clinical settings. A recent observational study at the National Center for Epilepsy analyzed over 600 serum measurements to map these patterns. The researchers discovered a striking 34-fold interpatient variability in concentration-to-dose ratios. Although the intraindividual variation remains moderate at 18%, the presence of comedications significantly alters drug exposure. For example, strong enzyme inducers can reduce serum levels by 9%, while enzyme inhibitors may increase them by 14%.
The study highlights complex two-way Cenobamate pharmacokinetic interactions that affect several common antiseizure medications. Specifically, adding cenobamate to a regimen containing clobazam leads to a 115% increase in N-desmethylclobazam, the active metabolite of clobazam. This substantial rise often triggers adverse events like severe somnolence, necessitating proactive dose reductions. Furthermore, cenobamate appears to induce the metabolism of other drugs. Results showed that carbamazepine concentrations dropped by 14%, and valproate levels decreased by 10%. Consequently, therapeutic drug monitoring (TDM) serves as an essential tool to maintain the delicate balance between efficacy and toxicity during titration.
Physicians should adopt a personalized approach when prescribing cenobamate for adults with focal-onset seizures. Because the drug exhibits non-linear pharmacokinetics, small dose adjustments can lead to disproportionate changes in serum levels. Moreover, the influence of gender and age must be considered, as women often show higher exposure levels than men. Therefore, clinicians must monitor patients closely during every titration step. Additionally, regular blood tests help in identifying early signs of drug accumulation. By integrating TDM into routine practice, neurologists can better navigate the pharmacological complexities of modern epilepsy treatment.
Cenobamate inhibits the CYP2C19 enzyme, which is responsible for breaking down N-desmethylclobazam, the active metabolite of clobazam. This interaction can cause a 115% increase in metabolite levels, often leading to increased sedation and requiring a dose reduction of clobazam.
The study found a 34-fold interpatient variability, meaning different patients may have vastly different blood levels on the same dose. This highlight makes therapeutic drug monitoring crucial for ensuring each patient receives a safe and effective dose.
Yes, cenobamate can induce the metabolism of carbamazepine, leading to an average reduction of 14% in its serum concentration. Clinicians may need to adjust the carbamazepine dose to maintain seizure control.
Disclaimer: This content is for informational and educational purposes only. It does not constitute medical advice, diagnosis, or treatment. Always seek the advice of a qualified healthcare provider with any questions regarding a medical condition. Refer to the latest local and national guidelines for clinical practice.
References
Johannessen Landmark C et al. Pharmacokinetic variability and complex two-way interactions with cenobamate in patients with refractory epilepsy. Epilepsia. 2026 Mar 24. doi: 10.1002/epi.70184. PMID: 41874535.
Roberti R et al. Critical Appraisal of Cenobamate as Adjunctive Treatment of Focal Seizures in Adults. Pharmaceuticals (Basel). 2021;14(12):1241.
Gidal BE et al. Dose Adjustment of Concomitant Antiseizure Medications During Cenobamate Treatment: Expert Opinion Consensus Recommendations. Neurol Ther. 2021;10(2):495-515.
"
Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A study reveals cenobamate's 34-fold interpatient variability and its 115% increase of clobazam's active metabolite, necessitating close monitoring....
6 months ago
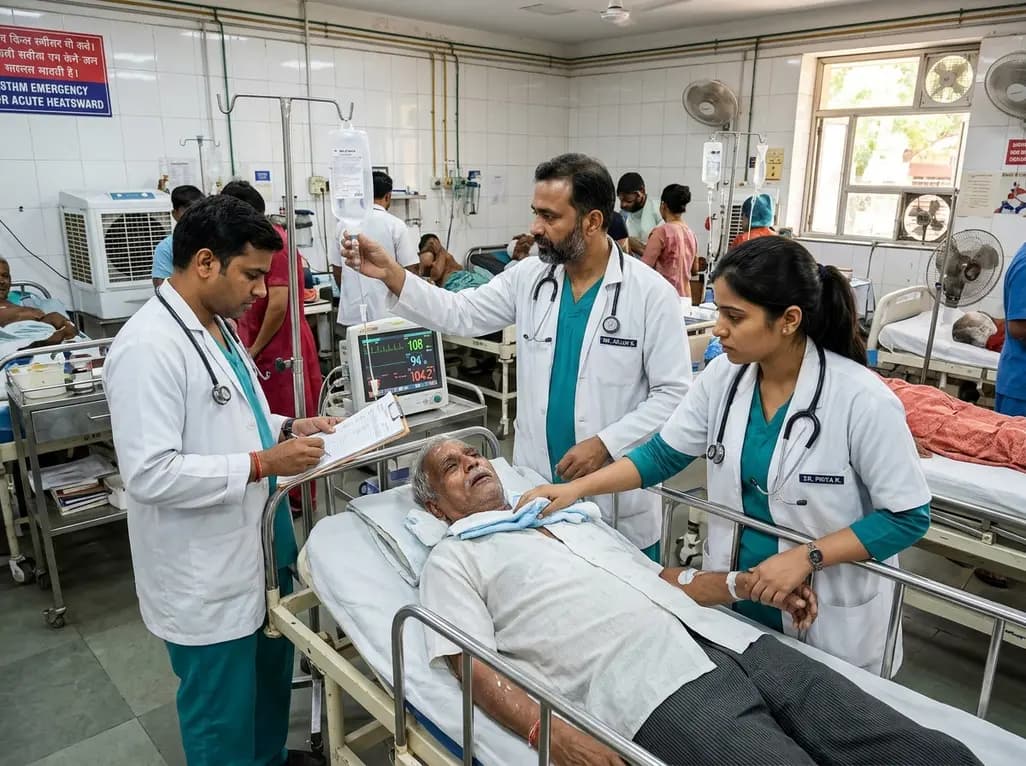
Recent epidemiological data reveals a dramatic surge in summer heat mortality driven by human-induced climate warming. This analysis explores the pathophysiological impacts on cardiac and renal systems, diagnostic dilemmas in death certification, and essential emergency cooling protocols for acute clinical care.
Today

Odisha has established India's first state-level clinical protocol specifically tailored for pregnant women with sickle cell disease. Developed with NHM and UNICEF, the framework provides structured antenatal screening, crisis mitigation, standardized referral pathways, and specialized interdisciplinary care.
Today

India is advancing preventive healthcare by integrating genomics, artificial intelligence, and quantum technologies. With the SANGAM programme sequencing one million Indian genomes, clinicians can unlock personalized therapies, detect cardiometabolic risks early, and curb the burden of diabetes and heart disease.
Today

A randomized controlled trial demonstrates that an eight-week dual-task training intervention significantly improves static and dynamic postural control over standard balance exercises in individuals with chronic ankle instability, addressing critical neurocognitive deficits during athletic and daily activities.
Today

A retrospective cohort study of 7,716 ICU patients from the MIMIC-IV database demonstrates that Gradient Boosting Decision Trees significantly outperform traditional SOFA scores in predicting in-hospital mortality among patients with sepsis and diabetes, with SHAP analysis providing clinical interpretability.
Today
