

Loading, please wait...
Loading, please wait...

Type 2 diabetes mellitus presents a multifaceted clinical challenge characterized by chronic metabolic disturbances and progressive musculoskeletal decline. Clinicians frequently track glycemic parameters, yet they often overlook the severe degradation of physical performance in daily practice. Recent investigations highlight that elevated body mass index compromises musculoskeletal integrity, walking endurance, and overall functional capacity in diabetes. Consequently, excess adiposity accelerates muscle loss and impairs postural stability. Therefore, comprehensive patient care requires evaluating metabolic control alongside physical functioning.
Excess body weight exerts a substantial mechanical and metabolic burden on skeletal muscle. In type 2 diabetes, adipose tissue expansion promotes systemic low-grade inflammation through elevated pro-inflammatory cytokines. Consequently, this persistent inflammatory milieu accelerates myosteatosis and impairs protein synthesis. Although heavier patients display larger limb circumference, their relative muscle strength declines significantly. This clinical condition, termed sarcopenic obesity, impairs neuromuscular coordination and normalized power output.
Furthermore, mechanical loading from excess adiposity increases the energetic cost of simple physical tasks. Patients quickly experience premature exhaustion during locomotion, which encourages sedentary habits and exacerbates functional loss. In addition, peripheral insulin resistance blunts glucose delivery to myocytes, diminishing mitochondrial energy production. Therefore, clinicians must recognize that elevated body weight directly compromises functional capacity in diabetes through biological and biomechanical mechanisms.
Clinical investigations demonstrate a strong inverse correlation between body mass index and skeletal muscle percentage in diabetic cohorts. Specifically, researchers observe that elevated adiposity correlates with reduced handgrip strength, an established surrogate marker of global muscle vitality. While absolute quadriceps torque may appear stable due to weight-bearing stimulation, relative muscle quality drops sharply. Intramuscular lipid deposition disrupts force generation per unit of muscle area.
Moreover, diabetic microvascular disease and neuropathy impair motor unit recruitment, exacerbating upper-limb weakness. As a result, patients struggle with fundamental self-care tasks, including blood glucose testing and medication delivery. Consequently, handgrip dynamometry represents an accessible, cost-effective screening tool for clinical practice. Routine measurement allows physicians to detect occult functional decline early. Therefore, healthcare providers should incorporate grip strength assessment into standard diabetes management.
Elevated adiposity profoundly degrades ambulatory endurance and cardiorespiratory fitness in diabetic individuals. Specifically, objective evaluations utilizing the six-minute walk test demonstrate that patients with high body mass index achieve significantly shorter distances. Excess body weight increases the mechanical work of walking while blunting oxygen utilization efficiency. Furthermore, subclinical cardiovascular stiffness restricts cardiac output responsiveness during sustained physical exertion.
Consequently, affected individuals experience early dyspnea, leg fatigue, and joint pain during ordinary locomotion. This functional limitation triggers a vicious cycle of physical inactivity, leading to worsening glycemic control and weight gain. In addition, altered gait biomechanics accelerate degenerative knee and hip osteoarthritis. Therefore, clinicians must incorporate objective exercise tolerance testing rather than relying solely on subjective patient recall.
Postural control represents another crucial physiological domain that deteriorates as body mass index rises. Clinical assessments utilizing the Berg Balance Scale show that obese diabetic individuals exhibit marked postural instability. Excess abdominal mass shifts the center of gravity anteriorly, demanding greater corrective joint torque. Furthermore, diabetic sensorimotor polyneuropathy blunts somatosensory feedback from plantar mechanoreceptors, impairing balance preservation.
Simultaneously, visual and vestibular mechanisms struggle to compensate for impaired proprioception under higher biomechanical inertia. As a result, patients demonstrate increased postural sway and delayed muscular responses to sudden perturbations. This combination of impaired sensory integration and relative weakness dramatically elevates fall risks. Therefore, routine clinical protocols should include balance evaluations to identify vulnerable patients and prevent traumatic injuries.
The cumulative biomechanical and metabolic complications of obesity severely diminish health-related quality of life. Chronic physical limitations prevent patients from participating in domestic, occupational, and social pursuits. Validated quality questionnaires reveal that physical functioning, vitality, and bodily pain subdomains suffer the greatest impairment. Furthermore, the daily burden of managing multiple medications alongside functional disability elevates diabetes-related psychological distress.
Moreover, chronic joint pain and sleep disturbances from comorbid obstructive sleep apnea cause persistent daytime exhaustion. Consequently, impaired psychological resilience diminishes treatment adherence and lifestyle compliance. Clinicians must therefore view functional capacity and emotional health as central therapeutic priorities. Implementing comprehensive psychosocial support empowers patients to manage diabetes and obesity more effectively.
Improving functional outcomes in diabetes demands an active therapeutic shift toward multidisciplinary physical rehabilitation. Healthcare providers must emphasize muscle preservation alongside safe adipose reduction. Although caloric restriction reduces body weight, unguided rapid weight loss can accelerate sarcopenia. Therefore, individualized medical nutrition therapy should supply adequate dietary protein distributed evenly across daily meals.
Additionally, structured exercise prescriptions should combine progressive resistance training with aerobic conditioning. Resistance workouts restore normalized muscle strength and promote glucose uptake, whereas aerobic exercise improves cardiorespiratory fitness. Furthermore, clinicians can utilize weight-neutral or weight-reducing antihyperglycemic therapies to support metabolic goals while protecting lean tissue. Collaborative care between physicians, physiotherapists, and dietitians ensures long-term physical independence and metabolic stability.
Elevated body mass index triggers chronic low-grade inflammation and intramyocellular lipid deposition within skeletal muscle. This process, known as myosteatosis, impairs myofibrillar contractile performance and cellular energy metabolism. Although absolute muscle mass might seem elevated in heavier individuals, relative force generation per unit of muscle tissue drops significantly. Consequently, patients with type 2 diabetes experience neuromuscular weakness and accelerated functional decline despite having larger body mass.
The six-minute walk test provides an objective, reliable assessment of functional exercise tolerance and cardiorespiratory capacity in daily life. In patients with type 2 diabetes, higher body mass index increases the energetic cost of ambulation, leading to premature fatigue and shorter walking distances. Furthermore, this validated test reflects integrated cardiovascular, respiratory, and neuromuscular functioning, enabling clinicians to monitor disease progression, evaluate rehabilitation efficacy, and identify individuals at elevated risk of functional disability.
A multimodal rehabilitation strategy combining progressive resistance training, core stabilization exercises, and dynamic balance re-education offers the greatest clinical benefit. Resistance exercises counteract sarcopenic muscle loss, whereas balance training enhances sensory integration and proprioception compromised by peripheral neuropathy. Additionally, clinicians should provide targeted dietary counseling emphasizing sufficient protein intake and weight management. This comprehensive intervention restores neuromuscular coordination, reduces fall risk, and significantly improves overall mobility and quality of life.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A cross-sectional study reveals that elevated BMI in type 2 diabetes correlates with reduced skeletal muscle mass, handgrip weakness, impaired walking capacity, balance deficits, and poor quality of life, highlighting the need for targeted rehabilitation.
Today

A Belgian study highlights maternal desires and healthcare provider perspectives on breastfeeding in women living with HIV. While viral suppression reduces transmission risk below 1%, significant clinical training and policy gaps remain, highlighting the urgent need for multidisciplinary counseling protocols.
Today
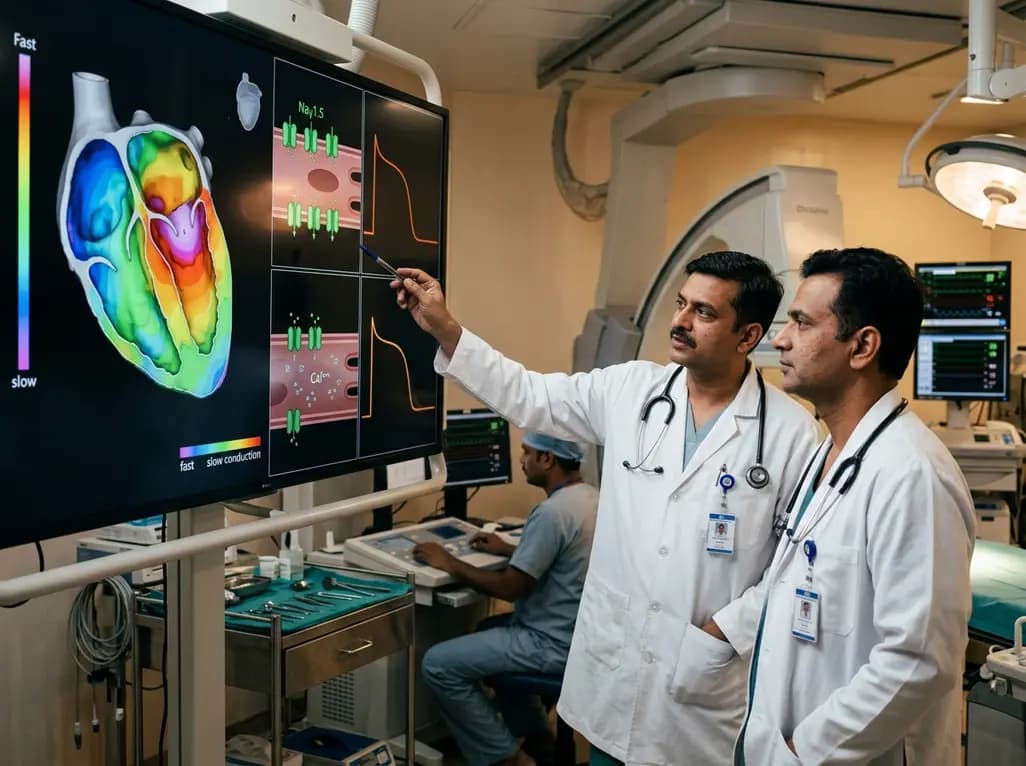
New research reveals that non-ablative radiotherapy suppresses ventricular tachycardia by increasing conduction velocity via NaV1.5 upregulation and action potential prolongation. However, sustained sodium current elevation and depressed calcium handling highlight the need for careful clinical translation.
Today

The ASAS core set defines mandatory domains and instruments for axial spondyloarthritis across routine and extended clinic visits, optimizing outpatient care and aligning treatment monitoring with international guidelines.
Today

A landmark randomized clinical trial demonstrates that real-time continuous glucose monitoring significantly reduces HbA1c and enhances time in range for individuals with type 2 diabetes who do not take insulin, paving the way for broader clinical adoption and personalized metabolic therapy in primary care.
Today
