

Loading, please wait...
Loading, please wait...

Many clinicians view sleep disturbances as secondary symptoms of active manic or depressive episodes. However, emerging clinical evidence demonstrates that bipolar disorder chronic insomnia represents an independent, debilitating condition. Sleep disruptions frequently persist during prolonged euthymic periods, placing substantial physiological strain on affected individuals. Chronic sleep deprivation destabilizes intrinsic circadian rhythms, impairs systemic homeostasis, and elevates cardiometabolic risks. Furthermore, persistent sleeplessness induces profound alterations across neuroendocrine, immune, and cellular pathways. Patients experience blunted stress hormone secretion, heightened inflammatory cytokines, and premature cellular aging that require targeted medical attention. Recognizing this condition as an autonomous clinical entity rather than a transient symptom transforms therapeutic priorities. Consequently, healthcare providers must investigate how prolonged sleep disruption compromises physiological resilience.
Sleep disruption in psychiatric populations has historically presented a complex diagnostic dilemma. Clinicians traditionally believed that resolving affective episodes would automatically restore healthy sleep patterns. Nevertheless, clinical investigations show that bipolar disorder chronic insomnia often persists for decades independently of mood stability. In matched cohorts, affected individuals reported an average insomnia duration exceeding twenty-two years. Furthermore, these patients demonstrated severe sleep fragmentation, prolonged sleep latency, and reduced sleep efficiency. Interestingly, overall functional status and mood episode severity did not differ between patients with and without insomnia. This crucial observation indicates that insomnia follows an independent pathophysiological trajectory. Consequently, managing mood symptoms alone leaves sleep disturbances unresolved. Clinicians must actively identify discrete sleep disturbances instead of assuming mood stabilizers will resolve nocturnal distress. Therefore, addressing chronic insomnia as an autonomous comorbid condition allows clinicians to optimize long-term clinical recovery.
The hypothalamic-pituitary-adrenal axis regulates systemic metabolism and manages physiological responses to stress. Under normal conditions, circulating cortisol surges immediately upon waking to produce the cortisol awakening response. However, patients experiencing chronic insomnia alongside bipolar disorder exhibit a markedly blunted waking cortisol profile. Decades of unremitting circadian disruption and nocturnal arousal likely exhaust adrenocortical secretory capacity. Consequently, the adrenal cortex fails to generate adequate morning cortisol spikes, leading to persistent hypocortisolism. This flattened diurnal rhythm impairs morning alertness, reduces stress adaptability, and drives daytime exhaustion. Furthermore, blunted cortisol rhythms correlate with central adiposity, dyslipidemia, and systemic insulin resistance. Therefore, hypocortisolism represents a biological consequence of prolonged sleep disruption that weakens metabolic resilience. Clinicians evaluating daytime fatigue should recognize that neuroendocrine exhaustion, rather than worsening depression, often underlies persistent lethargy.
Chronic sleep loss exerts profound negative effects on immune signaling and inflammatory cascades. Recent findings reveal that insomnia patients exhibit significantly elevated serum levels of tumor necrosis factor-alpha. This potent inflammatory cytokine contributes directly to vascular dysfunction, tissue damage, and neuroinflammatory processes. Furthermore, elevated cytokine concentrations persist regardless of current mood states or concurrent psychotropic medication regimens. Sustained nocturnal wakefulness triggers sympathetic hyperactivity and cellular oxidative stress, driving immune cells to release inflammatory mediators. Over time, circulating cytokines disrupt blood-brain barrier integrity and disturb monoaminergic neurotransmission. Additionally, chronic inflammation accelerates atherosclerosis, hypertension, and microvascular pathology, explaining the elevated cardiovascular morbidity seen in affective disorders. Hence, persistent insomnia serves as an unremitting biological stressor that perpetuates systemic inflammation. Targeted sleep therapies may therefore reduce this inflammatory burden and safeguard cardiovascular health.
Individuals with bipolar disorder often experience shortened life expectancy and premature age-related physical illnesses. Genetic analyses reveal that chronic insomnia associates with homozygous variants in the telomerase reverse transcriptase gene. The TERT gene encodes the vital catalytic enzyme responsible for maintaining telomere length and genomic integrity. Patients harboring these homozygous alleles demonstrate compromised cellular repair capacity and increased susceptibility to cellular senescence. Moreover, persistent systemic inflammation and blunted glucocorticoid signaling further accelerate telomere erosion. When chronic sleeplessness combines with this genetic vulnerability, biological aging accelerates dramatically. As a result, patients face heightened risks for early cognitive impairment, cardiovascular pathology, and metabolic disease. These findings demonstrate that chronic insomnia represents a critical biological modifier of longevity. Clinicians must prioritize restorative sleep interventions to protect cellular health and mitigate accelerated biological aging.
Prescription patterns reveal significant differences between patients with chronic insomnia and good sleepers. Specifically, individuals suffering from persistent sleep disruption consume higher quantities of daytime anxiolytic medications. This reliance reflects severe daytime distress, heightened anxiety, and persistent nervous system hyperarousal. Conversely, these individuals use fewer antidepressant medications, suggesting unique prescribing patterns among treating physicians. However, relying on daytime sedatives or long-term benzodiazepines often disrupts circadian rhythms and creates dependence. Therefore, psychiatrists and primary care practitioners must adopt structured, multimodal management strategies. Cognitive behavioral therapy for insomnia represents the gold-standard non-pharmacological treatment for stabilizing sleep patterns. When medication becomes necessary, clinicians should select compounds that support circadian alignment without worsening daytime sedation. Prescribing sedating mood stabilizers, low-dose trazodone, or melatonin agonists can restore sleep architecture while preserving cognitive stability.
Managing sleep disruption in bipolar disorder requires proactive clinical coordination between psychiatry and internal medicine. Because sleep disturbances independently drive neuroinflammation and neuroendocrine dysfunction, routine clinical evaluations should incorporate sleep assessments. Clinicians should systematically track sleep onset latency, midnight awakenings, and daytime dysfunction during routine consultations. Furthermore, physicians must provide clear behavioral guidance regarding consistent rising times, stimulus control, and daytime sunlight exposure. Interdisciplinary collaboration between psychiatrists, endocrinologists, and general physicians facilitates early screening for metabolic syndrome and cardiovascular disease. Additionally, educating patients about sleep biology encourages adherence to lifestyle modifications and prescribed mood-stabilizing therapies. Clinicians must also avoid prescribing daytime sedatives that merely mask symptoms without resolving underlying circadian deficits. By aggressively treating insomnia, healthcare providers can reduce chronic inflammation, stabilize neuroendocrine function, and optimize patient longevity.
Chronic insomnia significantly alters hypothalamic-pituitary-adrenal axis regulation in individuals with bipolar disorder. Rather than causing sustained hyperactivity, long-term sleep disruption blunts morning waking cortisol levels. This hypocortisolism reflects neuroendocrine exhaustion from years of chronic stress, contributing to persistent fatigue, metabolic vulnerability, and impaired stress adaptation throughout daily life.
Persistent sleep loss acts as a potent physiological stressor that directly stimulates inflammatory signaling pathways. Consequently, patients exhibit elevated tumor necrosis factor-alpha concentrations regardless of their current mood episode. This continuous low-grade neuroinflammation perpetuates systemic distress, damages cellular integrity, and accelerates physical comorbidity risks in patients managing chronic bipolar disorder.
Patients with long-standing insomnia show a significantly higher rate of homozygosity for a specific variant in the TERT gene. Because this gene regulates telomerase activity and protects telomere length, its alteration promotes cellular senescence. Chronic sleep disruption combined with this genotype likely accelerates biological aging and elevates long-term somatic morbidity.
Disclaimer: This content is for informational and educational purposes only and should not be considered as medical advice or a substitute for professional medical judgment, diagnosis, or treatment. It cannot be used to endorse any product or service and does not substitute any expert clinical decision or advice. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A matched case-control study reveals that chronic insomnia in bipolar disorder acts independently of mood state, driving blunted waking cortisol, elevated inflammatory marker TNF-alpha, and genetic risk for accelerated biological aging through TERT gene variants, requiring targeted sleep interventions.
Today

A randomized crossover trial evaluated fifth-year medical students interacting with an AI standardized patient versus a human standardized patient. The study revealed key differences in Mini-CEX scores, active engagement, and interview dynamics.
Today

A comparative evaluation of INNO-LiPA, Cobas 4800, and Amplicor highlights significant assay-dependent variation in high-risk HPV detection, emphasizing the clinical distinction between analytical sensitivity and screening specificity.
Today

A Canadian nutrition study reveals that higher diet costs predict lower dietary energy density and higher fruit intake, but also increase sodium and processed meat consumption.
Today
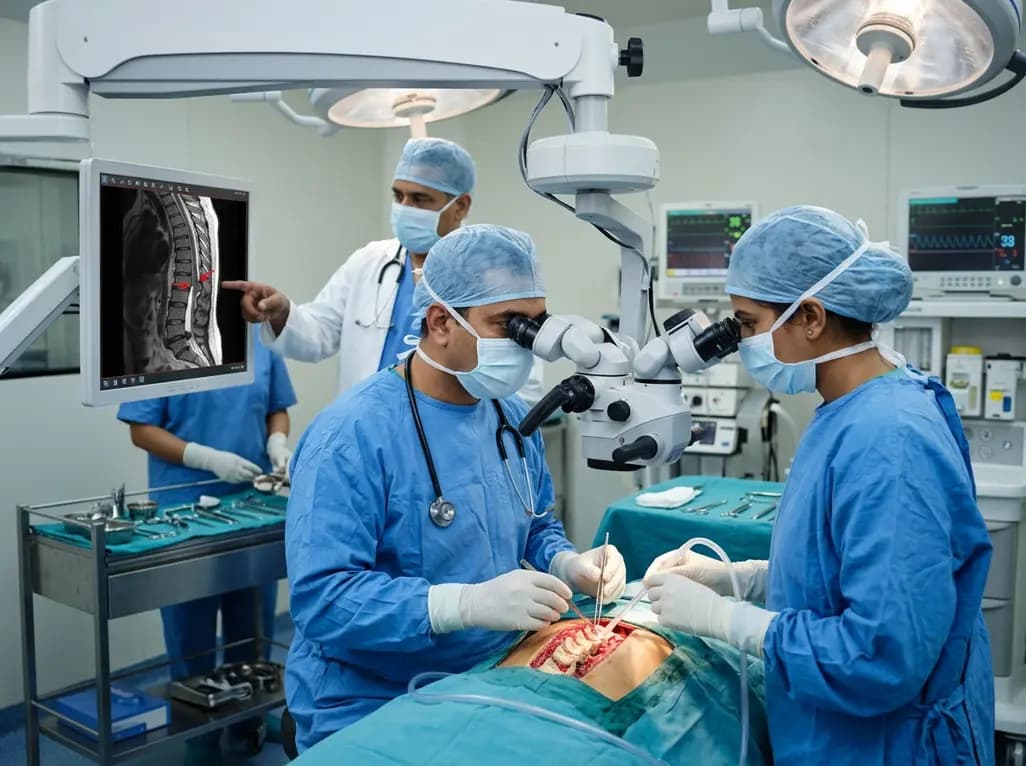
Idiopathic spinal cord herniation is a rare pathology presenting with progressive thoracic myelopathy. Early MRI identification and meticulous microsurgical reduction with dual bolstered dural defect repair prevent irreversible neurological deterioration.
Today

A novel smartphone-assisted biosensor utilizing molecularly imprinted polymers and catalytic nanozymes offers antibody-free, enzyme-free urinary microalbumin testing, enabling rapid, low-cost point-of-care screening for early chronic kidney disease.
Today
