

Loading, please wait...
Loading, please wait...

Traumatic physical injury often precipitates profound psychological distress alongside urgent surgical and orthopedic emergencies. Consequently, nearly forty percent of hospitalized trauma survivors develop post-traumatic stress disorder or major depressive disorder within one year. Trauma centers must therefore address acute physical wounds and behavioral health vulnerabilities simultaneously. Recent clinical evidence demonstrates that introducing a bedside mental health intervention improves long-term outpatient psychiatric engagement among acute trauma admissions. By initiating early behavioral dialogue in hospital wards, multidisciplinary teams bridge the precarious transition from inpatient surgical stabilization to community recovery. Furthermore, proactive emotional triage validates patient fear and encourages ongoing clinical participation.
Each year, millions of individuals sustain acute physical trauma requiring surgical admission and intensive resuscitation. Although surgical teams excel at repairing fractures and arresting visceral hemorrhages, emotional trauma frequently escapes timely clinical detection. As a result, acute psychological distress easily evolves into debilitating, chronic psychiatric morbidity. Patients facing sudden functional impairment, severe pain, and terrifying memories often experience persistent hyperarousal and profound depressive despair. Moreover, unaddressed post-traumatic stress disorder severely impedes physical rehabilitation, lowers return-to-work rates, and strains outpatient surgical resources. Therefore, modern trauma services increasingly recognize behavioral healthcare as an indispensable component of holistic trauma resuscitation. Early bedside screening protocols successfully identify patients displaying acute emotional distress or elevated baseline vulnerability. However, acute hospital stays are typically brief, and inpatient teams frequently struggle to coordinate reliable outpatient psychiatric appointments. Stepped-care models offer a pragmatic solution by embedding psychological triage directly within acute surgical wards. Thus, early hospital contact can dismantle pervasive stigma and reassure distressed patients before discharge.
To evaluate inpatient mental healthcare, researchers investigated a brief bedside mental health intervention within an urban Level I trauma center. Specifically, clinicians screened adult trauma admissions for acute post-traumatic stress and depression risk. Among 887 patients who screened positive, clinical staff offered the single-session bedside protocol to 683 individuals, reflecting an uptake offer rate of 77 percent. Over 81 percent of these offered patients accepted the intervention enthusiastically. Clinicians successfully delivered the bedside session to 452 individuals, while patient discharge or scheduling conflicts prevented completion in 103 cases. During the structured bedside consultation, behavioral health providers delivered targeted psychoeducation, normalized acute post-traumatic reactions, and taught basic grounding techniques for anxiety relief. Furthermore, providers explained the significance of attending scheduled post-discharge mental health evaluations. Rather than attempting intensive psychotherapy during acute hospitalization, this targeted session prioritized rapport building and practical coping strategies. Consequently, patients developed constructive emotional regulation skills while recovering in surgical units.
The trial demonstrated meaningful benefits regarding patient attendance at subsequent behavioral health evaluations. After adjusting for violent injury status, trauma survivors who completed the bedside session were 84 percent more likely to complete their 30-day mental health follow-up screening. This marked improvement highlights the pivotal role of personal bedside encouragement. Without early personal engagement, recovering surgical patients frequently skip psychiatric evaluations due to overwhelming orthopedic visits and functional exhaustion. However, receiving bedside validation demystifies psychiatric care and significantly diminishes post-discharge avoidance behaviors. Interestingly, completion of the single bedside session did not significantly alter 30-day post-traumatic stress or depression symptom severity scores. Similarly, the bedside protocol did not significantly increase formal outpatient psychiatric referrals. Nevertheless, these clinical outcomes align perfectly with established stepped-care principles. A brief bedside conversation cannot instantly eliminate complex emotional trauma. Instead, the intervention serves as an essential bridge toward ongoing monitoring. By successfully motivating patients to attend secondary screening, clinical teams identify persistent pathology and promptly initiate definitive outpatient therapies.
Although nonviolent trauma survivors derived substantial value from the bedside protocol, the trial revealed a critical limitation among victims of intentional interpersonal violence. In multivariate analyses, violent mechanism of injury strongly predicted initial acceptance of bedside consultations. Yet, the single bedside session failed to significantly enhance 30-day follow-up screening rates among violently injured individuals. Consequently, violently injured patients remain uniquely vulnerable to lost care continuity and unresolved post-traumatic stress. Clinicians must appreciate that interpersonal assault survivors encounter formidable social and environmental pressures. For instance, violently injured patients frequently return to environments marked by ongoing community conflict, retaliatory threats, and chronic hypervigilance. Moreover, heightened fear of retaliation and historical mistrust toward institutional systems often deter survivors from returning to hospital centers for outpatient evaluations. Therefore, brief hospital-based counseling alone cannot dismantle these complex systemic barriers. Trauma teams must acknowledge that generic bedside conversations remain inadequate for violence survivors without comprehensive community reintegration support.
These compelling findings provide valuable operational insights for trauma centers, emergency departments, and surgical wards seeking to optimize holistic outcomes. First, hospitals should institutionalize routine inpatient screening for psychological distress, establishing behavioral health assessment as a core trauma quality indicator. Second, clinical departments must deploy specialized bedside clinicians to deliver brief psychoeducation before hospital discharge. For individuals recovering from accidental or nonviolent physical trauma, this concise intervention reliably secures outpatient follow-up. Conversely, healthcare facilities must establish specialized, trauma-informed violence intervention programs for assault survivors. Such programs effectively integrate hospital-based peer support specialists, social workers, and community liaisons who address safety and legal challenges. Additionally, clinical teams should incorporate remote telehealth check-ins and mobile health monitoring to eliminate transportation hurdles for vulnerable populations. Ultimately, comprehensive trauma resuscitation extends far beyond surgical wound management and skeletal fixation. By adopting structured stepped-care behavioral models, multidisciplinary trauma teams can safeguard both physical survival and enduring mental health recovery.
Acute physical trauma triggers intense neuroendocrine stress responses that often precipitate long-term psychiatric illness. Between twenty and forty percent of hospitalized trauma patients develop post-traumatic stress disorder or major depression within one year. Unfortunately, standard surgical discharge planning frequently overlooks emotional trauma. Early hospital screening identifies vulnerable patients before severe functional impairment arises. Consequently, proactive bedside identification enables trauma centers to initiate timely stepped-care support, which prevents long-term disability and significantly enhances holistic recovery.
Survivors of intentional violence experience distinct social and structural challenges that brief inpatient sessions cannot resolve. Specifically, violently injured individuals often confront ongoing neighborhood violence, legal entanglements, acute safety threats, and severe socioeconomic instability. Furthermore, profound medical mistrust and fear of retaliation discourage patients from returning to healthcare facilities for non-urgent appointments. Consequently, addressing psychological distress in violence survivors requires intensive, culturally tailored hospital-based violence intervention programs rather than brief, generic bedside consultations alone.
A stepped-care model organizes behavioral healthcare into progressive tiers of clinical intensity based on patient need. Initially, hospital staff provide universal distress screening and brief bedside psychoeducation to admitted trauma patients. Subsequently, clinicians reserve more resource-intensive treatments, such as trauma-focused cognitive behavioral therapy or psychiatric pharmacotherapy, for patients demonstrating persistent symptoms at outpatient follow-up. Thus, this pragmatic approach optimizes healthcare resources by delivering targeted psychological support without overwhelming surgical departments or outpatient psychiatric clinics.
Disclaimer: This content is for informational and educational purposes only. It is not intended to be a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or another qualified healthcare provider with any questions you may have regarding a medical condition. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A Level I trauma center study shows a brief bedside mental health intervention boosts 30-day follow-up screening adherence by 84% in nonviolent injury patients. However, outcomes for violence survivors reveal critical care gaps, underscoring the urgent need for specialized community violence intervention programs.
Today
A nationwide study reveals that leisure-time physical activity enhances phase angle and optimizes the extracellular water-to-total body water ratio in older adults, whereas occupational activity shows no benefit. These bioelectrical markers offer crucial insights for sarcopenia screening and geriatric care.
Today

A randomized crossover study demonstrates that conventional and robotic laparoscopy require distinct neuropsychological and psychomotor skills. While trainees master conventional laparoscopy faster, robotic proficiency demands individualized, adaptive curricula tailored to specific learner profiles.
Today
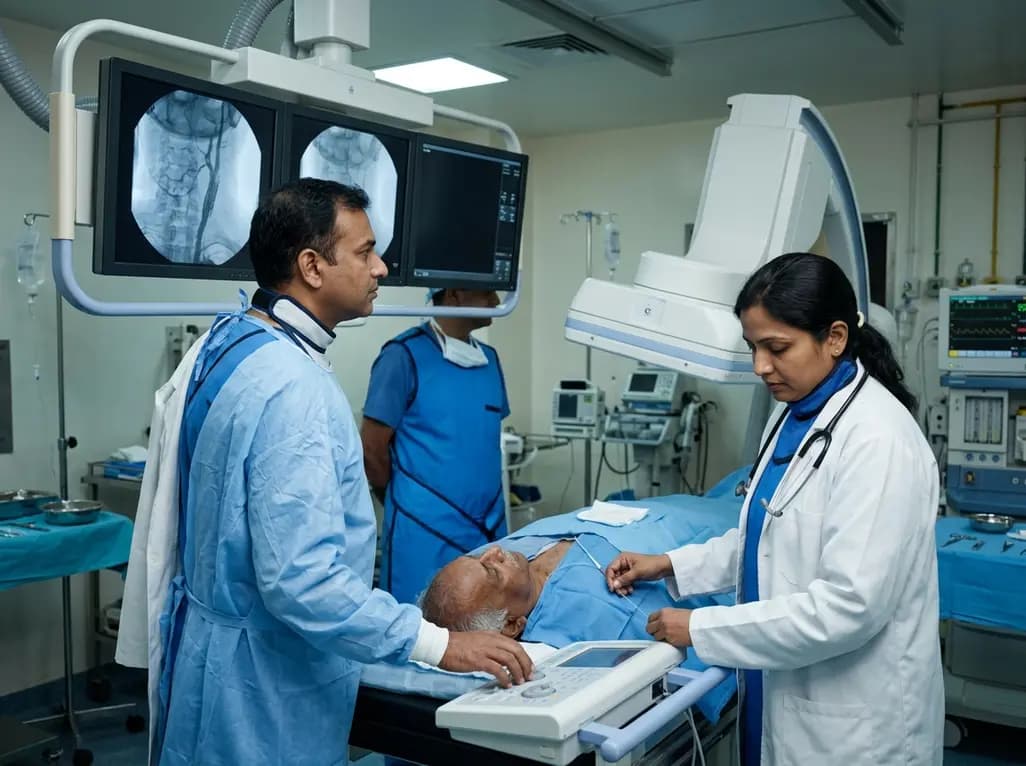
A retrospective study of 109 patients undergoing elective carotid artery stenting evaluated radiation exposure on biplane flat-panel systems. Standardized workflows and dedicated low-dose protocols provide crucial baseline data to establish neurointerventional diagnostic reference levels and optimize patient safety.
Today

An Australian cohort of 34,449 adults in an unsubsidized tirzepatide digital weight loss service showed that peer-referred patients achieved significantly higher 6-month adherence (48% vs 42%) and greater weight loss (16.16% vs 14.06%) than matched non-referred peers, highlighting social support in obesity care.
Today
