

Loading, please wait...
Loading, please wait...

Alzheimer's disease pathology encompasses complex neurodegenerative mechanisms that extend far beyond amyloid plaques and tau tangles. However, recent molecular discoveries reveal that apolipoprotein E4 profoundly reshapes the immune system across central and peripheral compartments. Consequently, carriers of this allele experience an accelerated decline in neural and vascular integrity. Importantly, APOE4 immune dysfunction establishes an active, self-reinforcing inflammatory loop connecting brain and peripheral cells. Furthermore, maladaptive microglial phenotypes and circulating inflammatory cells continuously accelerate neurodegeneration. In addition, this systemic immune remodeling compromises cerebral resilience against metabolic stress. Therefore, understanding this integrated neuroimmune network provides clinicians with a modern framework for evaluating disease risk.
In the healthy brain, resting microglia continually survey the cerebral parenchyma to preserve synaptic architecture. In contrast, apolipoprotein E4 forces these resident immune cells away from homeostatic surveillance. Specifically, the APOE4 isoform induces profound metabolic exhaustion and intracellular lipid droplet accumulation. This lipid dysregulation impairs microglial motility and compromises cellular clearance pathways. Consequently, APOE4 microglia fail to clear neurotoxic amyloid-beta oligomers and hyperphosphorylated tau aggregates. Moreover, these metabolically stressed cells adopt a chronic, maladaptive pro-inflammatory phenotype. They release substantial amounts of interleukin-1 beta, interleukin-6, and tumor necrosis factor-alpha into the surrounding tissue. In addition, these reactive microglia execute aberrant synaptic pruning, directly damaging viable neuronal circuits. Therefore, microglial dysfunction converts protective surveillance cells into active mediators of neurodegeneration. Ultimately, this metabolic and phenotypic collapse establishes an environment that accelerates cognitive decline in vulnerable individuals.
Modern neuroimmunology demonstrates that Alzheimer's disease involves significant peripheral immune remodeling. Apolipoprotein E4 is expressed not only in the brain but also across circulating leukocytes and tissue macrophages. Consequently, peripheral immune compartments in APOE4 carriers exhibit altered baseline activation states. Specifically, circulating monocytes display a primed inflammatory signature that produces excessive cytokines upon stimulation. In addition, cytotoxic CD8-positive T lymphocytes and inflammatory neutrophils show heightened baseline reactivity. This persistent cellular priming creates a long-term peripheral reservoir of chronic inflammation. Furthermore, systemic inflammatory mediators continuously challenge the cerebral vasculature throughout aging. Because peripheral leukocytes share this detrimental genetic variant, systemic inflammation mirrors intracerebral pathology. Consequently, this persistent cross-talk accelerates neurovascular stress. Thus, peripheral immune cells do not remain passive spectators during neurodegenerative illness. Instead, they actively promote progressive neurological deterioration.
The blood-brain barrier normally protects neural tissue from circulating macromolecules and systemic immune cells. However, APOE4 directly damages brain capillary endothelial cells and pericytes. This molecular vulnerability leads to accelerated pericyte loss and degradation of tight junction proteins. Consequently, the blood-brain barrier becomes permeable, allowing neurotoxic serum proteins like fibrinogen to enter neural tissue. In addition, this barrier breakdown facilitates the transmigration of primed peripheral leukocytes into vulnerable brain regions. Once inside the parenchyma, circulating T cells and monocytes interact directly with resident microglia. Therefore, mechanisms linking APOE4 immune dysfunction bridge peripheral and central compartments into an integrated pathological circuit. Furthermore, infiltrating immune effectors release matrix metalloproteinases that exacerbate vascular leakage. As a result, loss of compartmental integrity accelerates localized neuronal destruction and synaptic failure.
The interplay between vascular compromise and chronic inflammation establishes an escalating feed-forward cycle. Specifically, impaired glymphatic clearance in APOE4 carriers stalls the convective removal of interstitial fluid and toxic solutes. Astrocytic end-feet lose polarized aquaporin-4 water channels, worsening vascular amyloid deposition. Consequently, cerebral amyloid angiopathy develops and restricts microvascular perfusion. In addition, persistent cerebral hypoperfusion induces secondary oxidative stress and cellular hypoxia. These metabolic insults stimulate microglia and astrocytes to secrete inflammatory chemokines such as CCL2. Subsequently, these chemoattractants draw additional peripheral immune cells across the compromised blood-brain barrier. Therefore, recurrent inflammatory surges exhaust endogenous neural repair mechanisms. Additionally, neurovascular damage restricts nutrient delivery while accelerating toxic metabolite retention. Moreover, sustained neuroinflammation directly precipitates synaptic loss and widespread neuronal apoptosis. Ultimately, this vicious cycle of vascular decay and immune activation drives clinical disease progression.
Targeting the intersection of genetics and neuroimmunology reveals promising translational therapeutic opportunities. Historically, clinical drug development focused primarily on monoclonal antibodies targeting amyloid plaques. However, contemporary strategies increasingly focus on modulating the APOE4 immune axis. Specifically, small molecules designed to correct APOE4 protein structure help restore normal microglial lipid metabolism. Furthermore, activating the TREM2 receptor enhances microglial phagocytosis while mitigating synaptotoxic inflammation. In the periphery, biologic agents that block pro-inflammatory cytokines or inhibit leukocyte trafficking may halt systemic disease amplification. Additionally, antisense oligonucleotides and gene therapies offer innovative tools to lower pathological APOE4 expression. Because immune dysfunction varies significantly across disease stages and individual patients, clinicians require stage-specific biomarkers for precision medicine. Specifically, integrating multi-omic profiling helps identify targetable immune nodes. Therefore, future clinical trials must incorporate longitudinal blood and cerebrospinal fluid assays to guide timely targeted therapy.
The APOE4 allele shifts microglia from protective surveillance toward a metabolically stressed, chronically inflamed state. In carrying cells, disrupted lipid trafficking causes intracellular lipid droplet accumulation and metabolic exhaustion. Consequently, these microglia fail to clear amyloid-beta aggregates and apoptotic debris effectively. Instead, they secrete sustained pro-inflammatory cytokines and trigger aberrant synaptic pruning. This loss of normal microglial homeostasis impairs neuronal communication and accelerates neurodegenerative pathology in vulnerable brain regions.
Peripheral immune remodeling is clinically significant because APOE4 primes circulating monocytes, neutrophils, and lymphocytes toward hyper-reactivity. Furthermore, the genetic variant weakens the blood-brain barrier through pericyte and endothelial degeneration. This structural breakdown allows primed peripheral immune cells and circulating inflammatory cytokines to infiltrate the brain parenchyma. Consequently, peripheral inflammation directly fuels central neuroinflammation, creating a self-reinforcing pathogenic loop that accelerates neuronal destruction and hastens cognitive decline in Alzheimer's patients.
Emerging therapeutic approaches include small-molecule structure correctors designed to convert APOE4 into an APOE3-like conformation, thereby restoring cellular lipid homeostasis. Additionally, investigators are developing TREM2 agonists to reactivate microglial phagocytosis and suppress inflammatory signaling. Other innovative strategies employ antisense oligonucleotides to silence APOE4 expression and biologic therapies to inhibit peripheral leukocyte trafficking. These stage-specific interventions aim to interrupt bidirectional neuroimmune signaling before extensive, irreversible synaptic damage occurs across the brain.
Disclaimer: This content is for informational and educational purposes only and is not intended as medical advice. Healthcare professionals should make independent treatment decisions based on individual patient assessments and clinical judgment. The authors and publishers assume no liability for any actions taken based on this information. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Apolipoprotein E4 drives Alzheimer's disease progression by remodeling central and peripheral immune responses. This review examines how APOE4 impairs microglial surveillance, primes peripheral leukocytes, and erodes the blood-brain barrier to fuel neurodegeneration, highlighting novel precision therapeutic targets.
Today
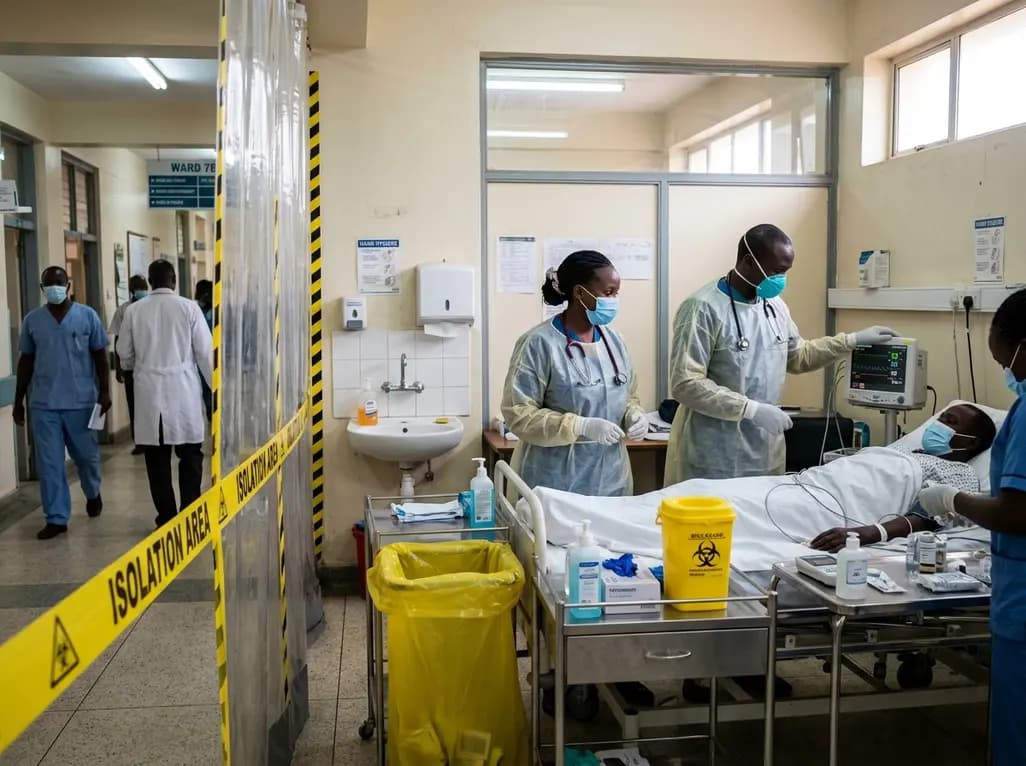
Kenya's confirmation of its eighth Ebola infection highlights the acute risk of secondary transmission in hospital environments. Clinicians must maintain high vigilance, enforce strict infection prevention protocols, and implement rapid triage mechanisms for viral hemorrhagic fevers across healthcare settings.
Today
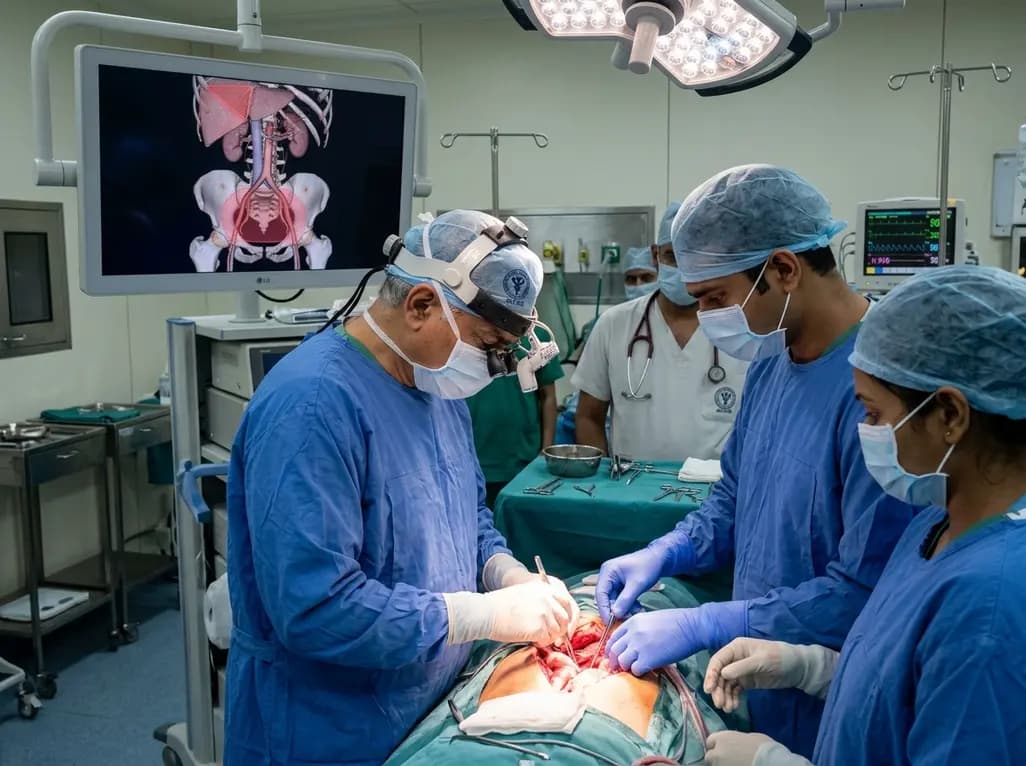
Surgical oncologists at AIIMS Delhi have mapped two critical anatomical landmarks: Ray's Zone in the deep pelvis and Ray's Hepatocaval Triangle near the liver. These predefined hazard boundaries guide dissection, dramatically reduce severe intraoperative bleeding, and preserve vital nerves and visceral organs.
Today

A study reveals that the MYLK c.4079G>A, p.(Gly1360Asp) variant is linked to high-penetrance heritable thoracic aortic disease and early-onset aortic dissection, showing a founder effect in Finnish cohorts. Findings emphasize early cascade screening and vigilant surveillance.
Yesterday

A novel sacrificial-template technique combines FDM polymer 3D printing and micro-arc oxidation to fabricate orientation-controlled porous titanium scaffolds. These bioactive constructs offer tailored stiffness, exceptional multidirectional load resistance, and robust osseointegration for bone defect repair.
Today

A novel label-free electrochemical biosensor utilizing magnetic nanocomposites enables ultrasensitive TERT C228T mutation detection (LOD: 0.67 pM) for rapid risk stratification in papillary thyroid cancer, offering promising point-of-care utility for endocrine oncology.
Today
