

Loading, please wait...
Loading, please wait...

Clinical microbiology laboratories play an essential role in guiding targeted antibiotic therapy. Currently, hospital workflows depend heavily on commercial antimicrobial susceptibility testing devices to deliver rapid results. However, broth microdilution remains the universal reference standard for determining minimum inhibitory concentrations. Because commercial platforms utilize surrogate algorithms, regulatory bodies require rigorous validation before routine clinical adoption. Consequently, clinicians must understand the underlying performance discrepancies between international standard organizations.
Broth microdilution serves as the primary benchmark for establishing bacterial minimum inhibitory concentrations worldwide. Nevertheless, manual microdilution testing requires substantial technical skill, pristine media preparation, and extensive technician time. Therefore, routine clinical laboratories primarily implement automated antimicrobial susceptibility testing devices and surrogate phenotypic assays. These commercial platforms assess bacterial growth kinetics, optical density, or redox indicators to extrapolate clinical susceptibility. In addition, diagnostic centers frequently utilize disk diffusion and commercial gradient diffusion strips for challenging isolates. Although these convenient platforms accelerate laboratory turnaround, they do not directly replicate reference broth mechanics. As a result, professional standard organizations establish strict evaluation protocols to guarantee diagnostic comparability. Regulatory bodies require manufacturers to demonstrate that surrogate platforms match broth microdilution reliably before commercial distribution. Furthermore, proprietary mathematical algorithms must interpret diverse bacterial species and emerging resistance phenotypes without systematic distortion. Without standardized performance criteria, subtle testing artifacts could misguide patient care and fuel therapeutic failure. Consequently, global agencies continuously refine validation frameworks to ensure consistent diagnostic precision across healthcare facilities.
Evaluating diagnostic systems requires clear performance benchmarks. Standard protocols distinguish analytical agreement from clinical categorical concordance. Specifically, essential agreement measures whether an automated instrument produces an inhibitory concentration within one doubling dilution of reference broth microdilution. This mathematical parameter reflects pure analytical accuracy across tested dilutions. In contrast, categorical agreement examines whether the system assigns the identical interpretive category, namely susceptible, intermediate, or resistant. Discrepancies between methods generate critical classification errors. For instance, very major errors occur when a platform misclassifies a truly resistant isolate as susceptible. Consequently, clinicians might administer ineffective antibiotics during life-threatening sepsis. Conversely, major errors arise when a susceptible organism is misclassified as resistant. This error inappropriately eliminates effective, narrow-spectrum therapeutic options. In addition, minor errors reflect intermediate interpretive disagreements between testing modalities. While categorical agreement directly influences bedside decision-making, it depends entirely on designated cutoff values. Therefore, analytical agreement and systematic bias provide essential insight into raw instrument reproducibility, independent of fluctuating interpretive criteria.
Standard development organizations and regulatory agencies adopt fundamentally divergent evaluation philosophies. For example, the Clinical and Laboratory Standards Institute and the United States Food and Drug Administration emphasize categorical agreement and error thresholds. They judge device performance strictly against current clinical breakpoints. However, the International Organization for Standardization framework focuses primarily on analytical parameters. Specifically, ISO guidelines prioritize essential agreement, reproducibility, and mathematical bias without calculating categorical errors. Meanwhile, the European Committee on Antimicrobial Susceptibility Testing aligns analytically with ISO standards while independently maintaining responsibility for breakpoint definitions. Furthermore, the European Union In Vitro Diagnostic Regulation enforces stringent clinical performance mandates on commercial manufacturers. These differing philosophies create substantial regulatory discordance. When an agency revises an interpretive breakpoint, categorical agreement often collapses immediately. Yet, the underlying analytical capability of the hardware remains unchanged. Consequently, an identical commercial platform may achieve regulatory approval under one framework while failing validation under another, complicating global surveillance.
Commercial testing platforms often correlate well with reference broth microdilution near standard breakpoints. Nevertheless, systematic bias frequently skews minimum inhibitory concentrations across broader dilution ranges. For example, an automated system may consistently overestimate or underestimate inhibitory values by one dilution step. Although the device satisfies essential agreement requirements, systematic drift introduces perilous interpretive instability. Moreover, regulatory updates create extended implementation delays for hospital laboratories. When professional committees adjust breakpoints to address emerging resistance mechanisms, device manufacturers must re-engineer test panels. Subsequently, vendors must submit extensive verification data to regulatory agencies before releasing software updates. In the United States, clearance through federal regulators often delays modern software integration by several years. Similarly, European diagnostic regulations impose extensive clinical validation dossiers on automated manufacturers. During these multi-year transition periods, commercial systems continue reporting clinical results using obsolete interpretive criteria. As a result, microbiology laboratories unknowingly produce discordant susceptibility classifications, directly undermining local antimicrobial stewardship efforts.
Healthcare systems in low- and middle-income countries face severe diagnostic bottlenecks. Notably, hospitals in these regions encounter disproportionately high rates of multidrug-resistant pathogens, including carbapenem-resistant Gram-negative bacilli. However, resource-constrained laboratories rarely possess the financial resources to conduct continuous manual broth microdilution. Instead, they depend on automated testing devices or classic disk diffusion methods. Unfortunately, proprietary commercial panels often arrive locked with outdated manufacturer breakpoints. Furthermore, upgrading proprietary software requires costly service contracts that straining hospital budgets cannot accommodate. Consequently, clinicians may inadvertently select inappropriate therapies based on outdated susceptibility thresholds. To mitigate these risks, local microbiology teams must actively audit their laboratory systems. Specifically, microbiologists can implement manual secondary validation protocols, such as disk diffusion or gradient strips, for critical drug-pathogen combinations. Additionally, institutional antimicrobial stewardship committees should establish local interpretive conversion tables reflecting modern guidelines. Ultimately, international standard development organizations and device manufacturers must harmonize regulatory pathways, ensuring affordable, timely software updates for vulnerable healthcare ecosystems.
Commercial device manufacturers must obtain formal regulatory re-clearance before updating their internal interpretive algorithms. Following revised breakpoint recommendations by expert committees, manufacturers must complete rigorous multi-center clinical trials and extensive analytical validations. This complex approval pipeline routinely requires multiple years under stringent regulatory authorities. Consequently, hospital laboratories frequently operate with obsolete instrument cutoffs unless local teams perform independent internal validations to override software settings.
Systematic minimum inhibitory concentration bias shifts numerical testing results consistently in one direction. Even when an instrument meets standard essential agreement criteria, subtle one-dilution skews can cross clinical interpretive thresholds. Therefore, underestimating inhibitory values risks misclassifying resistant pathogens as susceptible, promoting ineffective therapy. Conversely, overestimating values causes false-resistant classifications. This artificially narrows therapeutic choices, needlessly compelling clinicians to prescribe broader second-line antibiotics and worsening institutional resistance rates.
Laboratories should first identify which breakpoint version their automated instrument utilizes for critical pathogens. When software updates lag behind current standards, microbiologists can perform alternative manual testing, such as calibrated disk diffusion or gradient strips. Furthermore, hospital stewardship teams can apply post-analytical software rules or manual conversion charts to raw minimum inhibitory concentrations. Finally, participating in external quality assessment programs ensures consistent error detection and reporting accuracy.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A critical evaluation of antimicrobial susceptibility testing devices across CLSI, EUCAST, ISO, and FDA frameworks, highlighting the clinical risks of systematic bias, error rates, and outdated breakpoints in LMIC laboratories.
Today
Cardiac involvement is the leading cause of mortality in EGPA. This report highlights an overlap phenotype of lymphocyte-predominant myocardial injury, Takotsubo-like cardiomyopathy, and left ventricular thrombus, emphasizing early multimodality diagnostics and aggressive immunosuppressive biologic therapy.
Today
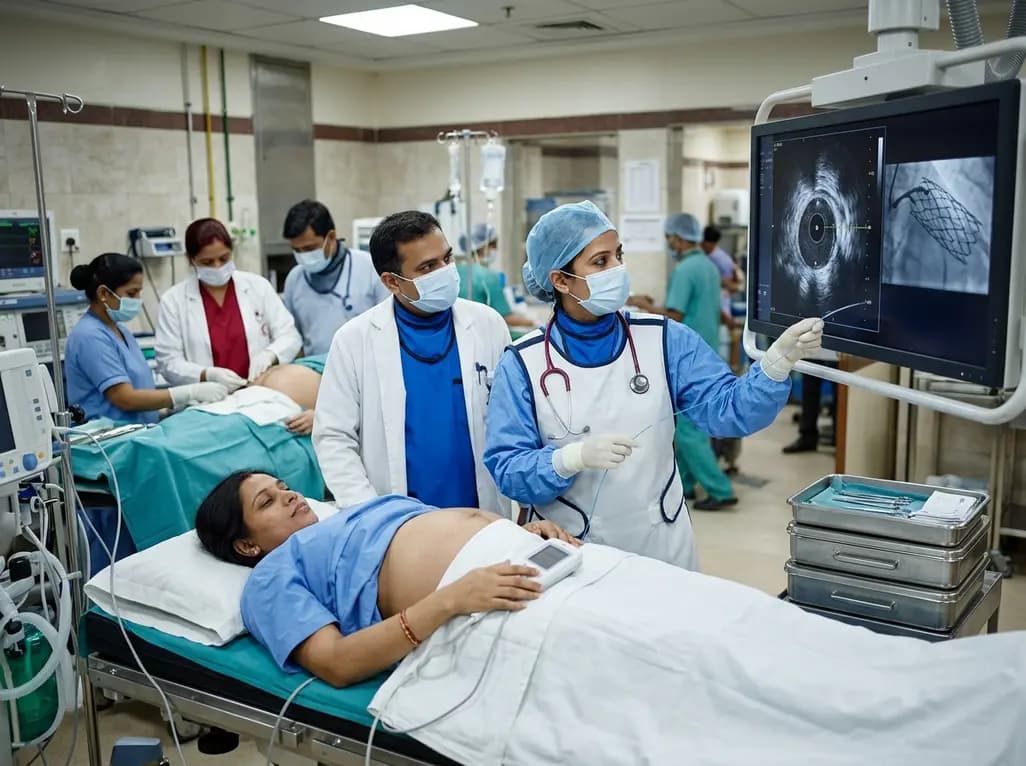
A 32-year-old gravida at 38 weeks with anterior STEMI underwent emergent IVUS-guided PCI and successful cesarean delivery under uninterrupted DAPT, highlighting cardio-obstetric care.
Today
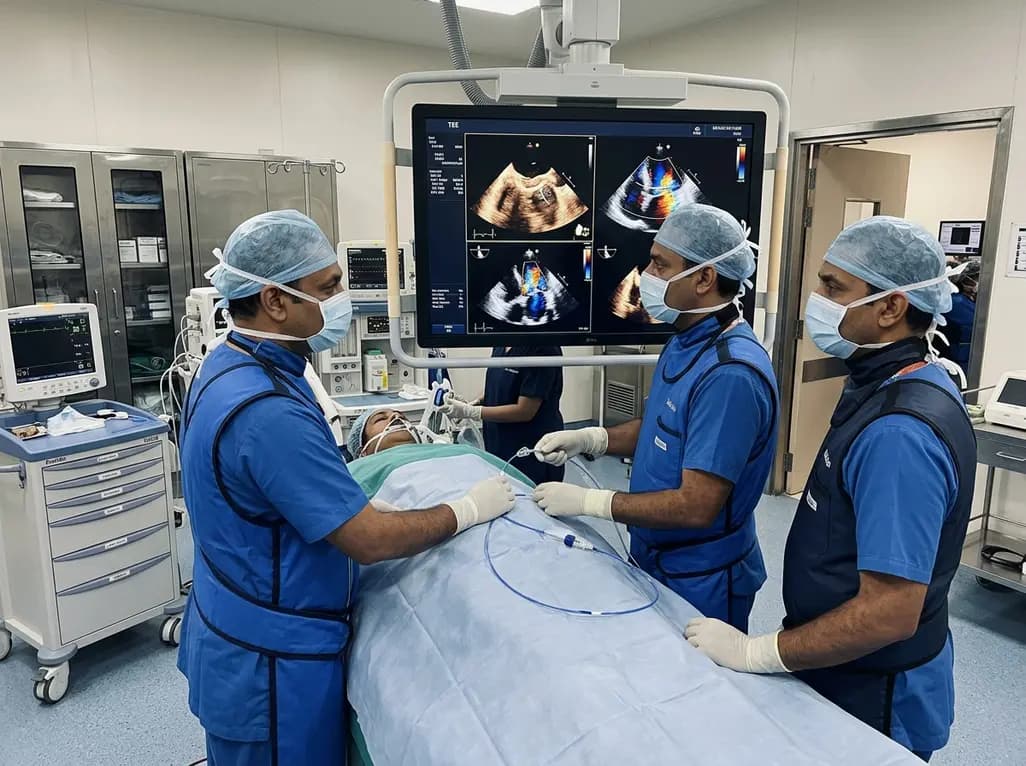
Transcatheter edge-to-edge repair (TEER) successfully treated severe mitral regurgitation from a posterior leaflet perforation. Guided by 3D multiplanar reconstruction, operators sandwiched the defect using two MitraClip devices, providing safe hemodynamic recovery without requiring open-heart surgery.
Today

A landmark biomechanical study demonstrates that sports bra support and running shoe cushioning interact significantly to influence tibial acceleration, breast motion, and comfort in female runners, providing crucial insights for clinical counseling in sports medicine and women's health.
Yesterday

A systematic review and meta-analysis of 5,406 participants reveals that tirzepatide significantly reduces hsCRP by 34.3%, improves cardiorenal biomarkers, and enhances functional capacity and exercise endurance in patients with heart failure.
Today
