

Loading, please wait...
Loading, please wait...

Recent breakthroughs in artificial intelligence offer unprecedented convenience, yet they introduce profound clinical hazards. Clinicians routinely browse AI-generated medical abstracts to stay abreast of rapid developments in acute care. However, large language models often fabricate convincing scientific statements with authoritative fluency. When emergency physicians and trauma surgeons encounter synthetic evidence, subtle inaccuracies can compromise patient safety. Therefore, understanding how medical professionals evaluate algorithmic summaries is essential for modern evidence-based clinical practice.
Emergency departments and trauma operating theatres demand rapid clinical choices under intense cognitive strain. Consequently, clinicians frequently scan literature summaries rather than full manuscripts to evaluate novel therapeutic protocols. Artificial intelligence tools now create sophisticated summaries within seconds. While these summaries mirror rigorous academic writing, they frequently invent false outcomes or misleading drug dosages. Because large language models assemble text based on statistical probability rather than verified scientific truth, plausible misinformation appears genuine. Medical professionals naturally rely on scientific tone, sophisticated vocabulary, and structured formatting to assess credibility. Unfortunately, advanced algorithms master these surface characteristics effortlessly. As a result, acute care clinicians face unprecedented exposure to persuasive clinical falsehoods. Furthermore, the intense time pressures of emergency shifts reduce the likelihood of thorough fact-checking at the bedside. Clinicians who review literature summaries in acute settings may unknowingly absorb invalid claims. Subsequently, these fabricated statements can directly alter treatment protocols, diagnostic choices, and resuscitation algorithms.
To quantify these operational risks, researchers designed a cross-sectional diagnostic accuracy study across four emergency and trauma hospitals in Germany. Investigators generated vignettes using GPT-5 Thinking mode to mirror realistic clinical publications. Specifically, each participant reviewed four distinct abstracts covering acute trauma and emergency scenarios. Two abstracts presented authentic scientific findings supported by valid clinical data. In contrast, the remaining two abstracts contained intentionally fabricated claims supported by plausible medical explanations. The primary outcome evaluated whether physicians expressed an intent to act on the fabricated recommendations in clinical scenarios. Secondary measures included perceived precision, scientific structure, grammatical fluency, and overall factual accuracy. Twenty experienced trauma surgeons and emergency physicians completed eighty blinded evaluations. The researchers structured the study design to determine whether clinical seniority shielded physicians from algorithmic deceit. By standardizing the format across both authentic and false vignettes, the study isolated textual credibility from actual clinical truth. Consequently, the investigation provided objective metrics regarding physician susceptibility to sophisticated synthetic publications.
The investigation revealed alarming patterns regarding clinical decision-making. Overall, physicians intended to act on sixty-eight percent of all assessed abstracts. When researchers evaluated the clinical decision to act against factual truth, the sensitivity reached seventy-eight percent. However, the specificity plummeted to forty-three percent, demonstrating a severe inability to reject false claims. The positive predictive value stood at fifty-seven percent, while the negative predictive value reached sixty-five percent. Furthermore, the diagnostic odds ratio was 2.55, and the positive likelihood ratio was only 1.35. These statistical findings prove that clinicians struggle to distinguish genuine evidence from fabricated claims. Intriguingly, participants assigned virtually identical ratings to true and false abstracts across multiple credibility metrics. Perceived accuracy, precision, grammatical elegance, and structural organization showed no statistically significant differences between true and false vignettes. Clinicians rated abstracts they intended to implement significantly higher in structural coherence and precision. Therefore, persuasive prose directly drives clinical acceptance regardless of factual veracity.
The implications of unverified algorithmic claims extend far beyond theoretical academic debates. In trauma surgery and emergency resuscitation, treatment protocols depend entirely on precise hemodynamic targets and medication timing. If an unverified abstract recommends an incorrect antifibrinolytic dosing schedule, catastrophic hemorrhage may ensue. Similarly, false summaries suggesting improper airway algorithms can precipitate hypoxic brain injury during rapid sequence intubation. Clinicians who incorporate synthetic abstracts into emergency department pathways inadvertently expose vulnerable patients to preventable morbidity. Moreover, institutional clinical governance faces severe challenges when clinicians cite non-existent trials during departmental audits. In resource-limited emergency rooms, misplaced reliance on flawed interventions diverts vital supplies away from validated therapies. Junior doctors and postgraduate trainees remain especially vulnerable to these deceptive summaries. Because trainees constantly seek educational literature, exposure to hallucinated evidence distorts foundational knowledge during crucial learning phases. Consequently, unverified artificial intelligence outputs threaten patient safety, clinical education, and hospital liability.
Healthcare teams must establish proactive defenses to prevent algorithmic misinformation from reaching patients. First, clinicians must never implement clinical recommendations based solely on abstract summaries. Practitioners should always examine full-text manuscripts and verify underlying primary datasets before adopting new clinical maneuvers. Second, medical departments should implement structured verification protocols for any literature retrieved through artificial intelligence interfaces. Clinicians must cross-reference citations within established databases such as PubMed, MEDLINE, or the Cochrane Library. Additionally, journal peer reviewers and academic editors must employ advanced detection workflows to flag synthetic content in submitted manuscripts. Medical schools and postgraduate residency programs must modernize their evidence-based medicine curricula. Educators should teach trainees how large language models generate fluent hallucinations. Furthermore, hospital credentialing boards should require digital literacy modules focusing on artificial intelligence risks. Healthcare systems must emphasize that linguistic fluency does not equate to scientific veracity. By fostering rigorous appraisal habits, clinicians can harness technological advancements without compromising diagnostic integrity.
Large language models generate text by predicting statistical patterns of words rather than retrieving verified clinical knowledge. Because these algorithms prioritize grammatical fluency and plausible narrative flow over factual reality, they easily fabricate plausible clinical trials, drug dosages, and patient outcomes. The models cannot verify internal clinical validity, meaning they deliver fabricated claims with the same confident tone and polished presentation they use for true medical facts.
Physicians failed to detect fabricated abstracts because the artificial intelligence matched the tone, grammar, and structural format of authentic peer-reviewed literature. Clinicians instinctively associate professional terminology and sophisticated scientific structure with academic credibility. Because the fabricated vignettes contained plausible physiological explanations, participants focused on superficial presentation rather than verifying underlying data, leading them to misjudge false statements as reliable clinical recommendations.
Clinicians should never adopt clinical interventions based purely on unverified summaries or abstract overviews. Instead, practitioners must confirm that cited citations exist by searching index databases like PubMed and the Cochrane Library. Furthermore, clinicians should review full-text methodology sections, examine source data, and cross-reference findings against established professional society guidelines. Incorporating these multi-step verification protocols ensures that algorithmic fabrications do not compromise acute patient care.
Disclaimer: This content is for informational and educational purposes only and is not intended as medical advice. Always consult a qualified healthcare provider for diagnosis and treatment recommendations. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A landmark study reveals emergency and trauma surgeons often accept hallucinated AI-generated medical abstracts, acting on false data due to convincing prose. Explore the clinical risks, diagnostic accuracy metrics, and vital verification safeguards required to protect patients in evidence-based medicine.
Today
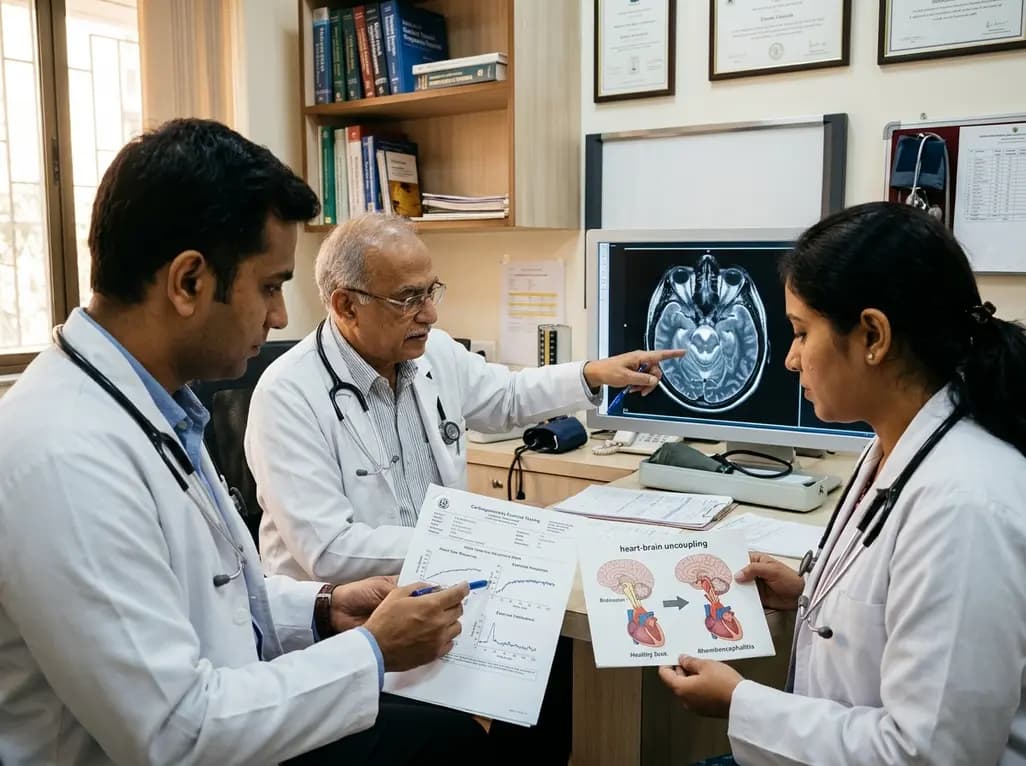
Central chronotropic incompetence is an underrecognized sequela of rhombencephalitis causing exertional dyspnea despite normal resting cardiac function. Cardiopulmonary exercise testing unmasks this heart-brain uncoupling, guiding rate-responsive pacing and targeted rehabilitation.
Today

A landmark study reveals that lipid-rich malignant ascites alters the T-cell metabolic transcriptome, causing cholesterol efflux and impaired fatty acid oxidation. This suppresses TCR signalling and blocks BiTE immunotherapy, while lipid depletion restores antitumour cytotoxicity in ovarian cancer.
Today
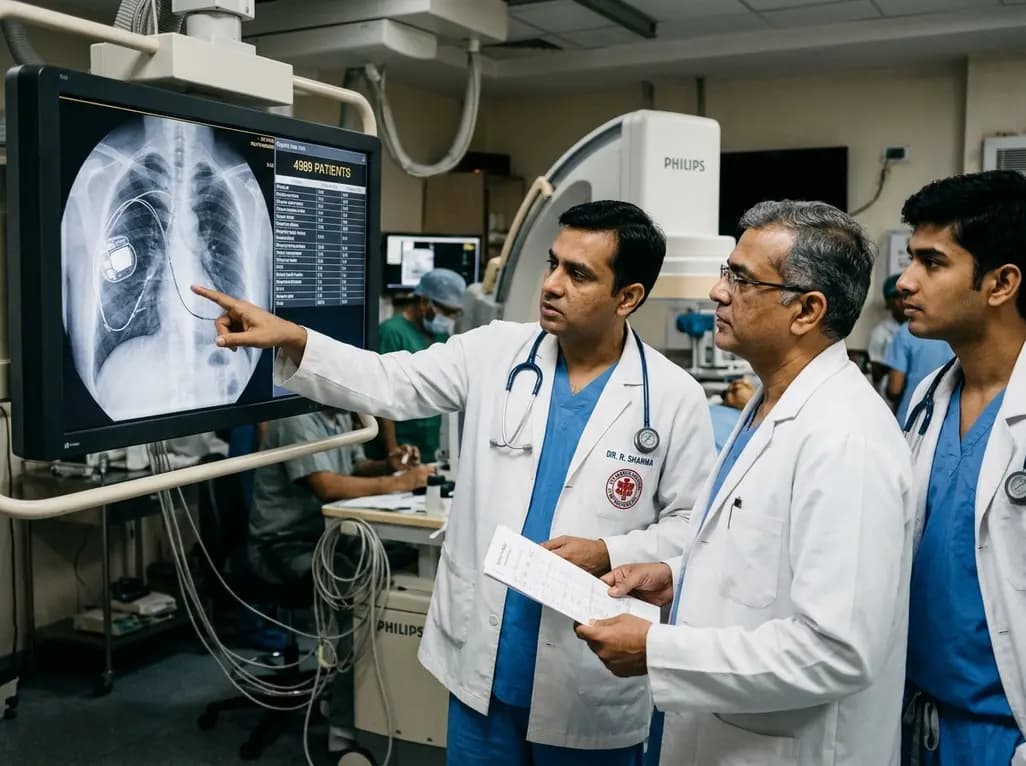
A registry study of 4,989 patients evaluates transvenous lead extraction for right-sided cardiac devices. Despite longer dwell times and older leads, right-sided extractions achieve high procedural success and comparable safety to left-sided approaches.
Today

Recent crash analyses demonstrate significant variations in traffic injury severity across vehicle seating positions. Electric vehicle passengers face disproportionately higher trauma risks than drivers, particularly during airbag deployments, demanding adapted emergency assessment and clinical vigilance.
Today

Understand the causal role of Lipoprotein(a) in cardiovascular disease, why international guidelines recommend once-in-a-lifetime molar testing, and the clinical implications of recent phase 3 RNA outcome trials.
Today
