

Loading, please wait...
Loading, please wait...
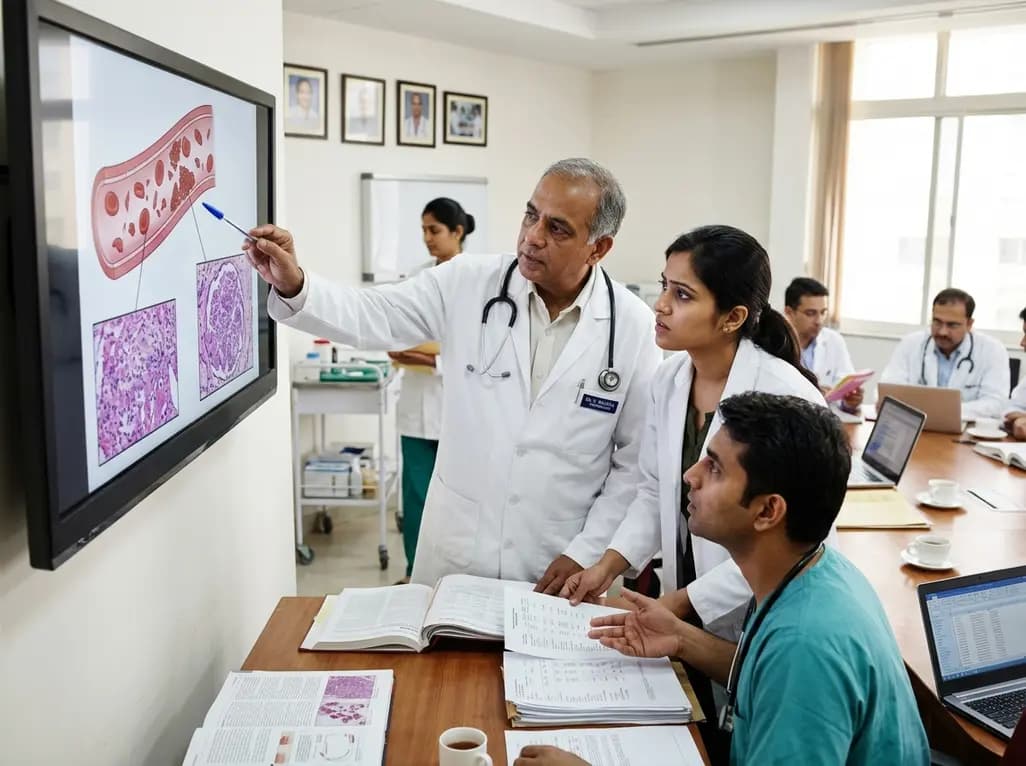
The sudden manifestation of acquired TTP in scleroderma represents an exceptionally rare yet perilous hematological emergency. Thrombotic microangiopathy occasionally complicates systemic sclerosis, but true immune-mediated thrombotic thrombocytopenic purpura remains distinctly uncommon. Recently, clinicians documented a rare presentation of acquired thrombotic thrombocytopenic purpura in a forty-four-year-old woman with anti-centromere antibody-positive limited cutaneous systemic sclerosis. The patient presented with diffuse purpura, severe thrombocytopenia, and overt microangiopathic hemolytic anemia. Interestingly, she exhibited normal systemic blood pressure, baseline serum creatinine levels, and intact neurological function during initial triage. Connective tissue diseases frequently trigger diverse microvascular injuries, yet clinicians seldom anticipate severe autoimmune protease deficiencies in limited scleroderma. Because microvascular thrombosis can rapidly produce irreversible multiorgan ischemia, physicians must maintain a high index of suspicion. Early recognition requires thorough peripheral blood smear evaluations to identify fragmented red blood cells or schistocytes. In addition, prompt diagnostic awareness enables critical intervention before catastrophic neurological or cardiac complications develop. Therefore, healthcare providers must routinely integrate targeted hematological assessments whenever patients with systemic sclerosis present with unexplained thrombocytopenic purpura.
Differentiating thrombotic thrombocytopenic purpura from scleroderma renal crisis poses an intricate clinical dilemma. Scleroderma renal crisis represents a quintessential rheumatologic emergency that classically manifests with new-onset accelerated hypertension and rapidly progressive acute renal failure. Furthermore, patients with renal crisis frequently show mild microangiopathic hemolytic anemia and moderate thrombocytopenia. In contrast, acquired thrombotic thrombocytopenic purpura produces profound thrombocytopenia, marked red cell fragmentation, and fluctuating cerebral ischemia. However, blood pressure often remains entirely normal in pure TTP presentations. Clinicians facing this diagnostic fork must evaluate clinical markers methodically. Prescribing high-dose systemic corticosteroids constitutes the standard first-line intervention for autoimmune TTP. Conversely, glucocorticoid therapy significantly increases the risk of precipitating or aggravating scleroderma renal crisis in systemic sclerosis patients. Because standard treatments for these two conditions conflict directly, clinicians must proceed with utmost caution. Consequently, administering empiric high-dose steroids without clear differentiation can trigger devastating renal failure. Medical teams must synthesize clinical symptoms, baseline renal parameters, and blood pressure trends to formulate safe therapeutic plans.
Definitive confirmation of immune-mediated thrombotic thrombocytopenic purpura requires testing for ADAMTS13 metalloprotease deficiency. In typical scleroderma renal crisis, vascular endothelial injury drives localized microvascular thrombi, leaving plasma ADAMTS13 activity levels relatively preserved above twenty percent. In stark contrast, acquired TTP arises when circulating autoantibodies neutralize ADAMTS13 activity below ten percent. In the reported index patient, laboratory assays revealed undetectable enzyme activity below one percent alongside an inhibitor level of 1.0 Bethesda units per milliliter. Consequently, these definitive findings confirmed an acquired autoimmune etiology rather than isolated scleroderma vasculopathy. Nevertheless, specialized ADAMTS13 testing frequently requires several days to return definitive results in standard hospital settings. Clinicians cannot afford to delay lifesaving interventions while awaiting confirmatory laboratory reports. Therefore, validated clinical prediction models such as the PLASMIC score provide indispensable guidance during initial decision-making. Moreover, integrating clinical scoring systems allows teams to calculate the pretest probability of severe ADAMTS13 deficiency rapidly. Clinicians can thus initiate targeted therapy with confidence while awaiting formal serological validation.
Clinicians frequently encounter profound hesitation when contemplating systemic corticosteroids in scleroderma patients. Historical cohort studies confirm that moderate-to-high doses of prednisone, exceeding fifteen milligrams daily, significantly increase the risk of triggering scleroderma renal crisis. However, withholding immunosuppressive therapy during active thrombotic thrombocytopenic purpura allows ongoing platelet-rich microthrombosis to cause fatal tissue ischemia. In the reported case, the clinical team initially withheld glucocorticoids, electing to start daily therapeutic plasma exchange alone. Unfortunately, the patient subsequently suffered clinical deterioration, developing severe thrombocytopenia of 8,000 platelets per microliter, acute dysarthria, right hemiparesis, and facial palsy. Furthermore, her neutralizing antibody titer climbed to 1.9 Bethesda units per milliliter. This clinical worsening demonstrates that therapeutic plasma exchange alone may fail to suppress vigorous autoantibody synthesis. Fortunately, anti-centromere antibody positivity denotes limited cutaneous involvement and correlates with a remarkably low baseline risk for scleroderma renal crisis. Therefore, judicious administration of high-dose corticosteroids remains reasonable when acquired TTP threatens patient survival and estimated renal crisis risk remains low.
When refractory autoimmune microangiopathy resists initial measures, aggressive multimodal therapy becomes paramount. Therapeutic plasma exchange serves as the cornerstone of acute management, effectively removing circulating ultra-large von Willebrand factor multimers and anti-ADAMTS13 antibodies. Concurrently, plasma infusion replenishes functional enzyme molecules to restore physiological hemostasis. However, refractory or deteriorating cases demand prompt immunosuppressive escalation. In this illustrative patient, specialists successfully added intravenous methylprednisolone pulse therapy alongside targeted rituximab infusions while continuing plasma exchange. Rituximab, an anti-CD20 monoclonal antibody, rapidly depletes antibody-producing B lymphocytes and eliminates the underlying autoimmune driver. Following this coordinated intervention, the patient demonstrated complete hematological recovery without experiencing further neurological deficits. In addition, long-term monitoring confirmed sustained clinical remission without relapse over a four-year follow-up period. This favorable outcome emphasizes that combining targeted biologic B-cell depletion with plasma exchange offers robust disease control in refractory connective tissue disease-associated microangiopathies. Consequently, multidisciplinary collaboration between hematologists and rheumatologists remains essential to execute timely escalation protocols and safeguard vital organ function.
Scleroderma renal crisis typically features new-onset malignant hypertension, rapid renal failure, and mild microangiopathic changes. In contrast, acquired thrombotic thrombocytopenic purpura presents with severe thrombocytopenia, profound microangiopathic hemolytic anemia, and fluctuating neurological signs without marked hypertension. Furthermore, testing reveals an ADAMTS13 activity below ten percent in TTP, whereas patients with scleroderma renal crisis maintain near-normal enzyme levels. Consequently, distinguishing these two emergencies guides rapid, lifesaving therapeutic decisions in clinical practice.
High-dose corticosteroids significantly increase the risk of precipitating scleroderma renal crisis, especially in patients with early diffuse cutaneous systemic sclerosis. Therefore, rheumatologists exercise extreme caution before administering systemic steroids. However, clinicians may selectively administer glucocorticoids alongside plasma exchange when they strongly suspect acquired TTP. In addition, patients possessing anti-centromere antibodies carry a substantially lower baseline risk for renal crisis. Consequently, physicians must carefully weigh severe neurological and hematological risks against potential renal complications.
Rituximab targets CD20-positive B lymphocytes, effectively halting the production of inhibitory anti-ADAMTS13 autoantibodies in refractory acquired TTP. Clinicians administer rituximab when patients show poor initial responses to therapeutic plasma exchange and standard immunosuppression. Furthermore, rituximab accelerates hematological recovery and dramatically reduces long-term relapse rates in complex autoimmune microangiopathies. Thus, incorporating rituximab into early multimodal rescue therapy offers critical protection against progressive microvascular ischemia, fatal end-organ failure, and recurrent thrombotic events.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A rare case report highlights acquired TTP in a patient with limited cutaneous systemic sclerosis. Clinicians must navigate complex differentials between TTP and scleroderma renal crisis, balance steroid-induced crisis risks, and rapidly deploy therapeutic plasma exchange alongside rituximab to ensure remission.
Today

A large cohort study demonstrates that fetal growth restriction in a first pregnancy raises maternal cardiovascular risk within five years postpartum, including elevated rates of heart failure, stroke, and myocardial infarction. Clinicians must initiate proactive postpartum screening and cardiovascular prevention.
Yesterday

A landmark study reveals that intermittent hypoxia drives vascular dysfunction via tissue-specific epigenetic aging and p16-mediated cellular senescence, highlighting novel senolytic targets for sleep apnea.
Today

A paired cadaveric study compared triple and quintuple percutaneous Achilles tendon lengthening. While quintuple hemisection showed numerically greater elongation, differences were not statistically significant.
Yesterday
Diabetic retinopathy remains a leading cause of preventable visual impairment. This review outlines key strategies for screening, systemic risk factor control, advanced diagnostic imaging, and timely specialist referrals within primary and multidisciplinary care models.
Today
