

Loading, please wait...
Loading, please wait...

Acquired hemophilia A (AHA) is a rare autoimmune bleeding disorder. It occurs when autoantibodies inhibit clotting factor VIII in individuals with no previous bleeding history. While uncommon, Acquired Hemophilia A ICH presents a life-threatening emergency for patients. Therefore, prompt clinical recognition is essential to prevent high morbidity and mortality. Understanding the diagnostic clues and management options is vital for every clinician in emergency and critical care settings.
Clinicians must suspect AHA in elderly patients presenting with sudden, unexplained bleeding. Specifically, an isolated, prolonged activated partial thromboplastin time (aPTT) serves as the primary diagnostic clue. Because other clotting tests like prothrombin time usually remain normal, physicians might overlook the diagnosis. However, an aPTT mixing study often reveals the presence of inhibitors when the aPTT fails to correct. Furthermore, specific assays for factor VIII activity confirm the diagnosis by showing markedly reduced levels. Early detection allows for the immediate initiation of specialized therapies, which is crucial for patient survival.
The main priority in managing Acquired Hemophilia A ICH is achieving rapid hemostasis. Standard factor VIII replacement often fails because the circulating inhibitors neutralize the infused factor. Consequently, clinicians must use bypassing agents like recombinant activated factor VII (rFVIIa) or activated prothrombin complex concentrate (aPCC). In addition to hemostatic therapy, starting immunosuppressive treatment is vital. This therapy aims to eradicate the autoantibodies and restore normal clotting function over time. Although some patients require surgery for hematoma evacuation, doctors must balance the risks of rebleeding against the potential benefits of the procedure.
Early intervention significantly improves survival rates in these complex cases. Neurologists and hematologists should collaborate closely during the acute phase to manage coagulopathy and intracranial pressure. Thus, monitoring aPTT and initiating bypassing agents immediately can save lives. While the overall survival rate remains around 62%, prompt recognition and aggressive treatment offer the best chance for neurological recovery.
The hallmark finding is an isolated prolongation of the activated partial thromboplastin time (aPTT) that does not correct during a mixing study, suggesting the presence of an inhibitor.
Autoantibodies in AHA specifically neutralize factor VIII, making standard replacement ineffective. Clinicians must use bypassing agents like rFVIIa or aPCC to promote clotting through alternative pathways.
Recent reviews indicate an overall survival rate of approximately 62%. However, only about 30% of survivors achieve full neurological recovery, highlighting the severity of the condition.
Disclaimer: This content is for informational and educational purposes only. It does not constitute medical advice or a professional recommendation. Clinicians should verify all information and treatment protocols with official medical literature and specialized consultants. Refer to the latest local and national guidelines for clinical practice.
References
Witten G et al. Intracranial hemorrhage in acquired hemophilia A: illustrative case. J Neurosurg Case Lessons. 2026 May 11. doi: undefined. PMID: 42114158.
Tiede A, et al. International recommendations on the diagnosis and treatment of acquired hemophilia A. Haematologica. 2020;105(7):1791-1801.
Kruse-Jarres R, et al. Acquired hemophilia A: Updated review of evidence and treatment guidance. Am J Hematol. 2017;92(7):695-705.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A comprehensive review of intracranial hemorrhage in acquired hemophilia A, focusing on diagnosis through prolonged aPTT and management using bypassing agen...
5 months ago

The TREM-AB open-label pilot study evaluated a wearable passive nonlinear vibration absorber for essential tremor. The Nonlinear Energy Sink bracelet reduced clinical Fahn-Tolosa-Marin tremor scores by 32.1% and electrophysiological tremor power by 49.2% with no adverse effects reported.
Today

A population-based study of 20,928 children reveals that small vulnerable newborns face sex-divergent mental capital outcomes at ages 6-7: term SGA girls show higher behavioral difficulties and lower resilience, while preterm non-SGA boys experience increased behavioral problems.
Today

A landmark study details how an enterprise pediatric remote patient management model expanded from a single cardiology pilot to 16 diverse specialty programs by combining centralized digital operations with specialty clinical leadership.
Today
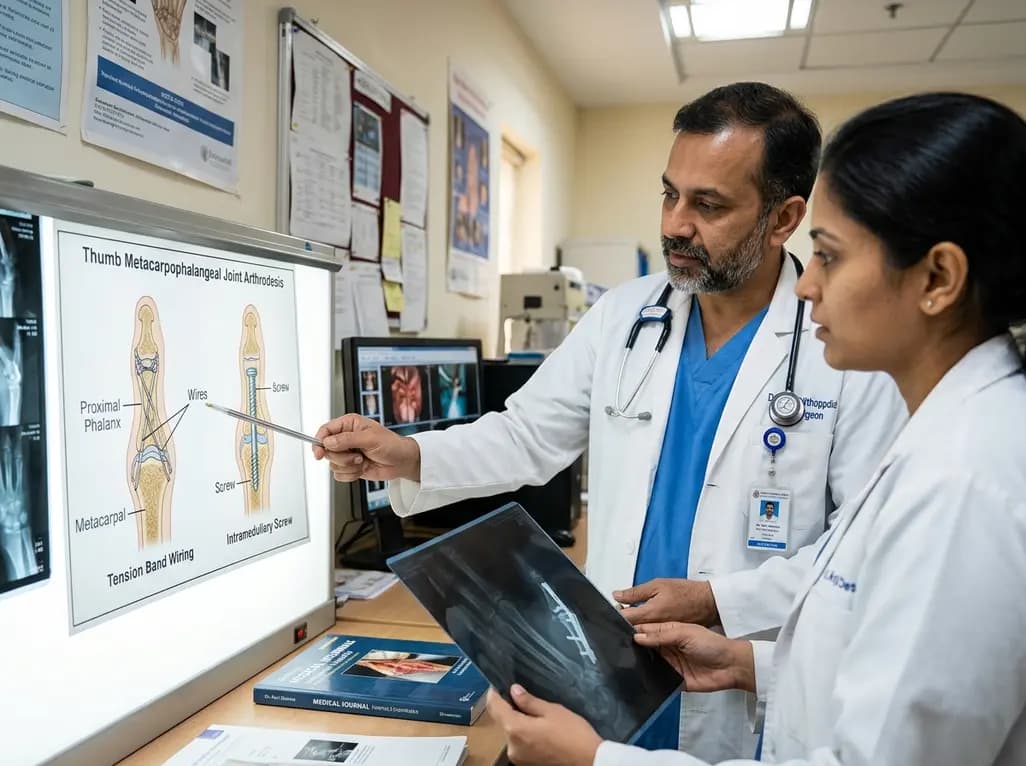
A comparative review of tension band wiring and intramedullary screw fixation in thumb metacarpophalangeal arthrodesis, evaluating union rates, hardware complications, and clinical outcomes.
Today

A breakthrough ultrathin multimodal sensor decouples physical hemodynamic monitoring from disposable electrochemical calibration, achieving long-term wearable glucose prediction with 81.36% accuracy and a 9.12% MARD. This offers a robust, drift-free solution for outpatient metabolic surveillance.
Today
