

Loading, please wait...
Loading, please wait...
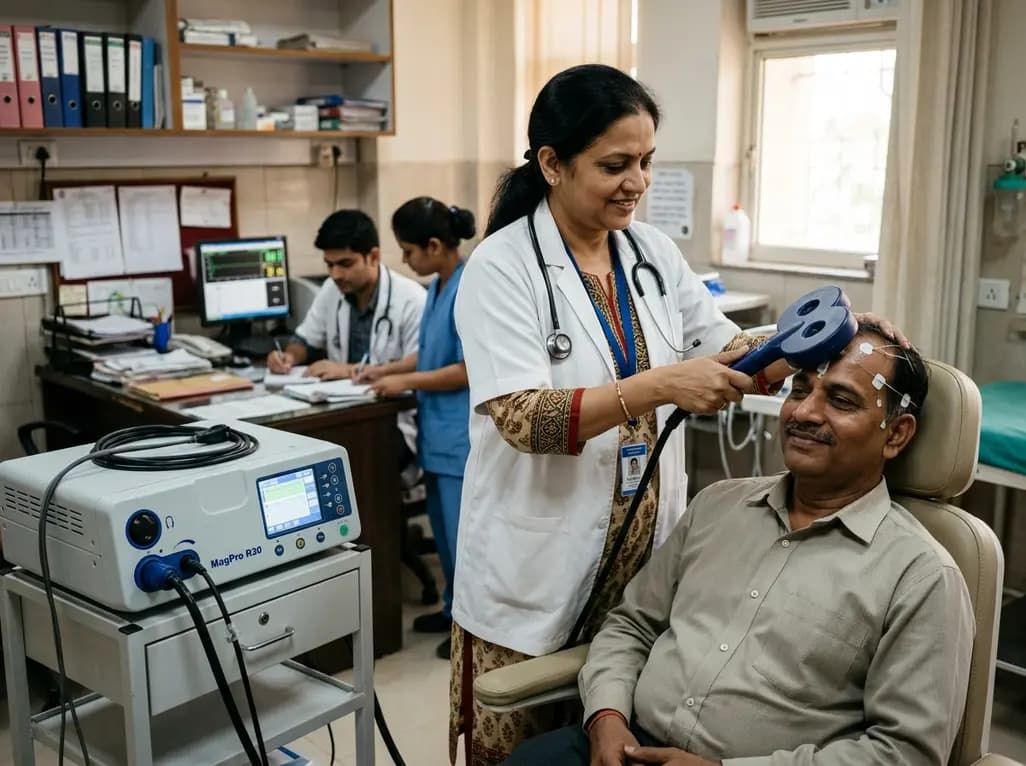
Major depressive episodes represent a substantial contributor to psychiatric disability worldwide. Clinicians frequently encounter patients who fail to respond to multiple consecutive antidepressant trials. Treatment-resistant depression occurs commonly in both unipolar major depressive disorder and bipolar II depression. Conventional repetitive transcranial magnetic stimulation provides proven relief for these difficult presentations. However, standard protocols require daily outpatient visits over four to six consecutive weeks. This demanding schedule creates severe logistical burdens for working adults and distant patients. Consequently, clinical investigators have developed accelerated intermittent theta burst protocols to compress neuromodulation delivery. Delivering multiple daily sessions within a single week shortens therapy significantly. Recently published naturalistic data demonstrate that a five-day schedule effectively alleviates treatment resistance in routine mental health services. Therefore, this intensive approach offers meaningful hope for patients needing urgent therapeutic interventions without prolonged treatment delays. Accelerated scheduling directly addresses barriers to care, thereby facilitating prompt symptom stabilization in clinical practice. Moreover, shorter treatment courses improve overall patient engagement and diminish clinical dropouts during interventional therapy.
Intermittent theta burst stimulation mimics endogenous hippocampal theta rhythms to promote long-term potentiation. The protocol delivers rapid bursts of high-frequency pulses to the left dorsolateral prefrontal cortex. This focal cortical excitation enhances frontostriatal connectivity and modulates dysfunctional affective circuits. Standard daily protocols induce neuroplastic adaptations gradually over several weeks. In contrast, accelerated scheduling leverages spaced synaptic learning principles to accelerate cumulative neuroplastic changes. Applying multiple stimulation trains each day with fifty-minute rest intervals optimizes synaptic consolidation. Neuroscientists hypothesize that these structured intervals prevent intracellular calcium saturation and avoid long-term depression of synaptic strength. In addition, repetitive activation throughout the day strengthens prefrontal control over deeper subcortical limbic structures. Thus, accelerated protocols achieve comparable biological engagement in a fraction of traditional treatment duration. Moreover, functional neuroimaging confirms that theta burst stimulation normalizes aberrant hyperactivity in the subgenual anterior cingulate cortex. Consequently, compressing thirty sessions into five consecutive days maximizes synaptic reorganization while respecting cellular recovery constraints. Clinicians can harness these fundamental biological mechanisms to reverse persistent network dysfunction in resistant patients.
A recent prospective naturalistic cohort study evaluated forty-six adult outpatients suffering from treatment-resistant depression in routine practice. The clinical sample included individuals diagnosed with unipolar major depressive disorder and bipolar II disorder. Participants completed thirty intermittent theta burst sessions across five consecutive business days. Each daily schedule comprised six discrete stimulation sessions separated by fifty-minute inter-session intervals. During each session, technicians delivered six hundred pulses at eighty percent of the resting motor threshold. Accordingly, patients accumulated eighteen thousand total therapeutic magnetic pulses over the five-day treatment course. Clinical staff assessed depression severity using the seventeen-item Hamilton Depression Rating Scale at baseline, post-treatment, and two-month follow-up. Furthermore, secondary measures captured self-reported depressive symptoms, generalized anxiety, and global clinical improvement. Naturalistic studies provide realistic benchmarks because they include patients with significant psychiatric comorbidities. In this investigation, clinical teams maintained concurrent psychotropic regimens while administering intensive neuromodulation safely. Therefore, this prospective design successfully demonstrated practical feasibility within typical psychiatric outpatient facilities. Clinicians confirmed that structured protocols integrate smoothly into ambulatory treatment workflows.
The study recorded meaningful symptom reductions across all longitudinal assessment points. Immediately post-treatment, 28.3 percent of participants achieved formal clinical response on the Hamilton Depression Rating Scale. Concurrently, 26.1 percent attained full clinical remission within five days. Importantly, therapeutic gains continued to accumulate following treatment completion. At the two-month follow-up assessment, the response rate reached 37.0 percent. Similarly, the remission rate climbed to 32.6 percent at two months. Linear mixed-effects models verified statistically significant improvements over time. Clinicians observed parallel reductions on the Patient Health Questionnaire-9 and Generalized Anxiety Disorder-7 scales. Moreover, global clinical impressions reflected broad symptomatic recovery. Clinicians rated 52.2 percent of participants as clinically improved post-treatment and 60.9 percent improved at two months. Treatment-resistant depression frequently co-occurs with debilitating anxiety, which often undermines pharmacotherapy. By alleviating anxious distress alongside core depressive symptoms, intensive prefrontal stimulation provides comprehensive mood stabilization. These longitudinal trajectories demonstrate that accelerated stimulation triggers enduring neuroplastic reorganization rather than fleeting symptomatic relief. Consequently, patients sustain substantial therapeutic improvements over extended observation periods.
Tolerability represents a critical priority when delivering multiple daily stimulation sessions. Encouragingly, the prospective cohort reported an excellent tolerability profile throughout the five-day protocol. The most frequent adverse effect was transient stimulation-site pain during active coil delivery. Patients managed this localized discomfort easily without requiring prescription analgesics or protocol modifications. Importantly, investigators recorded no serious adverse events, seizures, or cognitive deficits. Furthermore, participants with bipolar II depression experienced no hypomanic switches during treatment or follow-up. This finding is particularly vital because antidepressant pharmacotherapy frequently triggers mood instability in bipolar populations. Patient adherence remained remarkably high, confirming that outpatients readily complete compressed schedules. However, successful clinical execution requires attentive nursing staff and restful waiting suites between sessions. Clinics must also maintain strict coil positioning standards to deliver consistent stimulation across successive treatments. In summary, five-day accelerated delivery combines excellent clinical safety with substantial operational efficiency in psychiatric settings. Hence, healthcare providers can confidently recommend this intervention to appropriate patients.
Standard transcranial magnetic stimulation requires single daily sessions administered five days per week over four to six consecutive weeks. In contrast, accelerated intermittent theta burst stimulation delivers multiple sessions each day, typically separated by fifty-minute rest intervals. This compressed schedule allows clinical teams to administer thirty total sessions across five consecutive business days. Consequently, patients achieve meaningful symptomatic relief substantially faster, which markedly reduces logistical barriers and overall treatment burden.
Yes, the prospective cohort included adults diagnosed with both unipolar major depressive disorder and bipolar II disorder presenting with treatment resistance. Participants with bipolar II depression experienced significant improvements in depressive severity without encountering treatment-emergent affective switches into hypomania. Longitudinal evaluations showed sustained therapeutic responses and remissions at two-month follow-up. While larger randomized sham-controlled trials remain necessary, these findings suggest that accelerated protocols provide a safe, effective option for bipolar II depression.
Clinical data indicate that accelerated theta burst stimulation is well tolerated during routine outpatient administration. The most frequently documented adverse effect is transient scalp discomfort or mild pain at the stimulation site during active trains. These sensations resolve rapidly after each session without requiring medical analgesia. Furthermore, the naturalistic cohort study observed no seizures, serious neurological events, cognitive impairments, or treatment discontinuations, underscoring the general safety of intensive delivery schedules in real-world psychiatric settings.
Disclaimer: This content is for informational and educational purposes only and does not constitute medical advice, diagnosis, or treatment. Healthcare professionals should exercise their clinical judgment when applying this information. Clinical presentations and institutional protocols may vary across settings. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A prospective naturalistic cohort study demonstrates that a 5-day accelerated intermittent theta burst stimulation protocol achieves significant response and remission rates for treatment-resistant depression in routine clinical practice, showing sustained benefits and excellent tolerability at two-month follow-up.
Today

An exploratory pilot study evaluates metoprolol pharmacokinetics across cisgender males, cisgender females, and transgender women on gender-affirming hormone therapy. Findings reveal distinct drug disposition trends, emphasizing the critical need for genotype-stratified research in transgender cardiovascular care.
Today

Maharashtra has initiated the appointment of two dedicated special public prosecutors in every district alongside a joint police-health SOP to fast-track PCPNDT and MTP cases. Medical imaging centers, radiologists, and obstetricians must strengthen statutory documentation and audit preparedness.
Today
A prospective study evaluates percutaneous renal denervation in high-risk patients with resistant hypertension, demonstrating significant short-term blood pressure reduction alongside notable procedural considerations.
Today
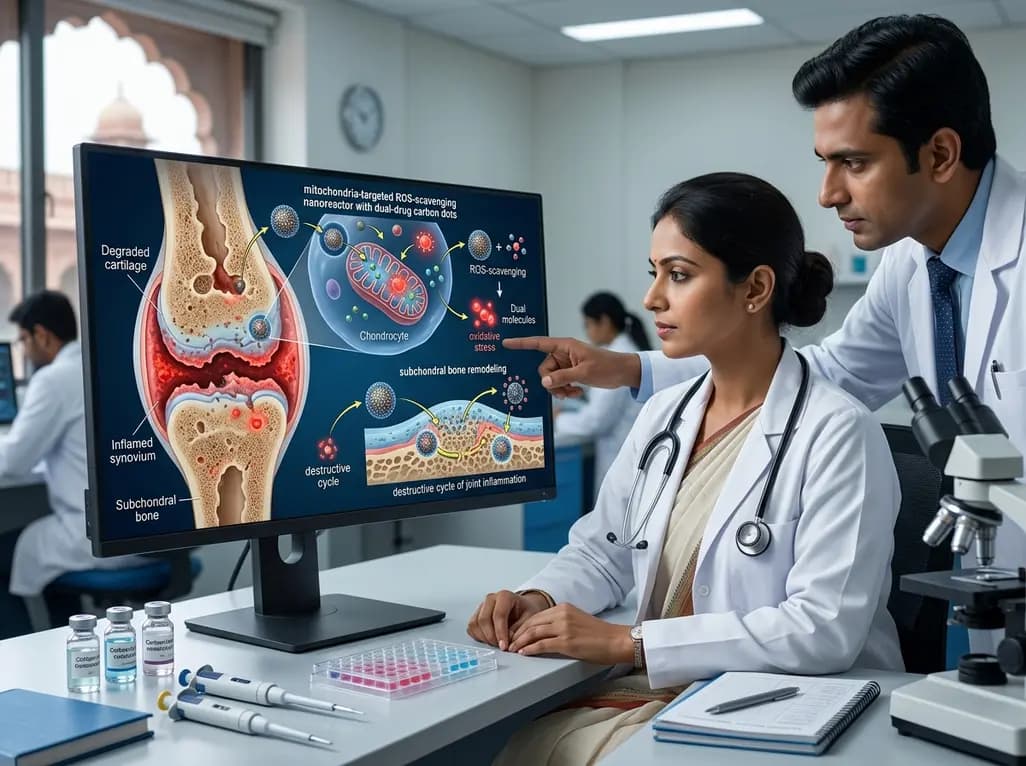
A novel mitochondria-targeted ROS-scavenging nanoreactor with dual-drug carbon dots provides a multi-mechanism strategy for osteoarthritis therapy. By neutralizing oxidative stress and remodeling subchondral bone, this platform breaks the destructive cycle of chronic joint inflammation and cartilage degeneration.
Today

A modified Delphi study identified crucial clinical and research priorities for older transgender adults. Key findings emphasize provider education, screening for social isolation, navigation of community resources, and long-term evaluation of gender-affirming hormone therapy safety during the aging process.
Today
