

Loading, please wait...
Loading, please wait...
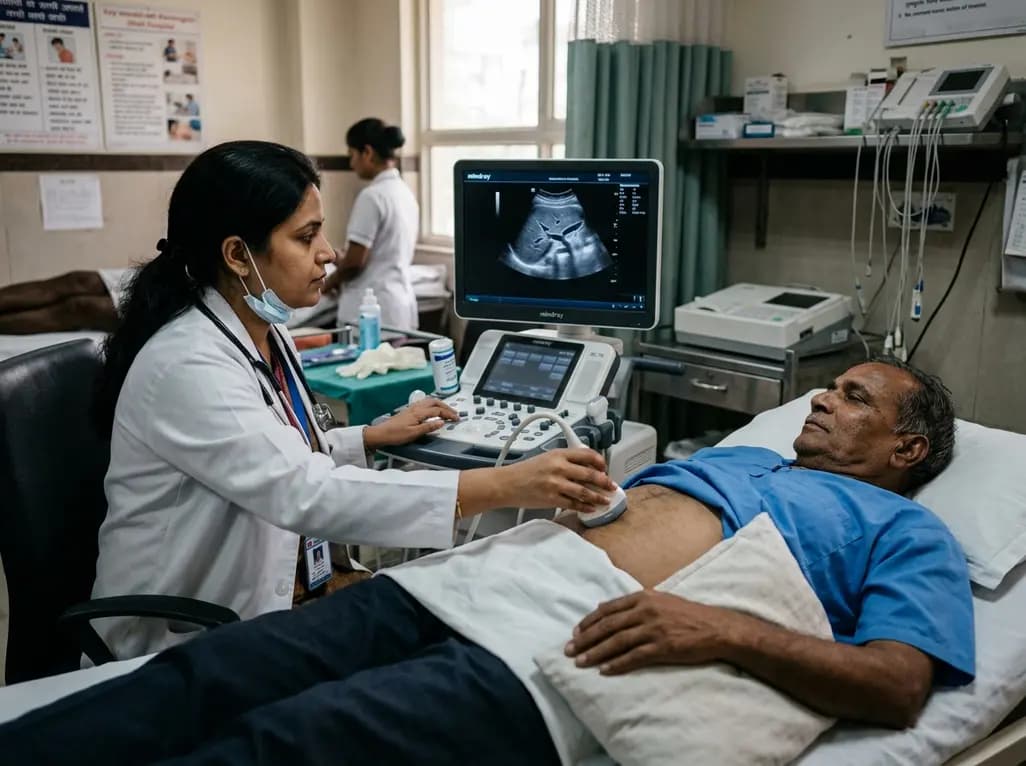
Rheumatoid arthritis is a systemic autoimmune condition that primarily inflames joints. However, systemic inflammation and disease-modifying therapies frequently provoke gastrointestinal and hepatic manifestations. Clinicians increasingly recognize that digestive complications and hepatic steatosis severely impair patient quality of life. Therefore, healthcare teams require dependable, non-invasive imaging tools to identify early organ involvement. Evaluating the clinical role of abdominal ultrasound in rheumatoid arthritis provides vital clarity regarding subclinical hepatobiliary and intestinal abnormalities. This accessible imaging technique offers rapid parenchymal assessment without radiation hazards. Consequently, integrating sonography into routine patient monitoring empowers clinicians to tailor therapeutic strategies and prevent long-term organ damage.
Hepatic dysfunction represents a significant clinical concern during long-term rheumatoid arthritis management. Chronic systemic inflammation can trigger reactive hepatopathy, steatosis, and parenchymal remodeling. In addition, disease-modifying agents like methotrexate frequently induce elevated liver enzymes and hepatocellular stress. In clinical studies, investigators observed that bright or bright coarse liver echotexture was significantly more prevalent among arthritis patients than healthy controls. Specifically, patients receiving methotrexate-based therapy demonstrated a higher incidence of parenchymal hyperechogenicity. This sonographic appearance typically indicates diffuse fatty infiltration or microvascular alteration. However, conventional serum transaminase measurements frequently fail to detect emerging structural damage. Transaminases can fluctuate unpredictably or remain completely normal despite progressive parenchymal steatosis. Therefore, relying solely on periodic blood tests may delay critical therapeutic adjustments. Clinicians must actively detect steatotic remodeling before extensive hepatocellular injury develops. Consequently, assessing parenchymal architecture alongside standard biochemical panels provides essential clinical context for safe immunosuppressive therapy.
Transabdominal sonography provides a practical, non-invasive method for evaluating upper abdominal organs in chronic arthritis. Notably, high-resolution B-mode ultrasound readily identifies hepatic echogenicity variations, vascular blurring, and parenchymal coarseness. In clinical practice, detecting a bright or bright coarse liver serves as a dependable indicator of steatosis. However, conventional sonography provides qualitative observations rather than direct quantitative measurements of stiffness. When sonographers observe abnormal hepatic echogenicity, clinicians can immediately re-evaluate pharmacotherapy and screen for underlying metabolic dysfunction. Furthermore, ultrasound involves zero ionizing radiation and remains widely accessible across medical centers. Routine sonographic surveillance effectively bridges the diagnostic gap between standard laboratory tests and invasive procedures. Physicians can monitor structural trends over time to confirm whether parenchymal changes improve after medication adjustments. In addition, routine abdominal imaging helps exclude biliary stasis, cholelithiasis, and splenomegaly. Thus, incorporating liver sonography into regular follow-up schedules helps clinicians detect structural hepatic shifts early.
Gastrointestinal symptoms represent an underappreciated comorbidity burden in rheumatoid arthritis patients. Recent comparative studies show that gastroesophageal reflux disease and irritable bowel syndrome occur much more frequently in arthritis cohorts than in healthy controls. Specifically, clinical assessments demonstrate a reflux disease prevalence exceeding fifty percent among arthritis patients. Similarly, irritable bowel syndrome affects nearly thirty percent of these individuals. Several distinct mechanisms drive this elevated symptom burden. First, sustained systemic cytokine release alters gastrointestinal motility and visceral sensitivity. Second, regular use of non-steroidal anti-inflammatory drugs and oral corticosteroids compromises gastric mucosal defenses. Consequently, patients frequently endure persistent heartburn, acid regurgitation, abdominal cramping, and irregular bowel habits. Furthermore, disruptions in the intestinal microbiome exacerbate mucosal permeability and fuel systemic immune activation. Clinicians must routinely ask about digestive symptoms during outpatient follow-ups. Therefore, structured symptom scoring allows clinicians to initiate timely proton pump inhibitors, prokinetics, or dietary guidance before severe mucosal ulcerations occur.
High-resolution bowel ultrasound has gained substantial recognition as an effective imaging tool for primary inflammatory bowel diseases. High-frequency transducers clearly visualize bowel wall stratification, mural thickness, and mesenteric blood flow. However, recent scientific findings define practical limitations regarding its routine use in rheumatoid arthritis. In asymptomatic patients, universal bowel ultrasound screening yields minimal actionable findings. Although functional disorders like irritable bowel syndrome occur frequently, they cause neuromuscular dysmotility rather than transmural structural inflammation. Consequently, bowel architecture appears completely normal on sonography unless concomitant ulceration or diverticulitis exists. Clinicians should therefore reserve bowel ultrasound exclusively for patients who present with alarm features. Critical red-flag signs include unintentional weight loss, gastrointestinal bleeding, severe localized pain, or chronic diarrhea. In these targeted scenarios, focused sonography rapidly identifies mural thickening, inflammatory strictures, or abscesses. Therefore, combining validated clinical symptom questionnaires with targeted physical examinations represents the most cost-effective diagnostic strategy for managing luminal gastrointestinal health.
Standard transabdominal sonography detects hepatic steatosis accurately, but it cannot quantify mechanical liver stiffness. To overcome this limitation, clinicians utilize vibration-controlled transient elastography as an advanced non-invasive modality. When conventional ultrasound demonstrates a bright or bright coarse liver, elastography measures shear wave velocity to grade fibrosis precisely. Recent data indicate that significant hepatic fibrosis of grade F2 or greater occurs in approximately five percent of screened arthritis patients. Nevertheless, detecting this vulnerable subgroup remains clinically essential. Methotrexate-induced fibrogenesis and fatty liver disease can advance silently without noticeable symptoms. Transient elastography provides objective numerical values in kilopascals, establishing an accurate baseline for longitudinal monitoring. Moreover, this bedside procedure avoids the procedural risks and discomfort of percutaneous liver biopsy. When elastography reveals elevated stiffness scores, physicians can safely modify immunosuppressive dosing or refer patients to hepatology specialists. Conversely, normal elastography results reassure rheumatologists, enabling them to maintain effective disease-modifying regimens safely. Therefore, combining routine ultrasound with reflexive transient elastography optimizes diagnostic precision and patient safety.
Routine abdominal ultrasound detects parenchymal liver changes, such as hepatic steatosis and coarseness, which frequently develop from systemic inflammation or long-term methotrexate therapy. Because standard liver enzyme panels often remain normal despite structural liver remodeling, ultrasound provides essential anatomic visualization without radiation exposure. Consequently, periodic sonographic screening enables clinicians to identify early drug-induced liver injury, optimize medication dosages, and introduce targeted lifestyle interventions before advanced hepatic fibrosis or irreversible cirrhosis can develop.
Bowel ultrasound is highly effective for transmural inflammation but has minimal diagnostic utility in asymptomatic arthritis patients. Functional gastrointestinal disorders, such as irritable bowel syndrome and dyspepsia, stem from altered neuromuscular motility and mucosal sensitivity rather than gross structural bowel wall changes. Therefore, routine bowel sonography in asymptomatic individuals adds substantial healthcare costs without improving clinical outcomes. Physicians should instead reserve bowel ultrasound for symptomatic patients who exhibit alarming signs like rectal bleeding or weight loss.
When an ultrasound reveals a bright or bright coarse liver, clinicians should immediately calculate metabolic risk factors and review ongoing medication lists. Rheumatologists ought to evaluate methotrexate cumulative dosage and alcohol consumption while ordering transient elastography to quantify liver stiffness. If elastography demonstrates significant fibrosis (stage F2 or greater), physicians should promptly adjust immunosuppressive therapy, consult a hepatologist, and initiate metabolic counseling to prevent progressive hepatic decompensation and preserve long-term liver function.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Rheumatoid arthritis frequently involves hepatic and gastrointestinal comorbidities. Discover why abdominal ultrasound is recommended for routine hepatic surveillance alongside liver enzymes, while bowel ultrasound is reserved for symptomatic presentations.
last month
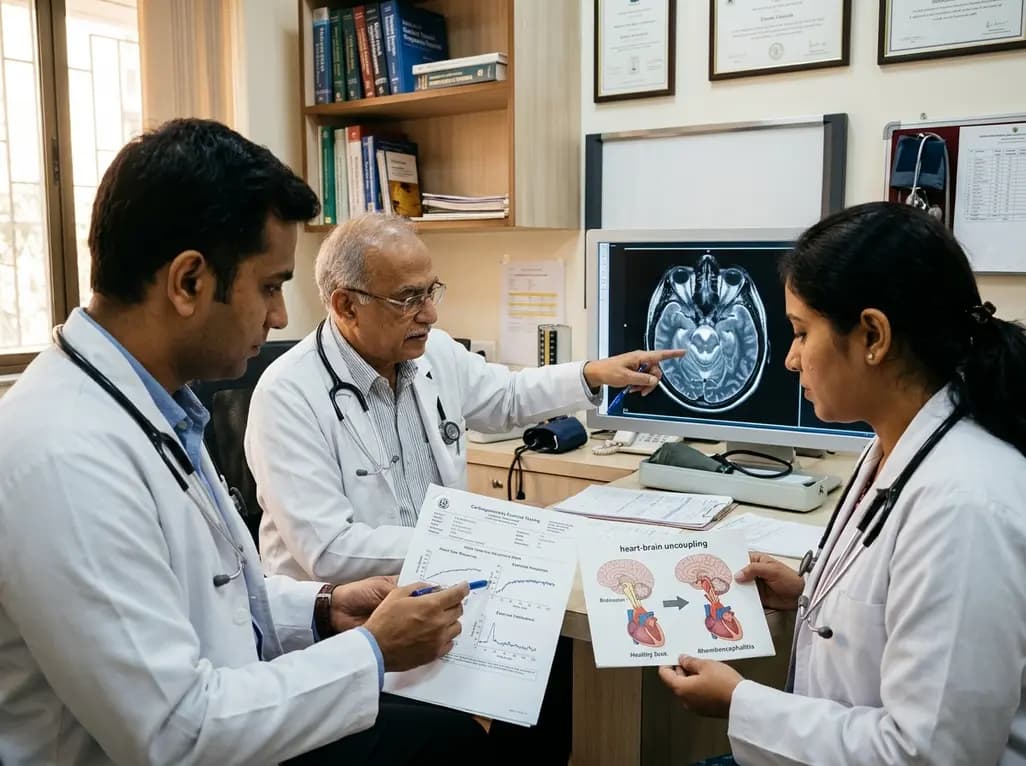
Central chronotropic incompetence is an underrecognized sequela of rhombencephalitis causing exertional dyspnea despite normal resting cardiac function. Cardiopulmonary exercise testing unmasks this heart-brain uncoupling, guiding rate-responsive pacing and targeted rehabilitation.
Today

A landmark study reveals that lipid-rich malignant ascites alters the T-cell metabolic transcriptome, causing cholesterol efflux and impaired fatty acid oxidation. This suppresses TCR signalling and blocks BiTE immunotherapy, while lipid depletion restores antitumour cytotoxicity in ovarian cancer.
Today
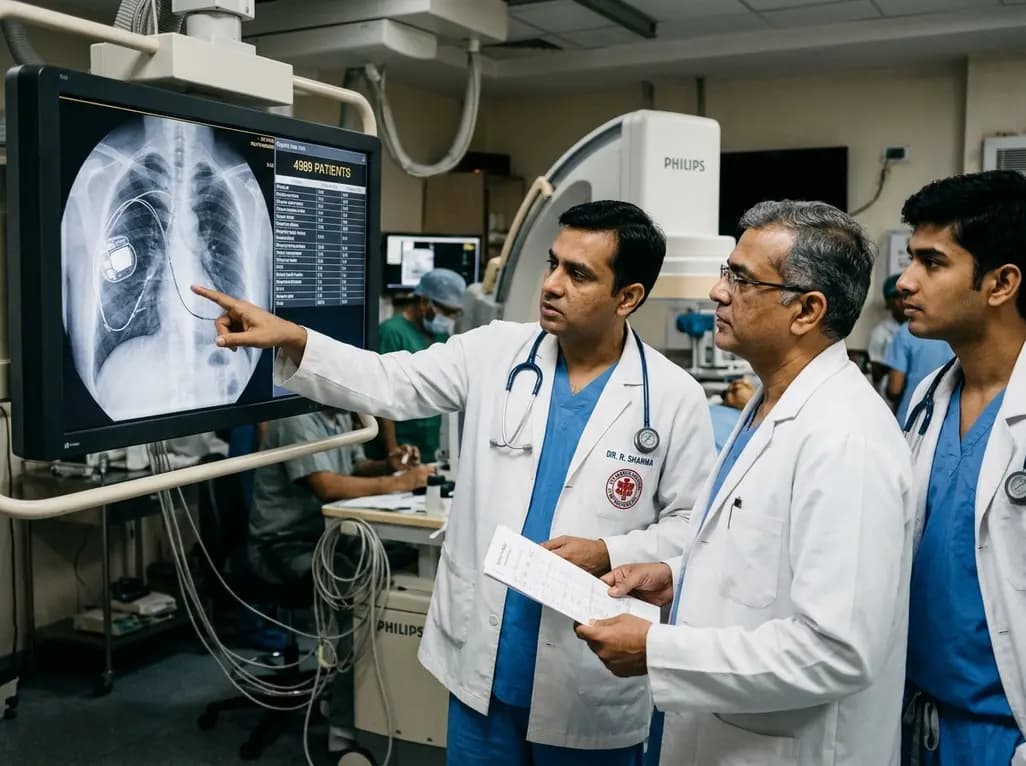
A registry study of 4,989 patients evaluates transvenous lead extraction for right-sided cardiac devices. Despite longer dwell times and older leads, right-sided extractions achieve high procedural success and comparable safety to left-sided approaches.
Today
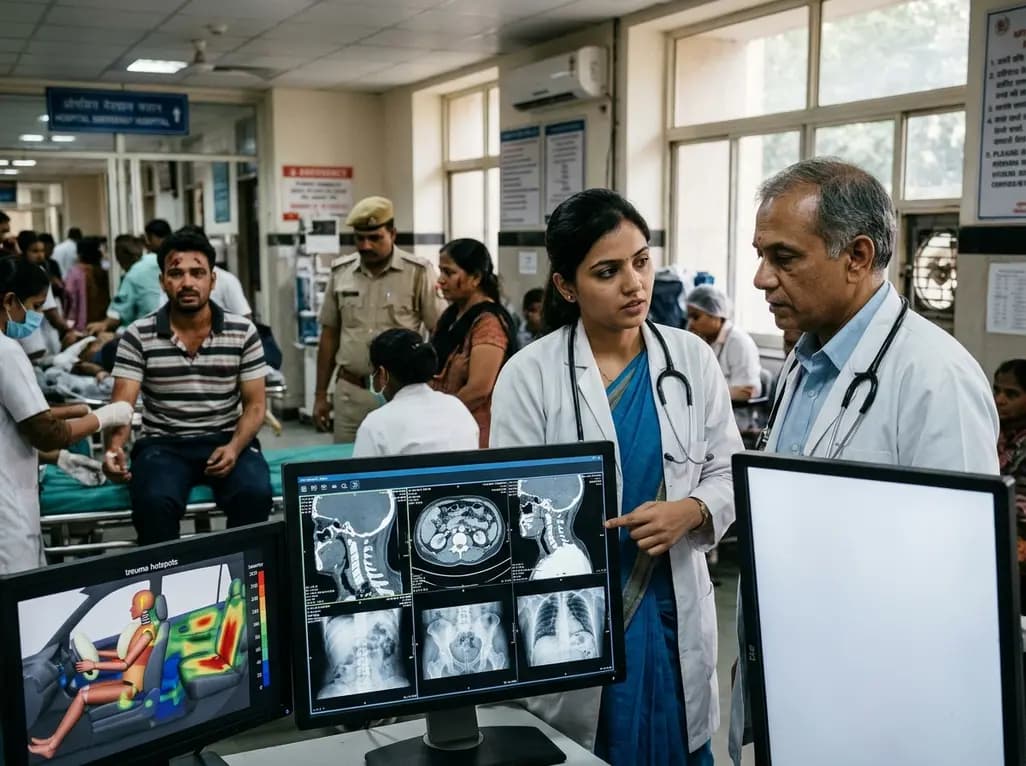
Recent crash analyses demonstrate significant variations in traffic injury severity across vehicle seating positions. Electric vehicle passengers face disproportionately higher trauma risks than drivers, particularly during airbag deployments, demanding adapted emergency assessment and clinical vigilance.
Today

Understand the causal role of Lipoprotein(a) in cardiovascular disease, why international guidelines recommend once-in-a-lifetime molar testing, and the clinical implications of recent phase 3 RNA outcome trials.
Today
