

Loading, please wait...
Loading, please wait...

Digital technology has rapidly transformed modern psychiatric and psychological practice. Today, AI in mental health has entered the consulting room regardless of whether clinicians actively invite it. Large language models engage hundreds of millions of users worldwide, and tens of millions turn to chatbots daily for psychological guidance. However, robust evidence regarding the clinical efficacy and safety of generative chatbots remains scarce. Because formal professional guidelines remain fragmented, practitioners frequently encounter an uncomfortable gap between patient habits and institutional policy. Neither enthusiastic adoption nor principled abstention offers a sustainable solution for modern practitioners. Instead, clinicians require structured harm-reduction strategies to address conversational tools with nuanced, evidence-informed care.
Millions of individuals now consult conversational algorithms for emotional reassurance, cognitive reframing, and stress management. Consequently, patients frequently bring algorithmically generated advice into therapeutic encounters. When a therapist ignores this digital reality, the therapeutic alliance often suffers. Furthermore, clinicians who refuse to explore automated tools forfeit vital visibility into thoughts, cognitive distortions, and coping habits that shape the patient's daily routine. Conversely, adopting unvalidated software without rigorous scrutiny introduces severe ethical and clinical vulnerabilities. Chatbots cannot replicate authentic human empathy or provide genuine relational containment. In addition, these models can generate convincing yet inaccurate clinical interpretations, commonly termed hallucinations. Therefore, mental health practitioners must acknowledge that digital technologies already shape their patients' internal narratives. By opening nonjudgmental channels of communication, providers can illuminate how patients interact with these systems between formal appointments. Ultimately, therapeutic curiosity allows clinicians to examine algorithmic advice constructively rather than allowing unvetted software to dictate emotional processing in secret.
Rather than prohibiting or endorsing conversational platforms, clinicians should adopt a structured harm reduction model. This proactive stance embeds technological inquiry directly across every phase of the therapeutic journey. First, providers can introduce technology screening during initial intake evaluations. By asking open-ended questions about digital tools, therapists create a safe space for candid disclosure. Second, clinicians must systematically integrate material chatbot usage into ongoing case formulation. For example, therapists can evaluate whether algorithmic interaction serves as an adaptive coping skill or an avoidant defensive maneuver. In addition, clinicians must delineate clear boundaries regarding acute crises. Digital algorithms cannot manage acute suicidal ideation, psychotic decompensation, or severe behavioral emergencies. Furthermore, practitioners should track digital interactions consistently across ongoing treatment sessions. Clinicians can review specific transcripts to challenge algorithm-induced reassurance seeking. Finally, therapists must address technology dependence during termination planning. Because ending therapy requires sustained self-reliance, clinicians help patients transition toward authentic human support systems rather than algorithmic substitutes.
To translate structured harm reduction into daily clinical practice, researchers proposed the practical GUIDE operational mnemonic. This conceptual framework structures clinical decision-making from preintake through final termination. First, the Gather stage encourages clinicians to collect detailed information regarding the patient's specific software usage, frequency, and functional motivation. Second, the Understand phase requires the practitioner to evaluate how synthetic interactions affect psychological functioning and relational patterns. For instance, clinicians examine whether automated dialogue relieves loneliness or fosters emotional isolation. Third, the Inform step tasks providers with educating patients on system capabilities, systemic flaws, privacy vulnerabilities, and diagnostic boundaries. Fourth, the Document phase ensures that therapists record patient disclosures, identified risks, and agreed behavioral guidelines within formal clinical notes. Accurate documentation defends clinical integrity and establishes clear medico-legal records. Finally, the Evaluate step prompts continuous clinical reassessment. Practitioners must measure whether automated software supports treatment goals or hinders emotional development over time. Thus, the GUIDE mnemonic provides an organized wrapper that balances innovation with essential therapeutic safeguards.
Clinician-initiated deployment represents an entirely separate ethical domain from patient-initiated technology use. When healthcare providers choose to introduce automated documentation tools, diagnostic aids, or algorithmic exercises, they carry elevated legal accountability. Therefore, clinicians must demand empirical evidence before embedding third-party digital tools into standard clinical workflows. In addition, obtaining informed consent remains paramount whenever automated systems handle patient health data. Patients must understand how external platforms process, store, and utilize their protected health information. Furthermore, clinicians must ensure that digital systems comply with established data confidentiality statutes and professional privacy mandates. Commercial software licenses often allow user data mining, which violates fundamental medical ethics. Practitioners must also recognize that algorithmic suggestions do not alleviate personal responsibility. Even when automated systems draft clinical summaries, the licensed clinician remains legally liable for every clinical entry. Consequently, practitioners must independently verify all algorithmic outputs prior to signing official medical charts. By maintaining strict supervision over digital tools, providers protect patient welfare while preventing dangerous regulatory violations.
Deploying artificial intelligence in clinical psychology also raises pressing concerns regarding demographic equity and algorithmic bias. Developers train foundational large language models predominantly on high-resource languages and specific demographic perspectives. Consequently, these systems frequently exhibit skewed cultural perspectives, Western-centric value systems, and subtle diagnostic biases. When marginalized patients interact with biased algorithms, they may receive inappropriate emotional advice or culturally insensitive formulations. Therefore, mental health practitioners must evaluate whether digital platforms demonstrate equitable performance across diverse socioeconomic and linguistic subgroups. Clinicians should proactively discuss cultural alignment whenever patients reference automated conversational tools. Furthermore, establishing explicit crisis management protocols remains non-negotiable. Large language models frequently fail to detect subtle nuances in suicidal risk, self-harm, or escalating intimate partner violence. Therapists must emphasize that algorithmic tools cannot replace emergency departments, suicide hotlines, or certified crisis intervention specialists. In conclusion, clinicians must advocate for transparent, culturally validated algorithms while fiercely protecting patients from automated failures during acute emergencies.
The GUIDE framework assists therapists by establishing an intentional protocol to gather data on digital platform usage during early assessments. Therapists systematically inquire about specific software, frequency, and personal motivations for using conversational tools. Consequently, clinicians uncover hidden coping habits, assess privacy vulnerabilities, and understand patient expectations. By framing this inquiry through harm reduction, providers build therapeutic trust while integrating digital behaviors directly into diagnostic formulations.
Outright prohibition often alienates patients and forces digital engagement underground, depriving clinicians of crucial diagnostic insights. When therapists forbid software usage, patients frequently withhold disclosures regarding symptoms, advice seeking, and emotional struggles between formal appointments. Conversely, maintaining an open, harm-reduction approach allows practitioners to explore algorithmic interactions collaboratively. Therapists can consequently identify misconceptions, reinforce adaptive coping techniques, and maintain relational visibility over critical factors that materially affect ongoing therapeutic recovery.
Clinicians face substantial legal risks regarding data privacy, confidentiality breaches, and professional negligence when deploying unvetted software. Commercial platforms often store user prompts on external servers, potentially violating medical confidentiality regulations and privacy statutes. Furthermore, clinicians remain entirely liable for erroneous outputs, misdiagnoses, or omissions generated by automated systems. Therefore, providers must obtain explicit informed consent, use compliant tools, and rigorously review all AI-generated content before clinical documentation.
Disclaimer: This content is for informational and educational purposes only and does not constitute medical advice. Consult a licensed healthcare professional for medical diagnosis and treatment recommendations. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





As patients increasingly turn to conversational chatbots, therapists face an unguided frontier. The proposed GUIDE framework offers a phased harm-reduction approach to assess, document, and manage patient and clinician AI use while safeguarding clinical boundaries, equity, and data privacy.
3 weeks back
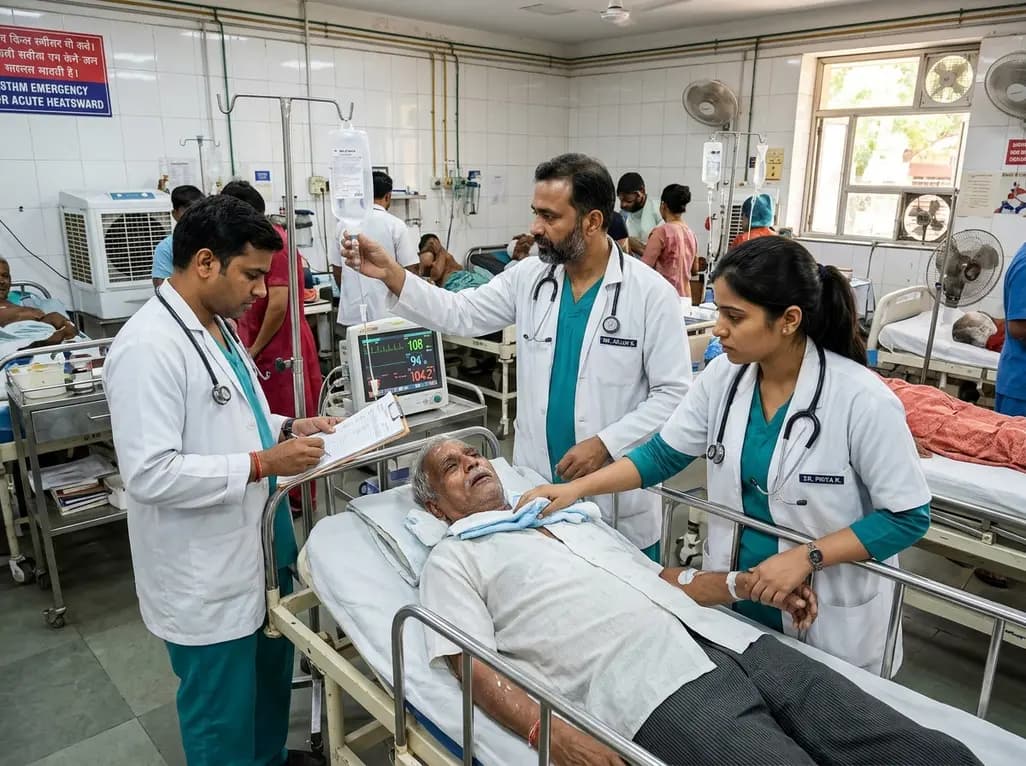
Recent epidemiological data reveals a dramatic surge in summer heat mortality driven by human-induced climate warming. This analysis explores the pathophysiological impacts on cardiac and renal systems, diagnostic dilemmas in death certification, and essential emergency cooling protocols for acute clinical care.
Today

Odisha has established India's first state-level clinical protocol specifically tailored for pregnant women with sickle cell disease. Developed with NHM and UNICEF, the framework provides structured antenatal screening, crisis mitigation, standardized referral pathways, and specialized interdisciplinary care.
Today

India is advancing preventive healthcare by integrating genomics, artificial intelligence, and quantum technologies. With the SANGAM programme sequencing one million Indian genomes, clinicians can unlock personalized therapies, detect cardiometabolic risks early, and curb the burden of diabetes and heart disease.
Today

A randomized controlled trial demonstrates that an eight-week dual-task training intervention significantly improves static and dynamic postural control over standard balance exercises in individuals with chronic ankle instability, addressing critical neurocognitive deficits during athletic and daily activities.
Today

A retrospective cohort study of 7,716 ICU patients from the MIMIC-IV database demonstrates that Gradient Boosting Decision Trees significantly outperform traditional SOFA scores in predicting in-hospital mortality among patients with sepsis and diabetes, with SHAP analysis providing clinical interpretability.
Today
