

Loading, please wait...
Loading, please wait...
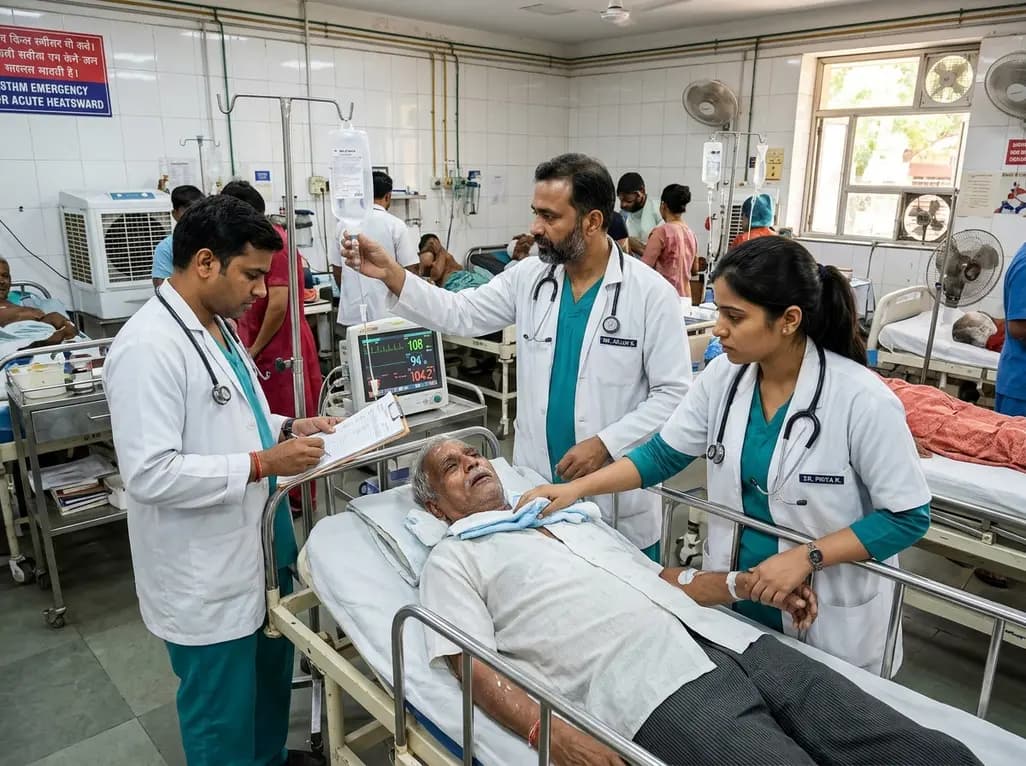
Recent epidemiological studies reveal an alarming increase in heat-related deaths across European urban centers. Scientists attribute nearly two-thirds of these excess fatalities directly to human-caused climate change. Consequently, acute care systems now face severe challenges as sustained ambient temperatures overwhelm human thermoregulatory limits. Furthermore, extreme heat operates as an invisible catalyst for catastrophic cardiovascular and renal failure. Clinicians must recognize these pathophysiological stresses early. Understanding these critical mechanisms ensures timely, lifesaving interventions during extreme environmental heat events.
A comprehensive multi-city analysis recently reported over 50,000 heat-related deaths across 854 European cities during one summer. Notably, advanced statistical modeling indicated that fossil-fuel emissions caused approximately 32,600 of these excess deaths. This mortality burden exceeded the previous benchmark from 2022 by seventy-one percent. Researchers compared observed mortality against counterfactual simulations of a world without anthropogenic warming. Consequently, they proved that the proportion of thermal deaths attributable to climate change rose from forty-five percent to sixty-five percent. In addition, these mortality figures represent significant underestimates. The investigation excluded early season heat spikes and focused exclusively on urban areas representing forty percent of the population. Southern metropolitan centers such as Rome and Naples recorded the highest cumulative mortality. Similarly, regional hospitals experienced double-digit spikes in emergency admissions during prolonged heatwaves. Therefore, medical professionals cannot regard intense heatwaves as harmless seasonal weather patterns. Instead, healthcare providers must treat sustained ambient hyperthermia as a severe public health hazard that triggers widespread organ decompensation. Additionally, persistent heat stress progressively exhausts physiological reserve, compounding excess mortality across consecutive hot days.
When environmental temperatures exceed normal skin surface limits, the body dissipates heat primarily through cutaneous vasodilation and diaphoresis. Consequently, the circulatory system shifts significant blood volume toward superficial dermal vessels. To maintain vital organ perfusion despite this peripheral pooling, cardiac output must double or triple. Therefore, myocardial oxygen consumption rises sharply precisely when coronary arterial perfusion may decrease. For individuals with underlying coronary artery disease or heart failure, this intense hemodynamic stress precipitates acute myocardial infarction or fatal arrhythmias. Furthermore, heavy fluid loss through sweating causes severe hypovolemia, hemoconcentration, and increased blood viscosity. These circulatory changes dramatically elevate the risk of arterial thrombosis and acute ischemic stroke. In addition, persistent renal hypoperfusion combined with heat-induced rhabdomyolysis frequently causes acute tubular necrosis. Thus, patients rarely die from simple elevated temperature alone. Instead, extreme thermal strain triggers decompensation of preexisting cardiovascular, pulmonary, and renal diseases. Clinicians must actively identify these systemic cardiovascular compromises during hot weather to deliver prompt hemodynamic support. Additionally, widespread endothelial activation and the systemic release of inflammatory cytokines accelerate microvascular damage, precipitating multi-organ dysfunction syndrome.
Official registries consistently underreport heat-related fatalities because death certificates rarely cite environmental hyperthermia as the primary cause of death. Instead, physicians usually record proximate cardiovascular or cerebrovascular endpoints like myocardial infarction or acute heart failure. Consequently, the true mortality burden remains concealed within routine diagnostic tallies. Furthermore, diagnosing heatstroke in emergency settings presents significant clinical hurdles. Classical heatstroke often mimics acute sepsis, central nervous system infections, or anticholinergic toxidromes. Therefore, clinicians must maintain high clinical suspicion whenever patients present with altered mental status during heatwaves. Immediate diagnostic confirmation requires an accurate core body temperature measurement. Notably, oral, axillary, and tympanic thermometry show significant inaccuracies during profound hyperthermia. Clinical teams must rely on continuous rectal probes or esophageal sensors. In addition, practitioners should promptly order serum electrolytes, renal function tests, creatine kinase, and coagulation profiles. Early laboratory evaluation helps identify impending rhabdomyolysis and disseminated intravascular coagulation. Clinicians can then distinguish environmental heat toxicity from other critical conditions rapidly. Moreover, recognizing subtle hyperthermic presentations prevents diagnostic delays that often lead to irreversible neurological injury or death.
Clinical data indicates that adults over eighty-five years of age represent more than half of heat fatalities. However, extreme heat also claims hundreds of lives among young, active individuals. Aging intrinsically degrades human thermoregulation through diminished sweat gland output, reduced vascular elasticity, and impaired central thirst perception. Furthermore, elderly individuals frequently live alone in urban apartments that lack air conditioning. Consequently, sustained indoor heat traps vulnerable seniors in dangerous thermal environments without adequate hydration. Similarly, patients suffering from psychiatric disorders, cognitive impairment, or mobility restrictions face heightened mortality risks. In contrast, younger individuals primarily succumb to exertional heatstroke during strenuous outdoor employment or athletic training. In these scenarios, intense muscular exertion generates metabolic heat much faster than the body can dissipate it. Additionally, chronic medical comorbidities like diabetes mellitus and chronic kidney disease impair microvascular reactivity. Therefore, clinicians must risk-stratify patients across different age groups based on both physiological vulnerability and occupational heat exposure. Targeted interventions can then prevent fatal outcomes across diverse patient populations. Importantly, understanding these varying risk determinants enables acute care physicians to intervene before irreversible multi-organ failure ensues.
Emergency management of severe hyperthermia demands immediate, aggressive physiological cooling. Clinicians must initiate active cooling within minutes because sustained core temperatures above 40.5 degrees Celsius cause rapid cellular death. Whole-body cold water immersion represents the optimal cooling modality for exertional heatstroke, reducing core temperature rapidly. However, cold water immersion may hinder airway management and continuous cardiac monitoring in frail, elderly patients. Consequently, in these non-exertional presentations, clinical teams should utilize evaporative and convective cooling techniques. For instance, practitioners should spray lukewarm water over exposed skin while circulating air with high-speed fans. Additionally, clinicians should place ice packs over superficial vascular beds in the axillae, groin, and neck. Medical teams must simultaneously administer chilled intravenous isotonic crystalloids to restore intravascular volume carefully. Crucially, clinicians must avoid antipyretic drugs like acetaminophen or nonsteroidal anti-inflammatory agents. These medications do not alter environmental hyperthermia and can aggravate acute hepatic and renal damage. Teams must discontinue active cooling once core temperature drops to 38.5 degrees Celsius to prevent rebound hypothermia. Furthermore, intensive care specialists must continuously monitor patients for secondary complications like non-cardiogenic pulmonary edema and severe encephalopathy.
Preventing heat-related deaths requires proactive outpatient management before heatwaves peak. Physicians should conduct thorough medication reconciliations during early summer consultations. Many commonly prescribed medications disrupt thermoregulation or impair fluid homeostasis. For example, diuretics exacerbate hypovolemia, while beta-blockers limit compensatory tachycardia and decrease peripheral heat dissipation. Similarly, angiotensin receptor blockers and ACE inhibitors compromise renal autoregulation during severe dehydration. Anticholinergic medications, tricyclic antidepressants, and typical antipsychotics directly inhibit diaphoresis. Therefore, clinicians should educate patients regarding timely dosage adjustments, appropriate fluid intake, and indoor cooling techniques. Furthermore, health systems must partner with local municipalities to establish early heat-warning alerts and community cooling shelters. Establishing volunteer check-in networks for isolated seniors substantially reduces solitary fatalities. Hospital administrators must also ensure backup power for clinical cooling infrastructure. In addition, addressing underlying environmental factors through rapid decarbonization remains crucial for long-term health preservation. Consequently, combining proactive clinical management with robust public health infrastructure offers the best defense against escalating heat mortality. Additionally, healthcare facilities must train front-line triage staff to recognize early heat exhaustion before decompensation requires intensive care admission.
Q1: How do extreme temperatures induce fatal cardiovascular collapse?
Extreme environmental heat forces profound cutaneous vasodilation to dissipate thermal energy. Consequently, the heart must double or triple its cardiac output to preserve mean arterial pressure. This dramatic increase in myocardial work sharply elevates oxygen demand, which can trigger acute coronary ischemia, congestive heart failure decompensation, or fatal ventricular arrhythmias. Furthermore, severe fluid loss causes hemoconcentration and vascular thrombosis, substantially increasing the risk of sudden cardiac arrest in patients with preexisting cardiac disease.
Q2: Which chronic prescription drugs significantly heighten heat vulnerability?
Several standard cardiovascular and psychiatric medications significantly heighten susceptibility to heat illness. Specifically, diuretics exacerbate intravascular hypovolemia and precipitate acute electrolyte disturbances during heavy sweating. In addition, beta-blockers limit compensatory heart rate increases and impair peripheral blood flow distribution. Anticholinergic drugs, antihistamines, tricyclic antidepressants, and typical antipsychotics directly inhibit sweat gland secretion, blocking evaporative cooling. Consequently, clinicians must proactively adjust dosages, review hydration status, and closely monitor patients taking these agents during heatwaves.
Q3: Why are standard antipyretics contraindicated in classical heatstroke?
Standard antipyretics such as acetaminophen, nonsteroidal anti-inflammatory drugs, and aspirin remain strictly contraindicated in heatstroke management. These medications reduce body temperature by inhibiting pyrogen-driven prostaglandin synthesis within the hypothalamus during an infectious fever. However, heatstroke results from failure of peripheral heat dissipation mechanisms rather than altered hypothalamic temperature set-points. Therefore, antipyretics provide zero therapeutic cooling efficacy. Moreover, their administration substantially aggravates hepatic injury, coagulopathy, and acute renal failure in critically ill hyperthermic patients.
Disclaimer: This content is for informational and educational purposes only. It does not constitute medical advice or replace professional judgment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Recent epidemiological data reveals a dramatic surge in summer heat mortality driven by human-induced climate warming. This analysis explores the pathophysiological impacts on cardiac and renal systems, diagnostic dilemmas in death certification, and essential emergency cooling protocols for acute clinical care.
Today

Odisha has established India's first state-level clinical protocol specifically tailored for pregnant women with sickle cell disease. Developed with NHM and UNICEF, the framework provides structured antenatal screening, crisis mitigation, standardized referral pathways, and specialized interdisciplinary care.
Today

India is advancing preventive healthcare by integrating genomics, artificial intelligence, and quantum technologies. With the SANGAM programme sequencing one million Indian genomes, clinicians can unlock personalized therapies, detect cardiometabolic risks early, and curb the burden of diabetes and heart disease.
Today

A randomized controlled trial demonstrates that an eight-week dual-task training intervention significantly improves static and dynamic postural control over standard balance exercises in individuals with chronic ankle instability, addressing critical neurocognitive deficits during athletic and daily activities.
Today

A retrospective cohort study of 7,716 ICU patients from the MIMIC-IV database demonstrates that Gradient Boosting Decision Trees significantly outperform traditional SOFA scores in predicting in-hospital mortality among patients with sepsis and diabetes, with SHAP analysis providing clinical interpretability.
Today
