

Loading, please wait...
Loading, please wait...

Optimizing antimicrobial therapy in critically ill patients presents severe clinical hurdles. Clinicians widely utilize vancomycin therapeutic drug monitoring to balance bactericidal efficacy against acute nephrotoxicity. However, standard population pharmacokinetic models often fail in emergency departments and intensive care units. In these high-acuity environments, rapid hemodynamic shifts frequently distort drug disposition. Consequently, initial dosing algorithms may miscalculate target serum concentrations. Recent clinical evidence demonstrates that free software tools can overestimate predicted serum levels in specific emergency cohorts. Therefore, critical care physicians must identify susceptible patient subsets and apply validated scaling factors to safeguard therapeutic success.
Critically ill patients exhibit dynamic physiological alterations that disrupt conventional antimicrobial pharmacokinetics. Sepsis, extensive trauma, and systemic inflammation trigger endothelial dysfunction and capillary leak syndrome. As a result, hydrophilic glycopeptides like vancomycin experience a massive expansion in extracellular volume of distribution. Furthermore, aggressive fluid resuscitation dilutes circulating antibiotic concentrations during early resuscitation phases. In contrast, altered cardiac output and hyperdynamic circulation frequently induce augmented renal clearance. When kidneys clear drugs at accelerated rates, serum concentrations decline rapidly below therapeutic thresholds. Conversely, acute kidney injury can abruptly impair clearance mechanisms, causing severe drug accumulation. Because standard population models assume stable physiology, they often fail to capture these volatile kinetic extremes. Therefore, relying exclusively on generic nomograms risks both treatment failure and preventable nephrotoxicity. Clinical teams must understand that routine pharmacokinetic equations cannot universally represent emergency department patients. Consequently, clinicians require refined analytical tools that accurately adjust for acute physiological volatility. Moreover, baseline hypoalbuminemia further complicates dosing by elevating the unbound, biologically active fraction of the drug. Hence, precise initial dose calculation remains paramount for patient survival.
Researchers at the University of Miyazaki Hospital evaluated initial dosing accuracy using the Practical Antimicrobial TDM web application. Specifically, the investigative team examined serum concentration data from diverse emergency and intensive care admissions. The investigators classified patient groups by calculating the ratio between observed concentrations and predicted population concentrations. Interestingly, the analysis revealed a consistent overestimation of predicted serum levels across several high-risk patient subgroups. In these vulnerable individuals, the observed serum levels remained considerably lower than population model forecasts. Several clinical factors contributed to this systematic discrepancy. For example, severe fluid overload and third-spacing markedly elevated total distribution volumes beyond standard adult estimates. In addition, patients experiencing hypermetabolic stress displayed enhanced glomerular filtration that standard serum creatinine measurements failed to detect. Consequently, the software algorithm predicted adequate drug accumulation, whereas the patients actually suffered persistent subtherapeutic exposure. This overestimation creates significant hazards in early sepsis management because inadequate antimicrobial exposure increases microbiological failure rates. Therefore, identifying the root causes of model divergence is essential for clinicians who manage critical sepsis.
To overcome persistent concentration overestimation, clinical pharmacologists introduced specific population scaling factors. These mathematical corrections directly adjust the predicted mean concentration values generated by standard algorithms. By applying targeted scaling factors, clinicians can effectively counterbalance expanded distribution volumes and hyperdynamic renal clearance. Furthermore, this computational adjustment prevents clinicians from administering inappropriately low initial doses to septic patients. When practitioners utilize calibrated scaling factors, the accuracy of initial dose selection improves significantly. Consequently, patients attain target area-under-the-curve thresholds much earlier during empirical therapy. Importantly, achieving early target attainment within the initial twenty-four hours substantially curtails 30-day mortality in severe infections. Scaling factors also enable bedside pharmacists to individualize loading and maintenance regimens before initial therapeutic trough levels return from laboratory analyzers. In addition, this calibrated approach maintains therapeutic vigilance without requiring complex, unavailable bioanalytical hardware. Thus, incorporating scaling adjustments into free web-based platforms offers a highly practical solution for busy critical care units. As a result, clinical teams can deliver model-informed precision dosing safely and effectively.
The findings from emergency department pharmacokinetic simulations offer vital lessons for modern sepsis protocols. Early and appropriate antibiotic therapy remains the cornerstone of surviving sepsis guidelines worldwide. However, empirical underdosing during the first 48 hours frequently undermines patient recovery and fosters antimicrobial resistance. Furthermore, methicillin-resistant Staphylococcus aureus infections demand sustained target exposures, specifically an area-under-the-curve to minimum inhibitory concentration ratio between 400 and 600. When prediction tools overestimate serum concentrations, clinicians inadvertently select lower maintenance doses. Consequently, bacterial clearance stalls, and the risk of persistent bacteremia multiplies. Conversely, administering excessive compensatory doses without proper guidance could precipitate acute tubular necrosis. Therefore, precision dosing tools must integrate realistic physiological scaling factors to maintain safety margins. Moreover, bedside intensivist-pharmacist multidisciplinary teams can utilize these validated adjustments to design superior initial infusions. As a result, critical care units can improve patient survival while simultaneously reducing length of stay. Clinicians must actively bridge the gap between static pharmacokinetic formulas and fluctuating acute illness.
These pharmacokinetic insights carry tremendous relevance for clinical practice across intensive care units in India. Severe sepsis, polymicrobial trauma, and hospital-acquired infections remain highly prevalent throughout Indian tertiary hospitals. Moreover, Indian clinicians encounter high rates of methicillin-resistant Staphylococcus aureus in blood and pulmonary isolates. Unfortunately, many regional hospitals lack access to high-end commercial Bayesian software licenses due to economic constraints. Therefore, free web-based platforms like Practical Antimicrobial TDM provide an invaluable, accessible resource for Indian intensivists. However, healthcare professionals must exercise caution regarding population overestimation in undernourished, edematous, or hyperdynamic patients. Sepsis in Indian intensive care units frequently involves profound capillary leaks and acute third-spacing from severe tropical infections. In addition, routine reliance on serum creatinine often masks augmented renal clearance in younger trauma patients. Consequently, incorporating scaling factors into initial dosing nomograms prevents catastrophic underdosing in Indian critical care environments. Furthermore, establishing dedicated clinical pharmacy services in regional intensive care units will accelerate the adoption of precision dosing. Ultimately, standardizing these pharmacokinetic corrections will enhance patient safety and optimize antimicrobial stewardship nationwide.
Critical illness causes capillary leak, profound third-spacing, and aggressive fluid resuscitation, which collectively expand the extracellular volume of distribution. Additionally, hyperdynamic circulation frequently accelerates renal clearance beyond normal parameters. Because standard population pharmacokinetic models assume stable physiology and typical distribution volumes, they project higher drug levels than actually exist. Consequently, the software algorithm calculates an overestimated predicted concentration, leading clinicians to observe unexpectedly low drug levels in their emergency patients.
Scaling factors apply mathematically derived correction coefficients directly to the initial predicted population concentrations. By adjusting for expected physiological extremes, these scaling factors compensate for expanded distribution volumes and augmented clearance before empirical therapy begins. Consequently, clinicians avoid selecting subtherapeutic loading or maintenance doses for high-risk patients. This targeted adjustment accelerates the achievement of therapeutic area-under-the-curve targets during the critical first twenty-four hours while substantially minimizing the risk of drug-induced nephrotoxicity.
Indian intensive care units can implement precision dosing by adopting validated, accessible web applications alongside dedicated clinical pharmacy consultations. Clinicians should routinely evaluate patients for augmented renal clearance, fluid overload, and hypoalbuminemia before finalizing empirical regimens. Furthermore, medical teams must apply scaling corrections to initial doses, obtain timely blood samples, and calculate individual pharmacokinetic parameters. This structured multidisciplinary workflow optimizes therapeutic outcomes, shortens hospital stays, and strengthens antimicrobial stewardship across resource-constrained clinical settings.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A Japanese emergency department study reveals that population pharmacokinetic software frequently overestimates initial serum vancomycin concentrations in critically ill patients. Applying targeted scaling factors corrects these discrepancies, safeguarding early target attainment and patient outcomes.
4 weeks back

A preclinical breakthrough reveals how nodosin drives hepatic stellate cell ferroptosis via the SIRT1-PERK-HSPA5-MARCHF1 axis, degrading GPX4 and reversing experimental liver fibrosis. This discovery uncovers fresh therapeutic avenues for managing chronic hepatic fibrogenesis.
Today

A large UK cohort study of 1.4 million women shows that pregnancy complications, including gestational diabetes, hypertension, and preterm birth, substantially raise long-term risks for hypertension, chronic kidney disease, type 2 diabetes, and cardiovascular events, highlighting early postpartum intervention needs.
Yesterday

A cross-sectional study reveals that hypertension knowledge, illness perceptions, depression, and substance use significantly predict self-care behaviors. Addressing mental health and cognitive beliefs in primary care is crucial for optimal blood pressure control and cardiovascular disease prevention.
Today
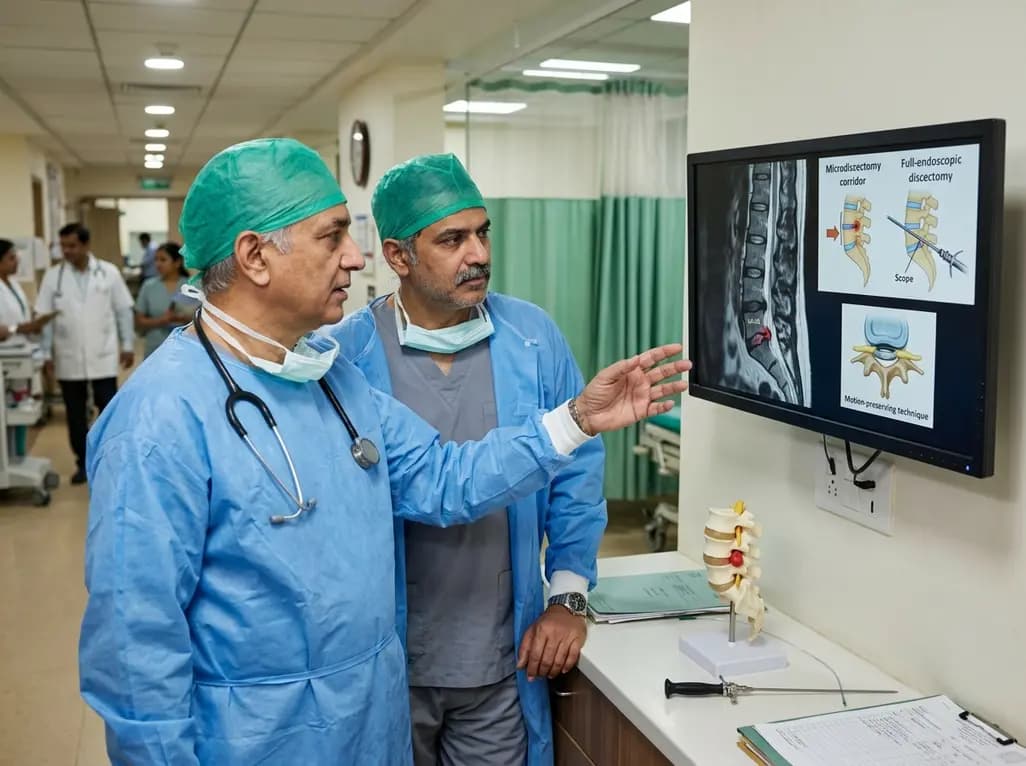
This clinical overview examines recent advancements in lumbar disc herniation surgery, comparing microscopic and full-endoscopic discectomy while highlighting biportal techniques and emerging motion-preserving innovations for spine specialists.
Today
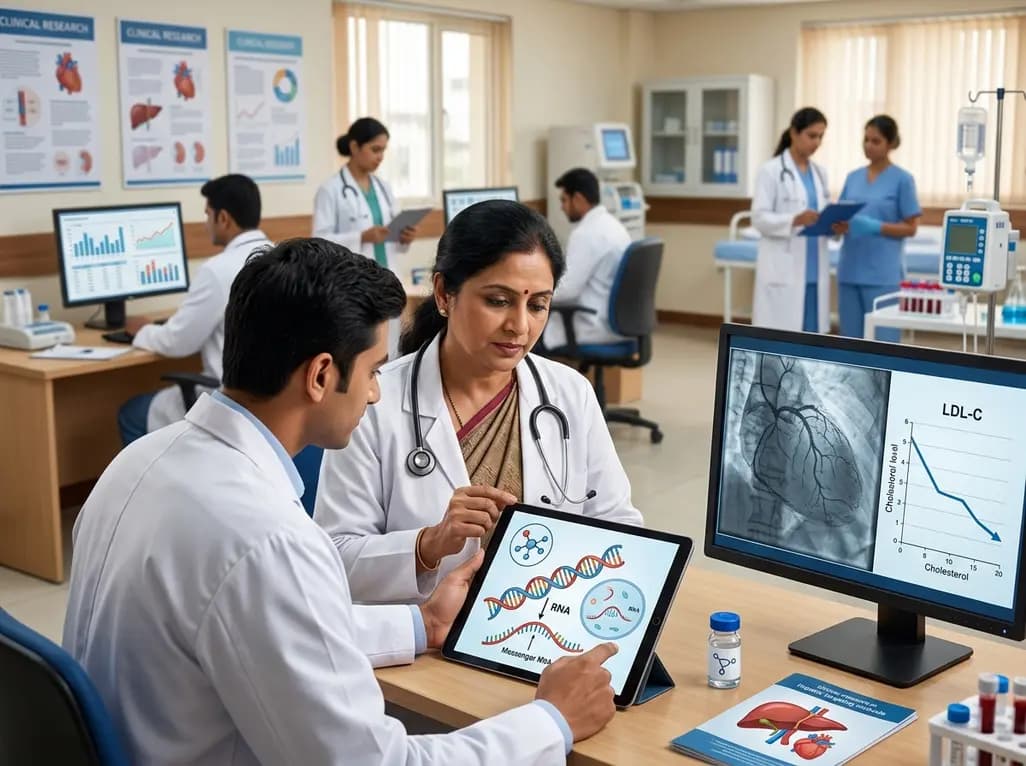
Small interfering RNA (siRNA) therapeutics harness RNA interference to degrade disease-causing messenger RNA. By delivering hepatocyte-targeted, durable gene silencing, agents targeting PCSK9, LPA, and angiotensinogen offer potent cardiovascular risk reduction with infrequent, biannual dosing schedules.
Today
