

Loading, please wait...
Loading, please wait...
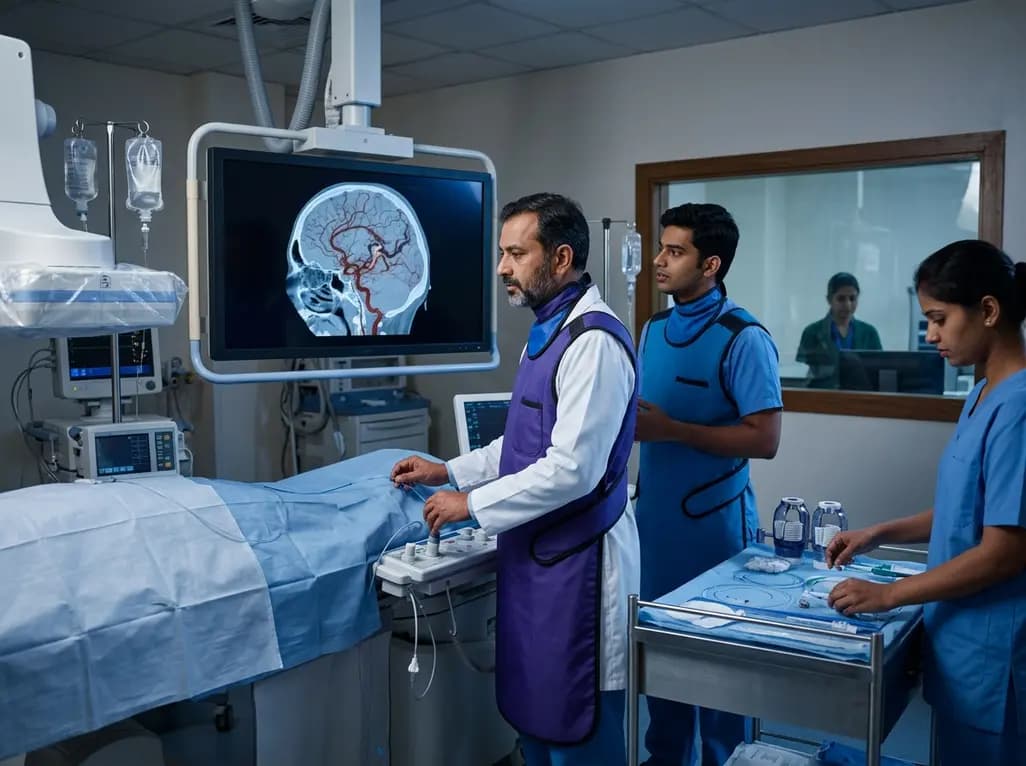
Cribriform plate DAVF represents a rare and challenging neurovascular pathology within the anterior cranial fossa. These vascular malformations develop along the ethmoidal groove, where abnormal arteriovenous shunts connect dural branches with cortical veins. Most notably, cribriform plate DAVF lesions lack immediate drainage into major dural sinuses. Instead, arterialized high-pressure flow empties directly into fragile frontal pial or cortical veins. Consequently, patients face an alarming risk of intracranial hemorrhage, often presenting with acute subarachnoid or intraparenchymal bleeding.
Historically, clinicians recognized this disorder primarily in older male patients. Affected individuals frequently report persistent headaches, visual changes, or pulsatile tinnitus before severe rupture occurs. In addition, head trauma or chronic local venous hypertension often contributes to fistula formation. Magnetic resonance angiography and digital subtraction angiography remain the diagnostic gold standards. These modalities reveal fine feeder networks arising from the ophthalmic artery via ethmoidal branches. Because untreated lesions exhibit aggressive natural histories, prompt neurointerventional obliteration is critical to prevent fatal rebleeding.
Traditionally, interventional teams selected transarterial embolization as the primary endovascular therapy for these anterior cranial malformations. Operators introduce microcatheters through the ophthalmic artery to deliver liquid embolic agents directly into the nidus. However, this transarterial route carries substantial technical limitations and safety hazards. The anterior and posterior ethmoidal arteries possess tiny calibers and tortuous trajectories. Therefore, navigating microcatheters into an ideal wedge position near the fistula site remains remarkably arduous.
Furthermore, proximal arterial occlusion often leaves collateral pathways patent, producing disappointing incomplete obliteration rates. Recent retrospective data reveal that transarterial embolization achieves immediate total occlusion in only 53.8% of treated cases. Moreover, navigating through the ophthalmic artery risks catastrophic complications, including central retinal artery occlusion and subsequent permanent blindness. Procedural challenges also precipitate mechanical mishaps. In clinical series, transarterial procedures suffered significant complications such as microcatheter fractures and distal thromboembolisms. Consequently, interventionalists actively seek more reliable and safer alternative pathways.
To overcome arterial access limitations, transvenous embolization has emerged as a potent therapeutic alternative for selected patients. Interventional radiologists and neurosurgeons access the venous system through femoral or jugular access. Subsequently, operators steer microcatheters through the superior sagittal sinus into the draining frontal cortical veins. Recent comparative studies demonstrate that transvenous embolization achieves a remarkable 100% immediate complete occlusion rate, significantly outperforming transarterial approaches.
Importantly, this transvenous route targets the common venous collector where multiple ethmoidal feeders converge. By obliterating this singular outflow foot with coils or liquid embolic materials, operators achieve durable anatomical cure. In addition, the transvenous approach spares the ophthalmic arterial system, effectively eliminating the risk of visual impairment. Clinical analyses also demonstrate exceptional procedural safety, with patients experiencing no symptomatic complications or procedural neurological deficits. Thus, evidence strongly suggests that transvenous treatment provides superior efficacy and favorable safety profiles in anatomically suitable candidates.
Although transvenous embolization delivers superior occlusion rates, navigating fragile intracranial veins demands extreme technical precision. Cortical veins feature thin muscular layers and follow acutely angled, tortuous courses into dural sinuses. Consequently, pushing straight microwires directly into these delicate vessels creates dangerous shearing forces and risks venous perforation. To mitigate this hazard, interventionalists rely on the wire-loop technique during catheter advancement.
Specifically, operators form a rounded, blunt loop with the microwire tip inside the superior sagittal sinus before engaging cortical tributaries. This curved geometry evenly distributes mechanical force along the vascular wall rather than focusing stress at a single point. As a result, the microcatheter tracks smoothly over the atraumatic loop without tearing fragile endothelium. Furthermore, this technique allows operators to negotiate sharp retrograde curves that would otherwise resist conventional wire guidance. Mastering this maneuver ensures safe distal positioning right at the fistulous venous sac, safeguarding procedural success.
The paradigm shift toward transvenous intervention significantly refines the modern management algorithm for anterior skull base fistulas. Historically, when transarterial embolization failed or appeared treacherous, clinicians immediately recommended open microsurgical disconnection through a frontal craniotomy. While microsurgery remains an effective definitive cure, it requires invasive brain retraction and carries inherent general surgical morbidity. Therefore, validating a minimally invasive transvenous strategy expands the endovascular armamentarium considerably.
However, multidisciplinary teams must carefully evaluate individual venous angioarchitecture before deciding on an intervention strategy. Successful transvenous access requires a continuous, navigable venous channel from the superior sagittal sinus to the fistula site without thrombosis. In addition, operators must ensure that occluding the target vein does not compromise normal cerebral venous drainage. When diagnostic imaging confirms isolated, non-functional venous drainage of the fistula, transvenous embolization should serve as a preferred first-line intervention. Ultimately, careful patient selection and specialized endovascular expertise ensure optimal neurological outcomes.
Cribriform plate DAVFs lack direct drainage into major dural venous sinuses. Instead, arterialized blood shunts directly into fragile frontal cortical or pial veins. Consequently, severe venous hypertension develops rapidly within these thin-walled vessels. This pathological hemodynamic stress significantly elevates the risk of life-threatening intracranial hemorrhage or subdural hematoma.
Transvenous embolization delivers liquid embolic agents directly into the draining venous pouch where multiple arterial feeders converge. Therefore, targeting this common venous outflow occludes the entire fistulous junction in one procedure. In contrast, transarterial access often fails because tiny, tortuous ethmoidal arteries restrict complete microcatheter navigation to the shunt.
Navigating retrograde through tortuous frontal cortical veins presents substantial mechanical resistance and perforation risks. However, the wire-loop technique creates a blunt, curved loop with the microwire tip. This design distributes forward pressure along vessel walls rather than puncturing them. Consequently, operators can safely advance microcatheters into acute venous angles without rupture.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References
Xu L et al. Transvenous approach: a promising strategy for endovascular treatment of cribriform plate dural arteriovenous fistula. J Neurosurg. 2025 Aug 01. doi: 10.3171/2024.12.JNS241501. PMID: 40184685.
Shilovs A, Kupca K, Kidikas H, Kupcs K. Transvenous embolization of cribriform plate arteriovenous fistulas: a case series. J NeuroIntervent Surg. 2025;17(Suppl 2):A165.
Gross BA, Du R. Adult intracranial dural arteriovenous fistulae: natural history and management decisions. MDPI J Clin Med. 2024;13(4):1042.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A recent study evaluates endovascular treatment for cribriform plate dural arteriovenous fistulas (DAVFs), showing that transvenous embolization achieves superior complete occlusion rates and fewer complications compared to transarterial approaches.
last month

Momelotinib offers unique clinical benefits for myelofibrosis patients with moderate-to-severe anemia via dual JAK and ACVR1 inhibition. While registration trials show positive hematologic outcomes, emerging real-world data underscore the need for vigilant surveillance of renal function and peripheral neuropathy.
Today

Delhi is undergoing a major healthcare overhaul with enhanced Ayushman Bharat insurance up to ₹10 lakh, increased MBBS and PG medical training seats, expanded primary network mandirs, new tertiary neuro-ICUs, and public-private reproductive technology initiatives to build a resilient, preventative healthcare model.
Today
A 78-year-old patient with high-grade aneurysmal subarachnoid hemorrhage complicated by refractory Takotsubo cardiogenic shock achieved full recovery following microaxial flow pump (Impella 5.5) rescue, demonstrating the safety and feasibility of advanced mechanical circulatory support during dual antiplatelet therapy.
Today

Non-union fractures occur in 2-5% of cases, causing significant disability and cost. Conservative modalities such as LIPUS, PEMF, and focused ESWT offer non-surgical healing options for defects up to 5-10 mm when adequate mechanical stability exists without infection.
Yesterday

The randomized HOBIT-AF trial reveals that while structured weight loss after catheter ablation significantly improves cardiometabolic health in obese patients with paroxysmal atrial fibrillation, it does not reduce arrhythmia recurrence compared to standard care.
Today
