

Loading, please wait...
Loading, please wait...
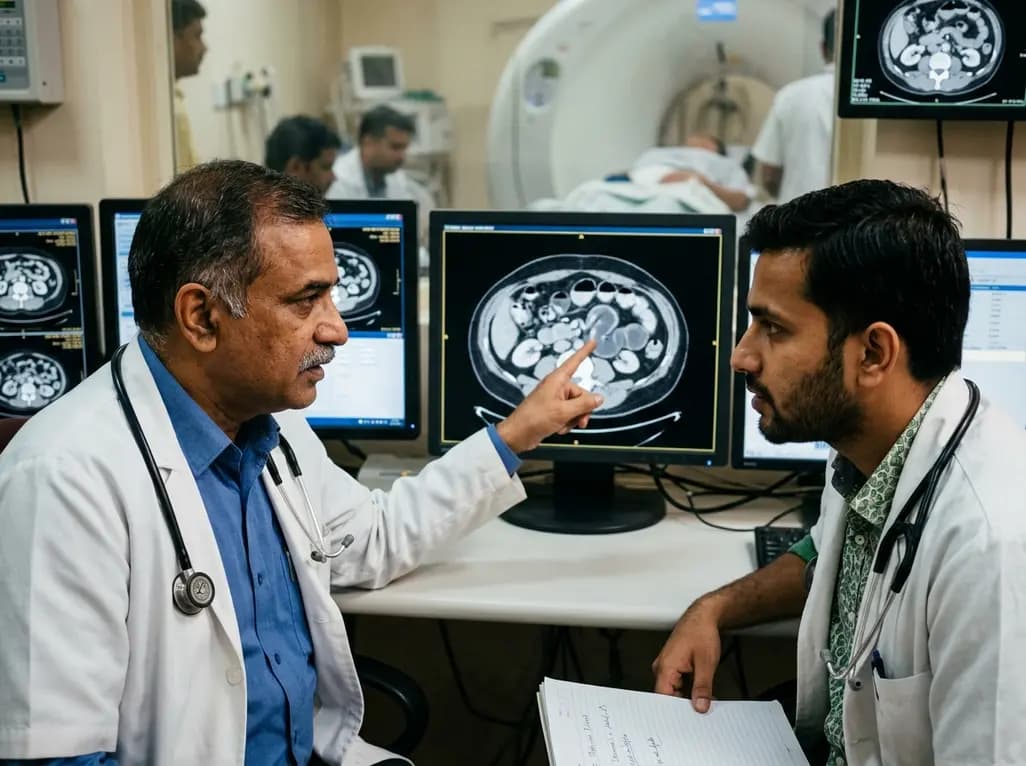
Small bowel obstruction remains a frequent surgical emergency encountered in emergency departments and acute care wards. While postoperative adhesions cause most mechanical obstructions, clinicians occasionally confront rare internal abdominal defects. Among these atypical presentations, spontaneous transomental internal hernia represents an exceedingly uncommon and life-threatening pathology, particularly in patients who have never undergone laparotomy. Because the clinical presentation mimics routine mechanical ileus, clinicians face significant diagnostic dilemmas that can delay lifesaving operative care.
Clinicians commonly presume postoperative adhesions when evaluating an elderly patient with acute mechanical obstruction. However, when an individual presents with a virgin abdomen, the diagnostic spectrum changes dramatically. Internal hernias account for fewer than five percent of all mechanical small bowel obstructions. Moreover, a transomental internal hernia constitutes merely one to four percent of these rare events. Consequently, practitioners seldom maintain a high index of suspicion during initial triage.
In the featured clinical case, a 72-year-old hypertensive gentleman presented with acute abdominal pain, persistent vomiting, and nausea. He possessed no history of prior abdominal operations, violent trauma, or chronic intra-abdominal inflammatory conditions. Laboratory investigations demonstrated leukocytosis, while preliminary plain abdominal radiographs showed distinct air-fluid levels consistent with mechanical ileus. Nevertheless, these conventional baseline investigations failed to pinpoint the exact underlying etiology.
Because the patient lacked surgical scars, the admitting medical team initially considered non-operative decompression. Unfortunately, conservative management frequently fails when anatomical apertures entrap intestinal loops. Delayed operative decompression increases the risk of irreversible bowel gangrene, vascular thrombosis, and septic shock. Therefore, clinicians must actively suspect spontaneous omental defects in non-operated patients who exhibit acute mechanical ileus.
Understanding how a spontaneous defect develops within the greater omentum requires close examination of tissue architecture. In younger populations, traumatic shear injuries or congenital mesenteric fenestrations typically create these rare peritoneal apertures. Conversely, in geriatric individuals with unoperated abdomens, age-related senile atrophy plays a fundamental physiological role.
As individuals age, progressive vascular insufficiency and adipose tissue thinning create localized avascular zones within the greater omentum. Consequently, physiological stretching or sudden spikes in intra-abdominal pressure can rupture these fragile, parchment-thin windows. Straining during defecation, severe paroxysmal coughing, or heavy lifting frequently triggers the final structural rupture. Once a small peritoneal defect forms, wandering peristaltic loops can easily slip into the opening.
Furthermore, the continuous propulsive forces of intestinal peristalsis gradually propel more bowel into the omental defect. As venous outflow becomes impeded, the trapped bowel loop swells rapidly, creating a rigid closed-loop obstruction. Because the greater omentum lacks an expansive peritoneal sac, the entrapped bowel faces rapid ischemic strangulation. Thus, what begins as a silent microscopic defect can rapidly culminate in an acute surgical crisis within hours.
Early identification of transomental defects requires urgent, cross-sectional imaging rather than prolonged plain radiographic observation. While conventional abdominal radiography easily detects multiple air-fluid levels, it provides negligible diagnostic information regarding the anatomical cause. In contrast, contrast-enhanced computed tomography offers decisive anatomic localization, guiding the surgeon directly to the operative site.
On computed tomography, radiologists search for clustered, dilated small bowel loops situated in an abnormal anterior compartment. Specifically, these fluid-filled loops often lie between the anterior abdominal wall and the transverse colon without an enclosing hernia sac. Additionally, multidetector computed tomography frequently visualizes a sharp transition zone alongside localized mesenteric fat stranding and vascular engorgement. Radiologists also look for the diagnostic whirl sign, which reflects twisted mesenteric vessels converging toward the narrow omental window.
In this clinical case, the contrast scan revealed a completely collapsed colon and a distinct transition zone between distended proximal loops and decompressed distal ileum. The presence of mesenteric haziness signaled localized vascular compromise. Therefore, prompt computed tomography allows clinicians to distinguish simple dynamic ileus from high-risk strangulating internal herniation before tissue necrosis occurs.
Standard protocols for mechanical adhesive obstruction frequently utilize nasogastric tube decompression, fluid resuscitation, and watchful waiting. However, applying prolonged conservative protocols to internal hernias introduces hazardous clinical pitfalls. Closed-loop obstruction develops when the entering and exiting limbs of the herniated intestinal loop undergo simultaneous constriction within the omental defect.
Because the trapped bowel cannot decompress proximally, intraluminal pressure escalates swiftly. This escalating pressure rapidly compromises microvascular mucosal perfusion, leading to venous infarction and transmural necrosis. In the featured elderly patient, conservative management continued for 48 hours without symptomatic or clinical improvement. Although the bowel miraculously remained viable until surgery, such prolonged delays often result in catastrophic perforations.
Furthermore, elderly patients possess diminished physiological reserve, which impairs their capacity to tolerate systemic endotoxemia or extensive surgical resections. Persistent leukocytosis, unremitting abdominal pain, or localized peritonitis demand immediate cessation of conservative observation. Clinicians must recognize that internal hernias rarely resolve spontaneously. Consequently, surgical teams should establish a strict, limited observation window and proceed promptly to surgical exploration whenever clinical evolution stalls.
Prompt operative intervention remains the cornerstone of definitive therapy for acute transomental herniation. Surgeons may select either minimally invasive laparoscopy or traditional exploratory laparotomy based on abdominal distension and hemodynamic stability. During surgical exploration, the primary surgical objectives include releasing the constricted bowel, evaluating tissue viability, and preventing hernia recurrence.
In this patient, surgeons performed an exploratory laparotomy, which revealed a distinct three-centimeter circular defect in the greater omentum. A loop of viable small bowel was strangulated within this tight fibrous ring. The surgical team carefully reduced the herniated loop and assessed intestinal viability under direct visual inspection. Because prompt decompression restored healthy capillary refill and active peristalsis, the patient avoided an extensive enterectomy.
Finally, the operating team resected the defective omental tissue rather than simply closing the aperture with sutures. Resecting the surrounding omental segment effectively obliterates the potential space and eliminates the risk of future adhesive bands or recurrent herniation. Following this definitive repair, the patient experienced an uneventful postoperative recovery and returned home safely on postoperative day three.
In patients with a virgin abdomen, spontaneous transomental internal hernias typically originate from senile atrophy of the greater omentum. As elderly individuals age, chronic microvascular insufficiency and fat thinning generate localized, parchment-like avascular apertures. Subsequent sudden increases in intra-abdominal pressure from coughing, lifting, or straining can tear these fragile zones. Peristaltic bowel loops then migrate into the resulting defect, causing acute incarceration and closed-loop intestinal obstruction.
Contrast-enhanced computed tomography reveals clustered, dilated small bowel loops positioned abnormally in the anterior peritoneal cavity, often directly abutting the anterior abdominal wall without an enclosing hernia sac. Additionally, radiologists identify a closed-loop obstruction configuration with close, paired transition zones converging toward the omentum. Secondary vascular signs such as mesenteric vessel convergence, localized fat stranding, and the classic whirl sign strongly differentiate internal herniation from straightforward adhesive obstruction bands.
Internal hernias inherently produce closed-loop mechanical obstructions that rarely reduce spontaneously through conservative nasogastric decompression. Prolonged observation progressively increases intraluminal pressure within the trapped segment, which rapidly compromises mesenteric venous outflow and arterial blood supply. Consequently, delaying operative exploration beyond 24 hours significantly heightens the hazard of irreversible bowel ischemia, transmural gangrene, and bowel perforation. Prompt surgical intervention preserves viable bowel tissue and prevents morbid enterectomy resections.
Disclaimer: This content is for informational and educational purposes only and does not constitute medical advice. Always consult a certified healthcare professional for diagnosis and treatment. Refer to the latest local and national guidelines for clinical practice.
References
Goren Z et al. Spontaneous transomental internal hernia causing small bowel obstruction in an elderly patient with a virgin abdomen: a case report. J Surg Case Rep. 2026 Sep undefined. doi: 10.1093/jscr/rjag835. PMID: 42812180.
Şimşek O, Ergenç M. Small bowel obstruction due to spontaneous transomental hernia in an octogenarian patient: a case report. J Trends Med Invest. 2025;4(2):45-48.
Doishita S, Takeshita T, Uchima Y, et al. Internal Hernias in the Era of Multidetector CT: Correlation of Imaging and Surgical Findings. Radiographics. 2016;36(1):88-103.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Spontaneous transomental internal hernia is an exceptionally rare cause of small bowel obstruction in patients with a virgin abdomen. Learn how emergency physicians and surgeons can recognize key CT signs, avoid delayed operative intervention, and prevent bowel gangrene through timely exploration.
Today

Data from the 2026 Workforce Health Index reveals that 38.7% of urban employees and dependents exhibit abnormal glycemic control. Emerging at increasingly younger ages, this metabolic shift intersects with severe vitamin deficiencies, highlighting the urgent need for early workplace screenings and targeted clinical care.
Today

The Maharashtra Food and Drug Administration has enforced stringent compliance orders under food safety laws. The directive prohibits commercial promotions, infant formula samples, gifts, and clinician sponsorships while mandating explicit breastfeeding notices and rapid adverse event reporting across healthcare facilities.
Today

Haryana Chief Minister Nayab Singh Saini has rolled out landmark performance-linked financial incentives for public sector clinicians and allied staff. The comprehensive reform introduces free intravitreal diabetic retinopathy management, flexible empanelment for private specialists, and digital infrastructure upgrades.
Today

A cross-sectional study reveals a strong positive correlation between problematic internet use and kinesiophobia in adults aged 18-45 with non-specific low back pain, highlighting how digital overuse reinforces movement fear and complicates musculoskeletal recovery.
Today
A recent coronary CT angiography study demonstrates that diabetic patients exhibit accelerated plaque burden, impaired CT-FFR, and elevated perivascular fat attenuation index values, reflecting heightened vascular inflammation that worsens across adverse metabolic phenotypes.
Today
