

Loading, please wait...
Loading, please wait...
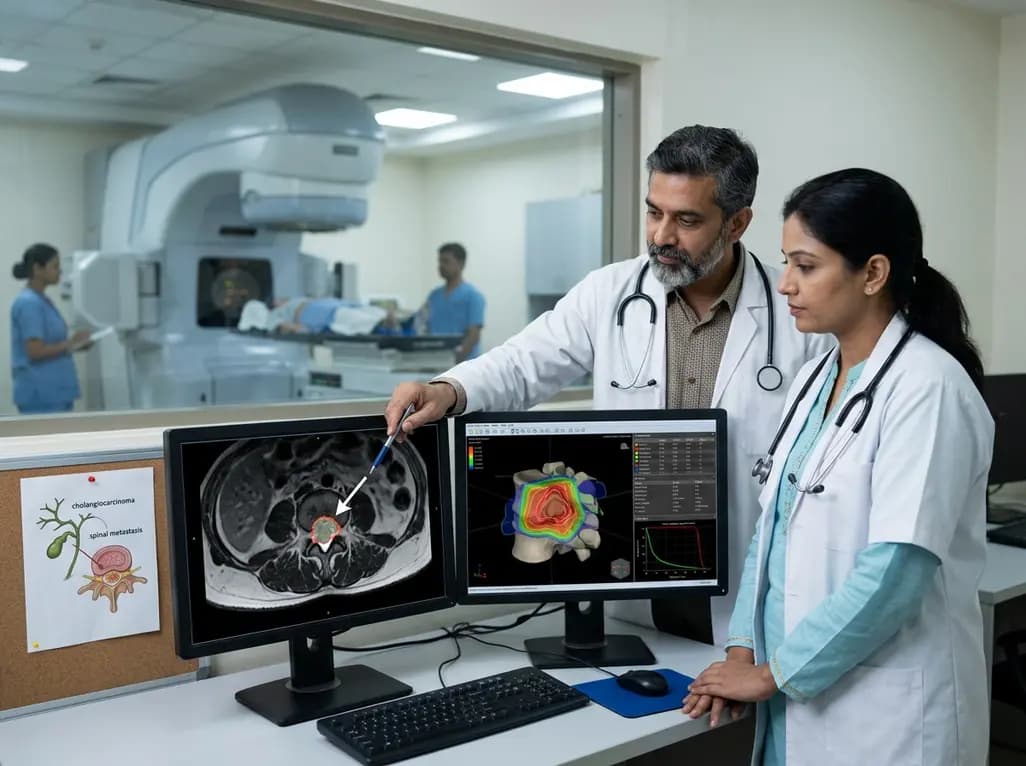
Cholangiocarcinoma represents an aggressive malignancy of the biliary tract that frequently presents at an advanced stage. When systemic dissemination occurs, osseous involvement poses severe clinical challenges, especially within the vertebral column. Clinicians increasingly encounter spinal cholangiocarcinoma metastases as patient survival extends with modern systemic therapies. Consequently, achieving rapid, durable local tumor control while preserving neurological function remains a primary objective. Stereotactic radiosurgery has gained prominence as a precise, non-invasive ablative technique for spinal oligometastases. However, comprehensive clinical evidence focusing specifically on secondary biliary tract lesions has historically remained sparse. A recent milestone study provides critical insights into the therapeutic efficacy, dosimetric parameters, and safety profile of high-dose stereotactic radiosurgery for these demanding cases. This article explores the latest clinical findings, examining how biologically effective dose thresholds and structural grading systems guide spine oncology care.
Biliary tract cancers exhibit biologically aggressive behavior, frequently resulting in rapid local invasion and distant organ metastases. While skeletal involvement was historically considered uncommon, enhanced imaging modalities identify spinal lesions with increasing frequency. Patients suffering from spinal cholangiocarcinoma metastases frequently experience severe, intractable axial pain, radicular symptoms, and debilitating neurological deficits caused by mechanical instability or epidural cord compression. Conventional external beam radiation therapy often provides only transient palliative relief for these patients, largely because biliary adenocarcinoma demonstrates relative radioresistance. Furthermore, standard palliative radiation schedules cannot safely deliver fully ablative doses without risking spinal cord toxicity. Stereotactic radiosurgery bridges this critical therapeutic gap by using advanced image-guidance and intensity modulation to deliver concentrated radiation directly to the vertebral lesion. Consequently, radiation oncologists can deliver tumoricidal doses while sparing critical neural structures. Clinicians must actively recognize the unique radiobiological behavior of biliary adenocarcinoma to optimize both palliative efficacy and long-term local tumor control in clinical practice.
Dose escalation remains central to overcoming the inherent radioresistance of gastrointestinal and hepatobiliary malignancies. In radiosurgery, the biologically effective dose (BED) quantifies the true biological impact of various fractionation regimens. Recent investigations highlight the role of BED thresholds in predicting local control for spinal cholangiocarcinoma lesions. Specifically, dosimetric analysis revealed that lesions treated with a BED exceeding 60 Gy achieved remarkable local tumor control with zero instances of local progression. In contrast, lesions receiving a BED of 60 Gy or less exhibited a twenty-five percent progression rate. Therefore, delivering an ablative BED above 60 Gy appears to represent a critical threshold for durable tumor ablation. Achieving these elevated dosimetric targets requires precise target delineation, meticulous motion management, and steep dose gradients. As systemic therapies improve patient life expectancy, durable local control becomes increasingly paramount. Consequently, radiation oncologists should prioritize reaching this biologically effective dose threshold whenever safe anatomical constraints permit.
Effective clinical management of spinal metastases requires comprehensive structural and functional evaluation prior to radiosurgery. The Bilsky grading system serves as an indispensable radiological tool, categorizing the degree of epidural spinal cord compression. Recent data demonstrate that lesions with Bilsky grade 1c or higher show significantly lower three-month clinical response stability compared to lower-grade lesions. Specifically, lower-grade lesions achieved an eighty-five percent stability rate, whereas high-grade epidural involvement dropped stability to twenty-five percent. Therefore, severe epidural extension substantially impairs durable radiosurgical response. In addition, baseline functional capacity, measured via the Karnofsky Performance Status, heavily influences treatment planning. Patients presenting with superior performance status frequently tolerate intensified radiosurgical regimens and higher biologically effective doses. Consequently, multidisciplinary teams must integrate both Bilsky grading and performance metrics during initial triage. For patients exhibiting high-grade epidural compression, separation surgery followed by postoperative radiosurgery often represents the most appropriate strategy.
Safety remains a paramount consideration when administering high-dose ablative radiation near the spinal cord and cauda equina. Fortunately, modern stereotactic radiosurgery demonstrates an exceptional safety profile in the management of secondary biliary tract tumors. Clinical analyses confirmed the absence of Common Terminology Criteria for Adverse Events grade 3 or higher toxicities following treatment. Importantly, no severe acute radiation myelopathy, vertebral collapse requiring emergent intervention, or life-threatening soft-tissue complications occurred. Simultaneously, stereotactic radiosurgery achieved an impressive one-year local tumor control rate of eighty-six percent. Furthermore, treated patients demonstrated a median overall survival of twelve months, reflecting meaningful clinical benefit in an advanced disease population. Because adverse events remained minimal, patients maintained their quality of life without treatment-induced interruptions to ongoing systemic chemotherapy. Thus, radiosurgery successfully combines powerful tumor ablation with robust tissue sparing, offering safe palliation for vulnerable cancer patients.
The management of complex spinal metastases requires close collaboration among spine surgeons, radiation oncologists, medical oncologists, and radiologists. These recent clinical insights establish clear practical guidelines for managing spinal cholangiocarcinoma metastases. First, clinicians should perform early magnetic resonance imaging to accurately determine Bilsky classification and detect subclinical cord compression. Second, multidisciplinary tumor boards should evaluate whether upfront surgical decompression is necessary before stereotactic radiosurgery for high-grade Bilsky lesions. Third, radiation treatment planning should deliberately target a biologically effective dose greater than 60 Gy to prevent local recurrence. In addition, preserving baseline performance status through proactive pain management and physical rehabilitation maximizes overall survival. As targeted systemic therapies and immunotherapies continue to evolve, achieving durable local spine stability prevents catastrophic neurological decline. Ultimately, incorporating targeted radiosurgery into multidisciplinary treatment pathways improves functional independence and survival outcomes for patients with metastatic cholangiocarcinoma.
Stereotactic radiosurgery delivers precise, high-dose radiation to vertebral metastases while sparing adjacent neural tissues. It provides durable local tumor control and rapid pain relief for radioresistant cholangiocarcinoma, preventing neurological deficits and preserving patient functional independence without requiring invasive open spinal surgery.
Dosimetric studies show that a biologically effective dose greater than 60 Gy significantly improves local tumor control. Lesions treated above this threshold demonstrated zero local progression, whereas lower doses had higher failure rates, highlighting the necessity of adequate dose escalation during radiosurgical treatment planning.
Surgical intervention, such as separation surgery, is strongly recommended for high-grade epidural cord compression corresponding to Bilsky grade 1c or higher. Decompression creates a safe distance between the tumor and spinal cord, allowing clinicians to deliver ablative radiosurgical doses without risking radiation-induced myelopathy.
Disclaimer: This content is for informational and educational purposes only and should not be considered medical advice. Clinical decisions must be tailored to individual patient needs and made by qualified healthcare professionals. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Stereotactic radiosurgery achieves an 86% 1-year local control rate for spinal cholangiocarcinoma metastases. Delivering a biologically effective dose over 60 Gy eliminates local progression, providing durable tumor ablation with a favorable safety profile.
last month

A review of incidental intestinal parasitic infections detected during colonoscopy, highlighting diagnostic morphology, the absence of peripheral eosinophilia, and tailored antihelminthic treatment.
Today

A nationwide South Korean study shows underreporting of smoking among women dropped from 57.4% to 36.4% between 2008 and 2021. However, over one-third of female smokers still conceal their habit, highlighting the critical role of cotinine verification in clinical risk assessment.
Today

PepsiCo and Monster Beverage have challenged the FSSAI ban on the energy drink label in Indian courts. While companies highlight supply disruptions, regulatory actions spotlight severe cardiovascular and metabolic risks associated with excessive caffeine, sugar, and taurine consumption, especially in adolescents.
Today
Persistent and recurrent musculoskeletal pain in youth athletes is often dismissed as simple growing pains. A developmentally informed biopsychosocial framework is essential to guide return-to-sport decisions, addressing biological vulnerabilities, psychological appraisals, and sociocultural expectations.
Today

A Bayesian multilevel meta-analysis reveals that aerobic training combined with moderate carbohydrate restriction modestly lowers HbA1c in type 2 diabetes. However, sparse data and very low certainty leave incremental benefits over exercise or diet alone unproven, highlighting the need for individualized care.
Yesterday
