

Loading, please wait...
Loading, please wait...
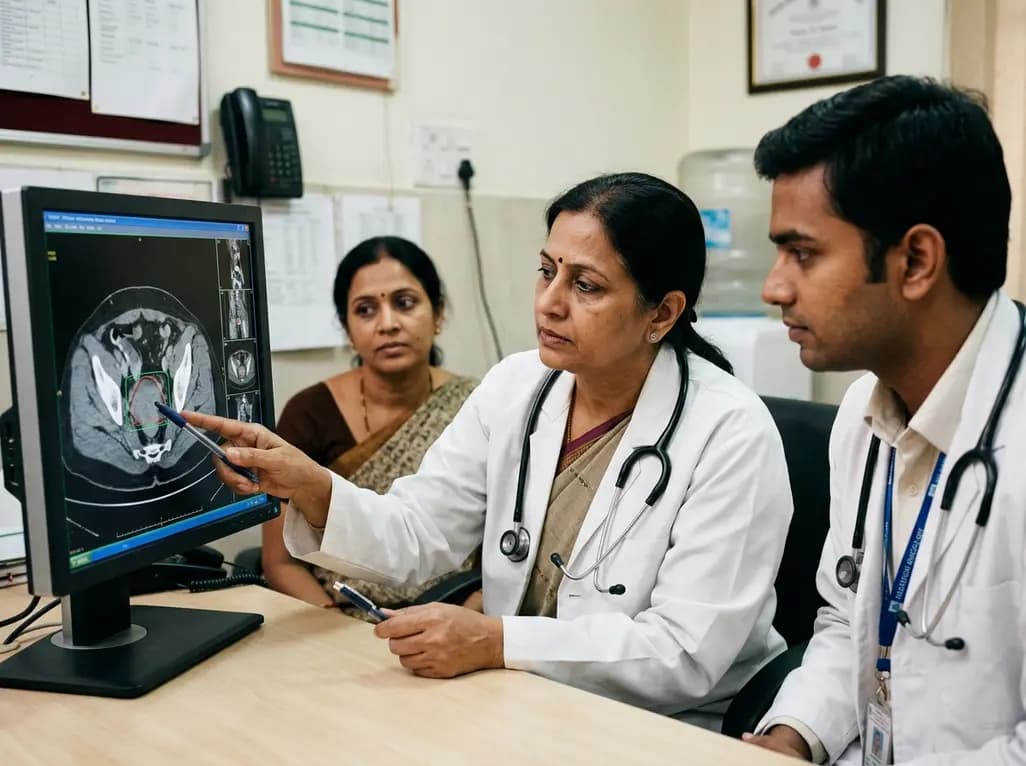
Clinicians routinely evaluate post-hysterectomy radiation volumes to balance locoregional tumor control against normal tissue toxicity in gynecologic oncology. A recent clinical investigation evaluated the role of small-pelvic adjuvant radiotherapy in patients with early-stage cervical cancer who lack classic high-risk pathological features. By sparing the common iliac nodal basins, field de-escalation aims to preserve intestinal and hematologic safety. However, physicians must determine whether smaller field boundaries maintain equivalent long-term oncologic efficacy across various intermediate-risk tumor characteristics.
Standard postoperative management for intermediate-risk early cervical carcinoma traditionally employs whole-pelvic irradiation to prevent regional pelvic recurrence. Nevertheless, expansive radiation fields unavoidably expose substantial volumes of active bone marrow and mobile small bowel loops to radiation. Therefore, radiation oncologists explored volume de-escalation by intentionally omitting common iliac lymph node coverage in surgically staged, node-negative patients. This targeted approach specifically seeks to lessen acute gastrointestinal morbidity and preserve long-term hematologic function. Researchers structured this clinical evaluation to compare small-pelvic adjuvant radiotherapy directly against conventional whole-pelvic fields in node-negative, margin-negative cohorts. Consequently, the investigation assessed whether reducing superior radiation targets compromises regional disease control or overall patient survival. The gynecologic oncology community continuously seeks to optimize toxicity profiles without sacrificing curative potential in early-stage management. Thus, establishing evidence-based anatomical boundaries remains vital for modern precision radiotherapy planning.
Initial crude comparisons indicated that whole-pelvic radiation achieved higher five-year disease-free survival rates than small-pelvic approaches. However, baseline clinical imbalances between treatment cohorts accounted for these early numerical discrepancies. Investigators subsequently applied rigorous propensity score matching to balance confounding clinicopathological variables between both study arms. After propensity score matching adjustment, the five-year disease-free survival difference resolved entirely, reaching ninety point eight percent versus eighty-seven percent. Furthermore, five-year locoregional control rates demonstrated no statistically significant differences between whole-pelvic and field-reduced treatments. These adjusted outcomes confirm that small-pelvic fields generally deliver adequate pelvic disease suppression in appropriately selected intermediate-risk cases. Accordingly, routine nodal coverage up to the common iliac level may represent overtreatment for low-burden cohorts. Nevertheless, precise patient selection criteria remain essential before clinicians safely omit standard lymphatic volumes.
To identify which patient subgroups safely tolerate reduced radiation margins, researchers performed recursive partitioning analysis. The analysis established three distinct risk tiers based on post-resection clinical and pathological measurements. Notably, tumor diameter emerged as the single most critical prognostic threshold in this decision model. In patients presenting with a primary tumor diameter of three point two centimeters or greater, whole-pelvic irradiation delivered distinctly superior therapeutic outcomes. Specifically, the whole-pelvic group achieved a ninety-six point seven percent five-year overall survival compared to only seventy-seven point one percent with field reduction. Similarly, five-year disease-free survival favored whole-pelvic radiation at ninety-six point seven percent versus seventy point eight percent. Consequently, larger tumor volume signals a heightened risk of lymphatic micrometastases along proximal nodal chains. Therefore, oncologists must retain full pelvic fields when tumor measurements meet or exceed this critical cutoff.
Detailed organs-at-risk dosimetry demonstrated substantial anatomical advantages when clinicians omitted the common iliac stations. Specifically, treatment planning showed meaningful reductions in radiation exposure to adjacent active bone marrow and small intestine segments. Conversely, rectal radiation metrics displayed no significant differences between the two treatment planning strategies because lower pelvic boundaries remained identical. These dosimetric savings translated directly into measurable clinical safety benefits for treated patients. Grade one and two gastrointestinal adverse events occurred twice as frequently in the whole-pelvic cohort compared to the small-field group. In addition, lower radiation absorption across pelvic bones helps preserve systemic hematologic function during adjuvant therapies. Thus, smaller treatment volumes provide meaningful quality-of-life benefits and lower chronic bowel toxicity risks. Clinicians can confidently recommend small fields when pathological tumor diameter remains well below the risk threshold.
These retrospective findings provide practical guidance for customizing postoperative treatment volumes in node-negative cervical cancer. Clinicians must meticulously evaluate macroscopic tumor dimensions alongside microscopic stromal invasion and lymphovascular space involvement. While small radiation fields substantially reduce mild intestinal complications, undertreating proximal lymphatic pathways compromises overall survival in bulky tumors. Therefore, multidisciplinary teams should avoid field reduction in women with tumors measuring three point two centimeters or larger. Conversely, patients with smaller tumors and isolated intermediate-risk factors can safely receive de-escalated pelvic treatment to avoid unnecessary toxicities. Furthermore, radiation oncologists must integrate advanced contouring tools and image guidance to verify adequate target coverage. Moving forward, prospective randomized trials will further refine patient selection criteria and validate these dimensional cutoff points.
Small-pelvic adjuvant radiotherapy targets the central pelvic tumor bed and lower pelvic lymph node basins while intentionally excluding the common iliac lymph nodes. In contrast, standard whole-pelvic radiation covers the pelvic cavity alongside internal, external, and common iliac lymphatic chains. Consequently, the small-pelvic technique delivers lower radiation doses to the small intestine and active bone marrow, significantly decreasing treatment-related gastrointestinal side effects in selected early-stage patients.
Patients with a primary tumor diameter of three point two centimeters or larger are poor candidates for field reduction. Clinical data show that these patients experience significantly worse disease-free and overall survival when clinicians omit common iliac node coverage. In addition, individuals with confirmed positive pelvic lymph nodes, parametrial extension, or positive surgical margins require comprehensive whole-pelvic radiation, often paired with concurrent chemotherapy rather than small fields.
Field reduction significantly lowers radiation exposure to the small bowel and pelvic bone marrow. As a result, patients experience a lower incidence of acute and chronic grade one and two gastrointestinal toxicities, such as radiation enteritis, cramping, and diarrhea. Moreover, sparing active marrow regions helps prevent acute myelosuppression and hematologic complications, supporting better tolerance and improving overall post-surgical quality of life.
Disclaimer: This content is for informational and educational purposes only and does not constitute medical advice, diagnosis, or treatment. Healthcare professionals should rely on their clinical judgment and refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A study evaluates small-pelvic adjuvant radiotherapy in early-stage cervical cancer without high-risk factors post-hysterectomy. While it significantly reduces mild bowel toxicity, patients with tumor diameter ≥3.2 cm experience inferior survival, indicating that field reduction requires precise risk stratification.
4 weeks back
UK Research and Innovation is deploying £80 million across the NHS to trial nine cutting-edge technologies. The initiative features seven-minute brain MRIs, blood biomarker assays, and predictive AI tools, aiming to evaluate 92% of suspected cases within 18 weeks and overcome lengthy diagnostic backlogs.
Today

A mixed-methods study identifies key drivers of PMTCT service utilization among adolescent girls and young women aged 15-24. Highlighting age disparities, PrEP uptake, and systemic barriers, the evidence guides clinicians toward adolescent-responsive, integrated maternal HIV prevention protocols.
Today

PepsiCo and Monster Beverage have challenged the FSSAI ban on the energy drink label in Indian courts. While companies highlight supply disruptions, regulatory actions spotlight severe cardiovascular and metabolic risks associated with excessive caffeine, sugar, and taurine consumption, especially in adolescents.
Today

A narrative review investigates whether the articularis genus muscle functions as an independent anatomical entity or blends with the vastus intermedius. We evaluate its morphology, role in retracting the suprapatellar bursa, and direct clinical significance in anterior knee pain and arthroplasty.
Today

A Bayesian multilevel meta-analysis reveals that aerobic training combined with moderate carbohydrate restriction modestly lowers HbA1c in type 2 diabetes. However, sparse data and very low certainty leave incremental benefits over exercise or diet alone unproven, highlighting the need for individualized care.
Yesterday
