

Loading, please wait...
Loading, please wait...

Clinical management of hypertension demands vigilant therapeutic adjustment because ambient weather directly influences vascular hemodynamics. Achieving consistent seasonal blood pressure control presents a recurring obstacle for healthcare professionals globally. Cold temperatures frequently elevate vascular resistance, prompting sudden blood pressure destabilization during winter. Consequently, clinicians observe significant blood pressure fluctuations across seasons. Understanding which dual therapies maintain stability is therefore crucial.
Environmental temperature variations exert a substantial impact on human cardiovascular physiology. During cold weather, cutaneous vasoconstriction occurs to conserve central core body heat. Therefore, systemic peripheral vascular resistance rises noticeably, driving both systolic and diastolic blood pressure upward. In addition, cold exposure stimulates the sympathetic nervous system and triggers increased secretion of circulating norepinephrine. This neurohormonal cascade elevates cardiac workload and substantially increases myocardial oxygen demand. As a result, epidemiological studies consistently demonstrate a higher incidence of acute myocardial infarction and ischemic stroke during winter months.
Furthermore, office blood pressure readings frequently surge during winter clinic visits, creating persistent therapeutic dilemmas for treating doctors. When clinicians observe elevated clinic numbers, they must decide whether to escalate medication doses immediately or await warmer temperatures. However, inappropriate dose escalation can cause symptomatic hypotension when ambient temperatures rise in spring. In addition, seasonal transitions alter patient lifestyle habits, dietary sodium intake, and regular physical activity patterns. Consequently, maintaining long-term hemodynamic stability requires resilient pharmacological regimens that minimize seasonal volatility without requiring frequent medication adjustments.
To determine how seasonal variations influence combination therapies, investigators conducted a rigorous 24-week therapeutic clinical trial. The study enrolled 560 hypertensive participants to compare two widely prescribed single-pill dual combinations. Specifically, participants initiated treatment with either amlodipine/benazepril at 5/10 mg daily or benazepril/hydrochlorothiazide at 10/12.5 mg daily. The trial protocol permitted dosage titration to 10/20 mg daily or 20/25 mg daily, respectively, whenever blood pressure remained uncontrolled during scheduled follow-up visits.
Furthermore, investigators monitored treatment outcomes through comprehensive clinic evaluations and 24-hour ambulatory blood pressure monitoring. Clinicians recorded standardized office blood pressure at every scheduled clinic visit throughout the follow-up period. In addition, participants underwent ambulatory monitoring at baseline and upon completing 24 weeks of active therapy. This dual monitoring strategy provided an objective assessment of true circadian hemodynamics beyond isolated clinic visits. Ultimately, 511 patients successfully completed the full 24-week protocol while maintaining their assigned therapeutic regimens. Researchers subsequently stratified patient outcomes according to the specific season in which patients commenced therapy to assess seasonal vulnerability.
The trial revealed striking differences in dose titration patterns between the two pharmacological combination groups. Overall, the proportion of patients needing dosage up-titration varied significantly across enrollment seasons in the benazepril/hydrochlorothiazide cohort. Specifically, the titration rate fluctuated markedly depending on whether patients began treatment during winter or warmer seasons. In contrast, patients receiving the amlodipine/benazepril combination showed remarkable consistency across all four seasons. Statistical analysis demonstrated no significant seasonal variation in up-titration for the calcium channel blocker cohort.
Most importantly, the disparity between the two regimens became pronounced among 134 patients who initiated therapy during winter. Within this winter cohort, 18.9% of patients on benazepril/hydrochlorothiazide required medication up-titration to achieve blood pressure targets. Conversely, only 5.0% of patients receiving amlodipine/benazepril required dose escalation during identical winter conditions. This between-group difference was statistically significant and clinically meaningful. However, among the 377 patients initiating therapy in other seasons, titration rates did not differ between treatments. Therefore, winter weather specifically unmasked a therapeutic vulnerability in the diuretic-based regimen.
The physiological mechanisms explaining the superiority of amlodipine/benazepril during cold weather involve distinct vascular pathways. Low environmental temperatures stimulate cutaneous alpha-adrenergic receptors, which induces intense peripheral vasoconstriction. Amlodipine, a dihydropyridine calcium channel blocker, selectively inhibits L-type calcium channels within vascular smooth muscle cells. Consequently, amlodipine promotes direct arteriolar dilation and effectively blunts cold-induced vasospasm throughout the peripheral circulation. Moreover, amlodipine possesses an exceptionally long elimination half-life of 30 to 50 hours. This prolonged duration of action smooths out hemodynamic fluctuations across changing daily temperatures.
In contrast, hydrochlorothiazide functions primarily by promoting renal natriuresis and reducing circulating plasma volume. However, cold weather naturally promotes diuresis through cold-induced natriuresis and decreased insensible perspiration. Therefore, adding a pharmacological diuretic during cold weather provides diminishing hemodynamic returns against elevated peripheral resistance. Furthermore, volume depletion can trigger compensatory renin-angiotensin-aldosterone system activation, which counteracts blood pressure reduction. By pairing the direct vasodilatory action of amlodipine with benazepril, clinicians achieve comprehensive vascular protection that prevents winter blood pressure escape.
These trial findings carry significant practical implications for physicians managing hypertension across diverse regions in India. Many parts of northern, central, and eastern India experience sharp temperature drops during winter months. During these seasonal transitions, Indian clinics regularly report surges in uncontrolled hypertension and cerebrovascular events. Furthermore, dietary sodium consumption in India remains substantially higher than international targets, which complicates diuretic efficacy. Initiating antihypertensive therapy with a dihydropyridine calcium channel blocker and an ACE inhibitor offers predictable hemodynamic control throughout unpredictable seasonal swings.
In addition, choosing a seasonally resilient regimen minimizes frequent dose adjustments and reduces patient anxiety. When clinicians prescribe amlodipine/benazepril, they can expect sustained blood pressure control even when patients start therapy in midwinter. Conversely, clinicians who prescribe diuretic combinations in winter must monitor patients closely for inadequate control. Moreover, fixed-dose single-pill combinations improve long-term adherence by streamlining daily pill burden. Ultimately, adopting calcium channel blocker-based dual therapy represents an evidence-based strategy to maintain stable blood pressure control year-round.
Cold temperatures stimulate cutaneous thermoreceptors and trigger immediate sympathetic nervous system activation. This physiological reflex causes peripheral vasoconstriction to prevent internal heat loss. Consequently, systemic vascular resistance increases, which elevates both office and ambulatory blood pressure readings. In addition, exposure to cold weather suppresses insensible perspiration and stimulates cold-induced natriuresis. These combined vascular and neurohormonal adaptations increase myocardial workload, thereby raising cardiovascular event risks during colder months.
Amlodipine directly antagonizes L-type calcium channels in arterial smooth muscle, promoting potent peripheral vasodilation that counteracts cold-induced vasoconstriction. In contrast, hydrochlorothiazide primarily reduces plasma volume, which fails to relieve peripheral vascular resistance effectively. Furthermore, amlodipine has a prolonged half-life that provides smooth, 24-hour hemodynamic stability across fluctuating ambient temperatures. Consequently, patients initiating amlodipine/benazepril in winter achieved robust blood pressure targets with significantly fewer dosage up-titrations than those receiving diuretic therapy.
Clinicians should avoid premature drug adjustments based solely on occasional elevated office readings during winter visits. Instead, physicians ought to confirm persistent hypertension through out-of-office ambulatory or home blood pressure monitoring before changing regimens. If winter blood pressure remains consistently elevated, escalating a calcium channel blocker provides more effective vascular relief than increasing diuretic doses. Furthermore, clinicians must monitor patients closely during spring to prevent overtreatment hypotension as temperatures rise.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References
Ye XF et al. Seasonal variation in the office and ambulatory blood pressure control in patients treated with two dual antihypertensive therapies. Hypertens Res. 2026 Sep 11. doi: 10.1038/s41440-026-02791-6. PMID: 42728325.
Jamerson K, Weber MA, Bakris GL, Dahlöf B, Pitt B, Shi V, et al. Benazepril plus amlodipine or hydrochlorothiazide for hypertension in high-risk patients. N Engl J Med. 2008;359(23):2417-2428. doi: 10.1056/NEJMoa0806182.
Stergiou GS, Palatini P, Modesti PA, Asayama K, Bilo G, de la Sierra A, et al. Seasonal variation in blood pressure: Pathophysiological mechanisms and clinical implications. J Hypertens. 2020;38(7):1235-1243. doi: 10.1097/HJH.0000000000002394.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A 24-week trial shows that patients starting amlodipine/benazepril maintain stable blood pressure across all seasons, whereas those on benazepril/hydrochlorothiazide require significantly more up-titration when initiated in winter (18.9% vs. 5.0%), highlighting amlodipine's superior seasonal hemodynamic stability.
last month

An observational study from the NIH All of Us Research Program reveals that adding a multi-ancestry polygenic risk score to machine learning models provides only modest improvements in predicting adult weight gain, underscoring the enduring significance of routine clinical and lifestyle factors.
Today

A study in JAMIA Open shows lightweight open-source reasoning LLMs achieve up to 95% sensitivity and accelerate evidence synthesis screening by nearly twentyfold, presenting a cost-effective, scalable AI solution for biomedical research and systematic reviews.
Yesterday

A landmark study details how an enterprise pediatric remote patient management model expanded from a single cardiology pilot to 16 diverse specialty programs by combining centralized digital operations with specialty clinical leadership.
Yesterday
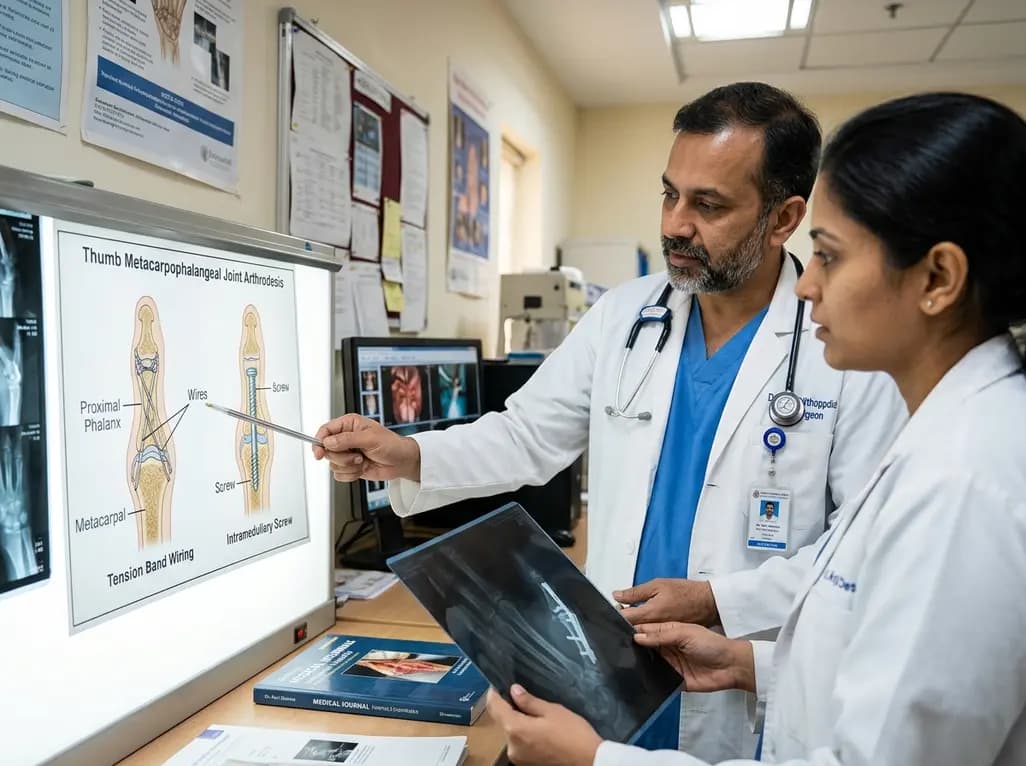
A comparative review of tension band wiring and intramedullary screw fixation in thumb metacarpophalangeal arthrodesis, evaluating union rates, hardware complications, and clinical outcomes.
Yesterday

A breakthrough ultrathin multimodal sensor decouples physical hemodynamic monitoring from disposable electrochemical calibration, achieving long-term wearable glucose prediction with 81.36% accuracy and a 9.12% MARD. This offers a robust, drift-free solution for outpatient metabolic surveillance.
Yesterday
