

Loading, please wait...
Loading, please wait...

Surgeons frequently encounter postoperative fatigue in neurosurgery, yet clinicians often undervalue its prolonged impact on functional recovery. Patients undergoing cranial and spinal interventions routinely report overwhelming exhaustion that persists long after discharge. Although clinicians historically categorized fatigue as an unavoidable consequence of surgical trauma, emerging prospective evidence demonstrates intricate connections with psychological and neurocognitive parameters. Therefore, identifying the distinct clinical courses of cranial versus spinal procedures remains crucial. In addition, recognizing how preoperative emotional health influences postoperative stamina enables surgeons to optimize recovery pathways. This article examines recent prospective multicenter data detailing the physiological, psychological, and cognitive dynamics that govern post-surgical recovery in modern neurosurgical practice.
Postoperative exhaustion represents a multifaceted challenge that extends beyond simple physical tiredness. In a landmark prospective multicenter investigation, investigators tracked 182 neurosurgical patients undergoing elective cranial and spinal procedures across four centers over twelve months. Notably, baseline assessments revealed that 59% of cranial surgery candidates and 68% of spinal surgery candidates experienced significant preoperative fatigue. Consequently, surgeons must realize that many patients enter the operating room already depleted.
Furthermore, researchers utilized validated assessment instruments, including the Fatigue Severity Scale and the Christensen Fatigue Scale, to evaluate symptom progression. The findings demonstrated that preoperative exhaustion robustly predicted higher levels of postoperative fatigue across both cohorts. Therefore, neurosurgical teams cannot treat fatigue as an unexpected acute event. Instead, clinical teams must recognize it as a continuous burden that pre-existing metabolic and emotional factors intensify. When surgeons recognize this vulnerability early, they can tailor perioperative expectations and initiate timely supportive interventions.
The longitudinal data reveal remarkably divergent recovery courses between cranial and spinal surgical patients. Specifically, cranial surgery patients experienced an acute, significant elevation in Fatigue Severity Scale scores at one week postoperatively, with an average score increase of 0.46. However, this postoperative surge proved temporary, as fatigue levels reverted to baseline by six weeks. Thus, cranial patients experience a transient acute physiological toll that resolves as tissue inflammation recedes.
In contrast, spinal surgery patients followed an entirely different trajectory of functional recovery. Although spinal patients exhibited a higher baseline fatigue rate of 68%, they suffered no significant spike in fatigue immediately following intervention. Moreover, these spinal patients demonstrated marked fatigue improvement by six weeks postoperatively, and they successfully sustained these clinical gains through twelve months. Consequently, successful decompressive or stabilizing spinal interventions alleviate the chronic constitutional burden that unmanaged spinal pathology produces. Understanding these divergent timelines empowers neurosurgeons to provide reassuring, realistic recovery milestones during discharge planning.
Affective disorders exert a profound influence on postoperative recovery and fatigue persistence in neurosurgical patients. Prospective assessments using the Hospital Anxiety and Depression Scale demonstrated that preoperative depression directly predicted higher postoperative fatigue severity. Additionally, cranial patients demonstrated significantly worse depression scores at one week postoperatively before returning to baseline levels at six weeks. This temporary mood decline likely reflects acute surgical stress and perioperative medication adjustments.
Conversely, spinal surgery patients exhibited no worsening of depression after their operations. Instead, their depressive symptoms steadily improved from six weeks onward, maintaining progress throughout twelve months. Furthermore, anxiety scores improved significantly across both cranial and spinal cohorts following surgical intervention. This positive psychological shift highlights how relieving surgical uncertainty and treating pathology mitigates situational distress. Nonetheless, persistent postoperative pain significantly magnified fatigue, depression, and anxiety throughout follow-up. Therefore, clinicians must treat postoperative pain aggressively, because uncontrolled nociceptive input directly drives psychiatric distress and prolongs physical exhaustion.
Subjective cognitive complaints frequently disrupt patient rehabilitation following major neurosurgical procedures. In the multicenter study, researchers evaluated self-reported cognitive failures using the Cognitive Failures Questionnaire. Interestingly, cognitive failure scores demonstrated measurable improvement at one week and six weeks postoperatively before returning to preoperative levels in both cohorts. Consequently, patients often experience a transient window of perceived cognitive clarity once surgical decompression relieves acute intracranial mass effect or severe chronic pain.
However, the data identified an alarming link between affective distress and persistent cognitive dysfunction. Specifically, patients with elevated Hospital Anxiety and Depression Scale scores of eight or higher exhibited a 6-point worsening in cognitive failure scores. Moreover, linear regression confirmed that postoperative fatigue strongly correlated with subjective cognitive impairment. Thus, cognitive complaints often mirror mood disturbances and chronic fatigue rather than structural brain injury. Surgeons must therefore reassure patients that mental fog usually stems from systemic exhaustion and emotional distress.
These prospective longitudinal findings carry immediate practical implications for neurosurgical practice in tertiary care settings. First, multidisciplinary teams should systematically screen neurosurgical candidates for pre-existing fatigue, anxiety, and depressive symptoms during preoperative evaluations. Because baseline psychological distress strongly predicts severe postoperative fatigue, early risk stratification allows clinicians to set realistic recovery expectations. Furthermore, prehabilitation protocols that address emotional distress and optimize physical stamina can significantly improve postoperative resilience.
Second, pain management demands meticulous multimodal attention throughout acute and subacute recovery phases. Because postoperative pain directly intensifies fatigue, anxiety, and depression, comprehensive analgesia serves as a critical protective intervention. Additionally, clinicians should counsel cranial patients that their fatigue and mood dips represent transient one-week phenomena that resolve by six weeks. Meanwhile, spinal teams can reassure patients that relieving structural pain offers sustained fatigue relief over twelve months. Ultimately, incorporating targeted psychological screening and aggressive pain control into clinical pathways fosters superior neurosurgical outcomes.
Postoperative fatigue arises from a combination of systemic surgical stress, neuroinflammatory cascades, tissue trauma, and pre-existing constitutional exhaustion. In addition, unmanaged postoperative pain, psychological distress, and disrupted sleep architectures significantly amplify this exhaustion. Preoperative depression and high baseline fatigue also directly predict greater symptom severity following both cranial and spinal operations.
Cranial surgery patients typically experience an acute increase in fatigue and depression during the first postoperative week, which reverts to baseline by six weeks. Conversely, spinal surgery patients avoid acute fatigue spikes and demonstrate significant, sustained reductions in fatigue and depression from six weeks through twelve months postoperatively.
Elevated anxiety and depression substantially diminish executive resources, processing speed, and daily attentional capacity. In neurosurgical cohorts, patients with high mood disorder scores exhibit significantly higher cognitive failure rates. Therefore, subjective cognitive complaints frequently reflect psychological distress, uncontrolled pain, and mental exhaustion rather than permanent surgical neurological damage.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A prospective multicenter longitudinal study reveals distinct trajectories for postoperative fatigue in neurosurgery. Cranial patients suffer acute one-week fatigue spikes, whereas spinal patients experience sustained relief. Preoperative depression and pain strongly drive prolonged fatigue and cognitive decline.
Today
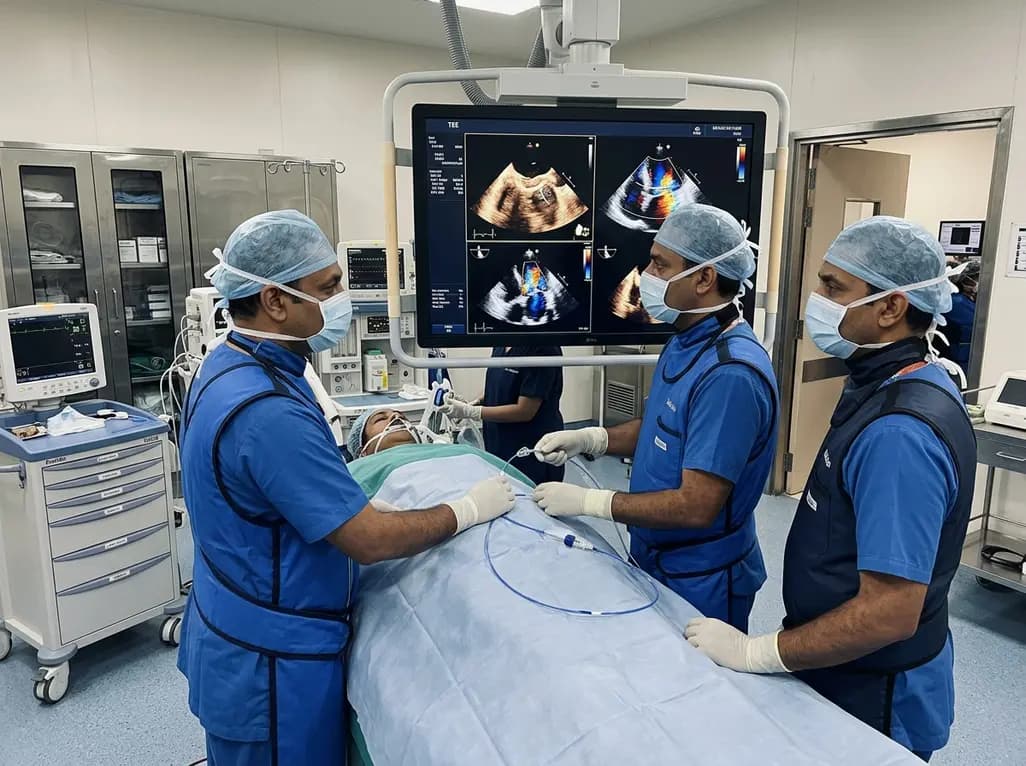
Transcatheter edge-to-edge repair (TEER) successfully treated severe mitral regurgitation from a posterior leaflet perforation. Guided by 3D multiplanar reconstruction, operators sandwiched the defect using two MitraClip devices, providing safe hemodynamic recovery without requiring open-heart surgery.
Today
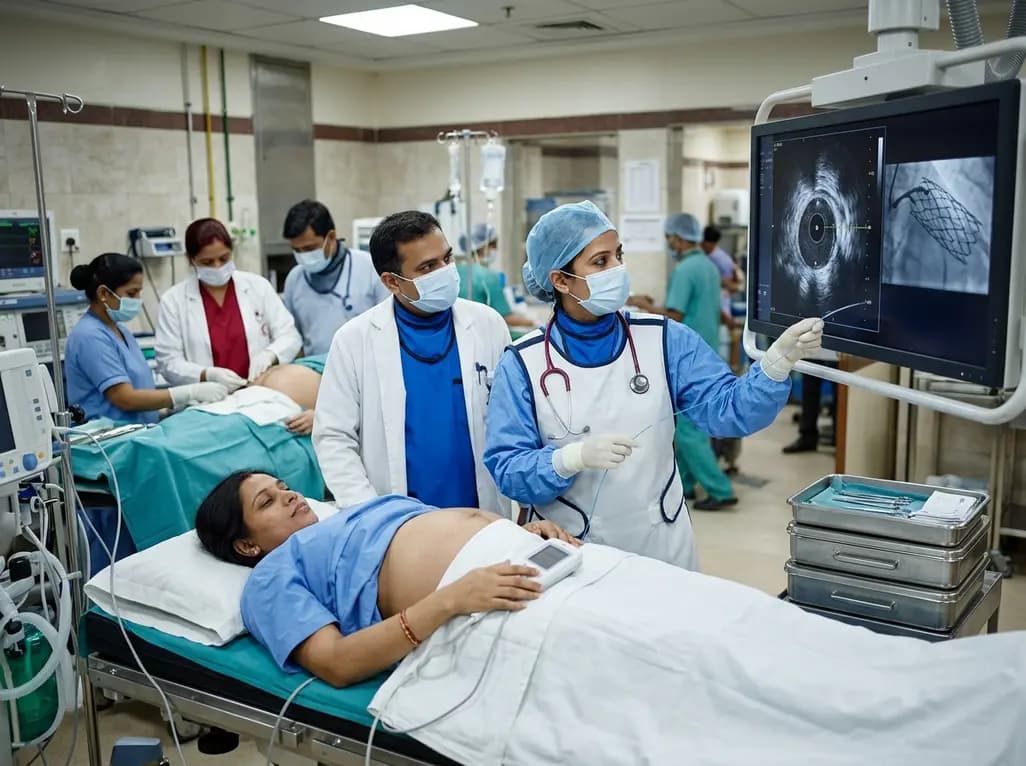
A 32-year-old gravida at 38 weeks with anterior STEMI underwent emergent IVUS-guided PCI and successful cesarean delivery under uninterrupted DAPT, highlighting cardio-obstetric care.
Today

A systematic review and meta-analysis of 5,406 participants reveals that tirzepatide significantly reduces hsCRP by 34.3%, improves cardiorenal biomarkers, and enhances functional capacity and exercise endurance in patients with heart failure.
Today

A landmark biomechanical study demonstrates that sports bra support and running shoe cushioning interact significantly to influence tibial acceleration, breast motion, and comfort in female runners, providing crucial insights for clinical counseling in sports medicine and women's health.
Yesterday
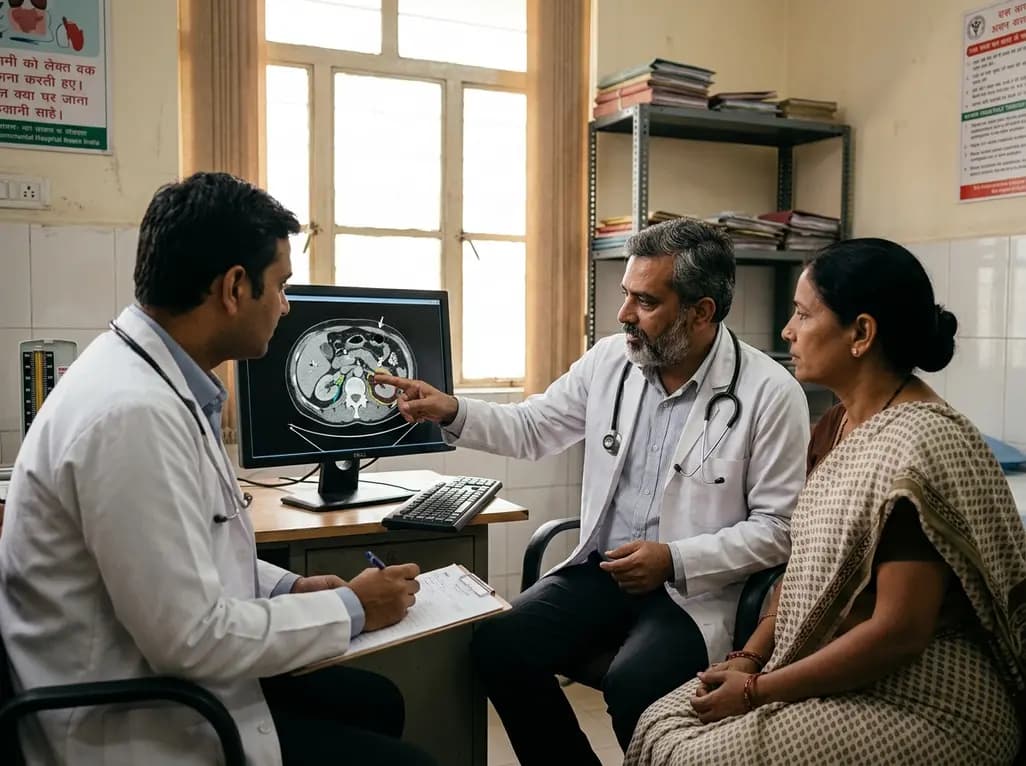
New ADIPO-CKD study findings demonstrate that both GLP-1 receptor agonists and SGLT2 inhibitors significantly reduce perirenal adipose tissue thickness in chronic kidney disease patients, with GLP-1 therapy achieving greater reductions, highlighting a novel mechanism for cardiorenal metabolic protection.
Today
