

Loading, please wait...
Loading, please wait...

Global health authorities recently raised heightened concerns following the death of a 28-year-old laboratory worker at an anti-plague research institute in Siberia. The researcher succumbed to severe pneumonia of undetermined origin, which prompted Russian public health officials to place approximately 200 close contacts under strict medical quarantine. Consequently, the World Health Organization requested comprehensive clinical data and laboratory findings under the International Health Regulations framework. For medical professionals across the globe, this acute respiratory event highlights why rigorous pneumonic plague surveillance and infection control protocols remain essential in hospital and reference settings.
Regional health agencies in Russia reported that the deceased laboratory employee developed fulminant respiratory symptoms before dying from rapid respiratory failure. Although local watchdog agencies noted that initial screenings detected no Yersinia pestis bacilli among isolated contacts, the World Health Organization stressed that timely verification remains imperative. In addition, conflicting reports emerged regarding a potential secondary respiratory case in the same regional workforce. Therefore, international surveillance bodies must evaluate all primary laboratory specimens, containment integrity, and environmental exposures.
Under the International Health Regulations, signatory nations must report unusual or unexpected public health events within twenty-four hours. This global requirement prevents transboundary disease dissemination and ensures that frontline clinicians receive accurate diagnostic intelligence. When high-consequence laboratories report sudden fatalities, prompt disclosure safeguards the wider health system. Furthermore, medical epidemiologists depend on complete genomic and microbiological reports to establish whether accidental laboratory exposure or an unrelated community pathogen triggered the fatal respiratory decompensation.
Yersinia pestis is a Gram-negative coccobacillus capable of causing three major forms of plague: bubonic, septicemic, and pneumonic. Primary pneumonic plague occurs when an individual directly inhales infectious respiratory droplets or contaminated laboratory aerosols. Consequently, the pathogen bypasses peripheral lymphatic tissue and colonizes pulmonary alveoli directly. Once inhaled, the bacteria deploy a type III secretion system and inject cytotoxic Yop effector proteins into host macrophages and neutrophils. This virulent mechanism paralyzes normal phagocytosis and suppresses early inflammatory signaling.
Following a rapid incubation period of twenty-four to seventy-two hours, patients experience acute systemic toxicity. Typical early symptoms include sudden high fever, chills, profound myalgia, tachycardia, and progressive headache. However, respiratory symptoms escalate rapidly within twenty-four hours. Patients develop tachypnea, severe dyspnea, pleuritic chest discomfort, and a productive cough. Furthermore, the sputum characteristically progresses from watery or mucoid to copious, frothy, bright red hemoptysis. Because pulmonary consolidation spreads bilaterally, severe ventilation-perfusion mismatch leads to fatal acute respiratory distress syndrome without immediate medical intervention.
Because secondary pneumonic plague can develop from untreated bubonic disease, clinicians must sustain heightened clinical vigilance. Frontline physicians working in emergency rooms and intensive care units must incorporate pneumonic plague surveillance into routine differential diagnoses for unexplained acute respiratory failure. In particular, clinicians should promptly question patients about recent animal contact, travel to endemic natural foci, or occupational laboratory exposure. When an otherwise healthy young adult deteriorates precipitously with bloody sputum, physicians must immediately flag the case for specialized microbiological screening.
Differential diagnoses frequently encompass severe bacterial pneumonia caused by Streptococcus pneumoniae, Legionella pneumophila, or Staphylococcus aureus. In addition, viral pathogens like influenza, severe acute respiratory syndrome coronavirus, and hantavirus can produce overlapping radiographic consolidations. However, primary pneumonic plague features an unusually rapid clinical trajectory that progresses to refractory septic shock within thirty-six hours. Consequently, healthcare facilities must maintain standardized clinical screening algorithms to identify suspicious presentations before patient triage finishes.
Rapid diagnostic identification remains vital for patient survival, but clinical specimen collection carries severe biohazard risks. Clinicians must collect pre-treatment sputum samples, blood cultures, and bronchoalveolar aspirates whenever clinically feasible. Sputum smears often demonstrate bipolar staining, showing a classic safety-pin appearance under Wayson or Giemsa staining. Furthermore, automated polymerase chain reaction assays and rapid antigen detection targeting the capsular F1 antigen offer rapid presumptive confirmation. Serological tests like enzyme-linked immunosorbent assays can also demonstrate diagnostic antibody titer increases.
Nevertheless, diagnostic laboratories must process potential Yersinia pestis specimens strictly under Biosafety Level 3 precautions. Laboratory personnel should handle all open culture plates and infectious liquids inside certified biosafety cabinets. Because aerosolization poses an extreme occupational hazard, technicians must never perform vortexing or centrifugation without sealed safety cups. If a diagnostic facility lacks appropriate biocontainment equipment, supervisors should immediately route specimens to designated state or national reference laboratories without initiating dangerous subcultures.
Immediate airborne and droplet containment protects healthcare workers from secondary pulmonary infection. Hospital teams must immediately place suspected patients into single-occupancy negative-pressure isolation rooms. Furthermore, healthcare personnel attending the patient must wear full personal protective equipment, including particulate respirators, fluid-resistant gowns, gloves, and eye shields. Attending teams should maintain these droplet precautions until the patient receives effective antimicrobial therapy for at least forty-eight to seventy-two hours and exhibits clinical improvement.
Empirical antibiotic therapy must commence immediately upon clinical suspicion because delaying antimicrobial treatment beyond twenty-four hours after symptom onset dramatically elevates mortality. Aminoglycosides, particularly streptomycin and gentamicin, serve as traditional first-line bactericidal agents. Alternatively, intravenous fluoroquinolones such as ciprofloxacin and levofloxacin offer outstanding pulmonary tissue penetration and bactericidal efficacy. In addition, oral doxycycline or ciprofloxacin provides effective post-exposure prophylaxis for close contacts, who must remain under active temperature surveillance for seven consecutive days.
Q1: What are the primary transmission routes of pneumonic plague in healthcare and laboratory settings?
Pneumonic plague transmits predominantly through the inhalation of infectious respiratory droplets expelled by coughing patients. In laboratory environments, accidental aerosol generation during centrifugation, pipetting, or handling culture materials represents an additional direct exposure pathway. Because droplet transmission requires close face-to-face contact, individuals standing within two meters of an active patient face significant risk. Therefore, healthcare staff must implement strict droplet precautions and wear fitted respirators immediately.
Q2: How does pneumonic plague differ clinically from severe community-acquired bacterial pneumonia?
Primary pneumonic plague progresses far more rapidly than typical community-acquired pneumonia, often causing respiratory collapse and shock within thirty-six hours. While standard bacterial pneumonia features localized alveolar infiltrates and purulent sputum, pneumonic plague characteristically produces copious, frothy, bright red hemoptysis alongside diffuse alveolar consolidations. In addition, the lack of clinical response to beta-lactam antimicrobials strongly suggests atypical virulent pathogens such as Yersinia pestis.
Q3: Which antibiotic regimens are recommended for immediate empirical therapy and post-exposure prophylaxis?
First-line therapeutic regimens for pneumonic plague include parenteral aminoglycosides like gentamicin or streptomycin, as well as intravenous fluoroquinolones like ciprofloxacin and levofloxacin. Clinicians must administer these agents within twenty-four hours of symptom onset to reduce mortality. For asymptomatic close contacts and laboratory personnel exposed to infectious aerosols, public health guidelines recommend oral post-exposure prophylaxis with doxycycline or ciprofloxacin twice daily for seven consecutive days.
Disclaimer: This content is for informational and educational purposes only. It does not constitute medical advice or replace professional judgment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Following the death of a Siberian plague laboratory worker from severe pneumonia, the WHO has requested transparent data under international regulations. Explore the clinical features of pneumonic plague, critical diagnostic pathways, isolation precautions, and empirical management protocols for clinicians.
Today
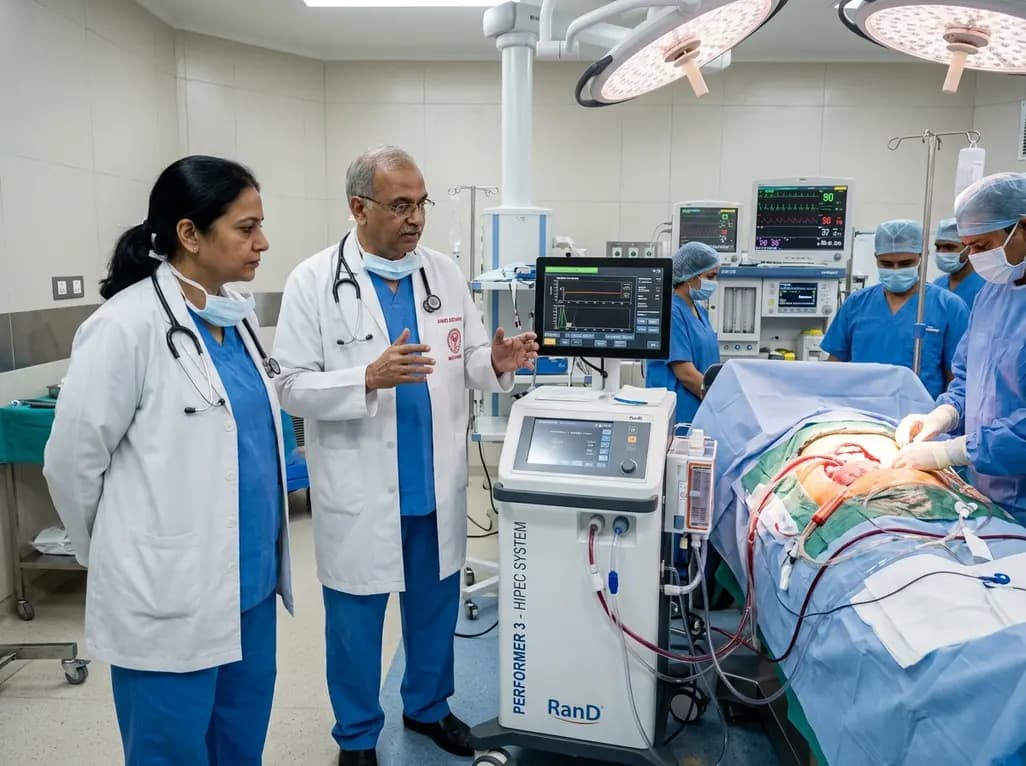
AIIMS Bathinda has inaugurated a specialized peritoneal oncology service featuring the RanD Performer 3 HIPEC platform. The facility offers cytoreductive surgery alongside hyperthermic intraperitoneal chemotherapy, transforming regional management for advanced ovarian, colorectal, and appendiceal malignancies.
Today

A cross-sectional study reveals that hypertension knowledge, illness perceptions, depression, and substance use significantly predict self-care behaviors. Addressing mental health and cognitive beliefs in primary care is crucial for optimal blood pressure control and cardiovascular disease prevention.
Today

This clinical overview examines recent advancements in lumbar disc herniation surgery, comparing microscopic and full-endoscopic discectomy while highlighting biportal techniques and emerging motion-preserving innovations for spine specialists.
Today
A breakthrough study reveals that loss of SELENOT in hypothalamic POMC neurons triggers premature cellular senescence, ATF6α stress activation, and ER calcium depletion, linking neuroendocrine decay to metabolic disease.
Today
