

Loading, please wait...
Loading, please wait...
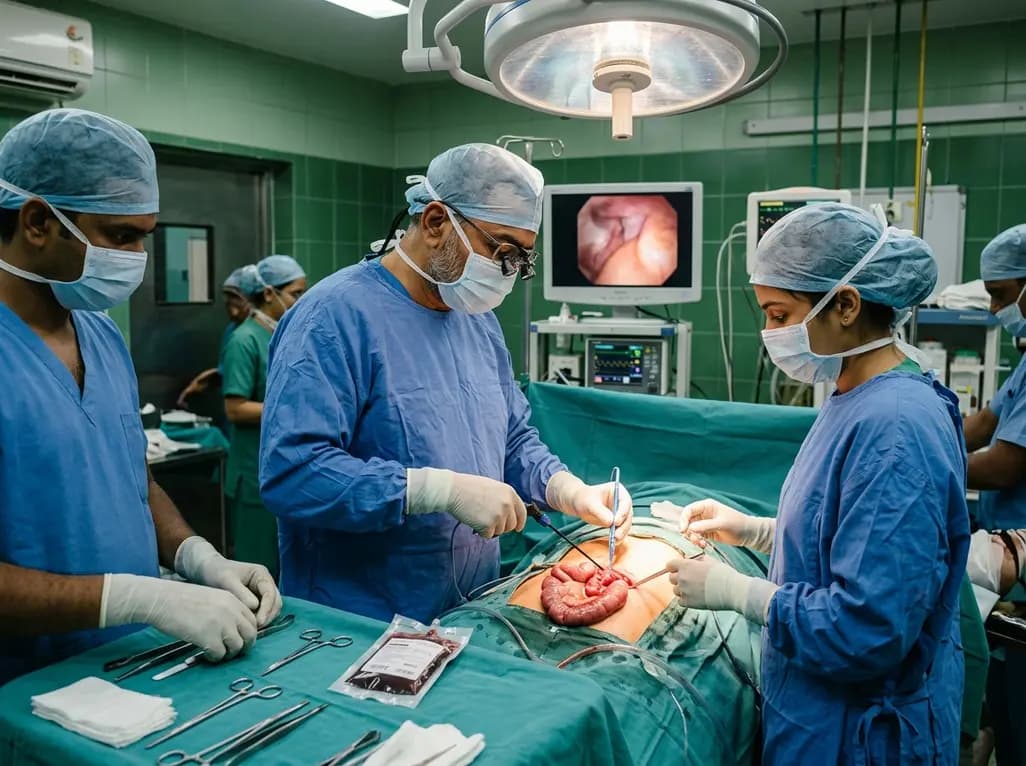
Small bowel diverticulosis represents a rare clinical condition that primarily affects elderly individuals. While colonic disease is widespread, jejunal involvement occurs in less than two percent of the population. However, complications such as diverticulitis, hemorrhage, and bowel rupture carry mortality rates exceeding forty percent. Clinicians face severe logistical and ethical challenges when perforated jejunal diverticulitis occurs in patients who refuse blood products. Delivering emergent operative intervention while honoring patient autonomy requires meticulous operative technique and advanced bloodless medical therapy.
Jejunal diverticula develop along the mesenteric border of the small intestine where nutrient vessels penetrate the muscularis layer. Consequently, these lesions represent false diverticula that lack a complete muscular coat. Most patients remain entirely asymptomatic for decades. However, luminal obstruction by enteroliths or inspissated food matter can trigger localized mucosal inflammation. This inflammatory cascade frequently progresses toward transmural necrosis and localized or generalized peritonitis.
Because the clinical signs mimic more common surgical emergencies, early bedside recognition remains notoriously difficult. Patients typically present with progressive central or left upper quadrant abdominal pain, high fever, and vomiting. Furthermore, physical examination commonly reveals localized tenderness, involuntary guarding, and abdominal distension. If spontaneous perforation occurs, systemic sepsis can escalate rapidly. Therefore, emergency clinicians must maintain a high index of suspicion in elderly individuals who develop unheralded acute abdominal distress without evident colonic or appendiceal pathology.
Diagnosing small bowel perforations before laparotomy demands prompt objective evaluation. Routine laboratory investigations usually demonstrate marked leukocytosis, elevated C-reactive protein concentrations, and variable degrees of metabolic acidosis. Nevertheless, these biochemical abnormalities lack anatomical specificity. In addition, plain erect chest radiographs fail to reveal free intra-abdominal air in up to half of all affected patients. This failure occurs because the mesentery often seals the microperforation quickly.
Consequently, contrast-enhanced computed tomography of the abdomen and pelvis serves as the definitive diagnostic investigation. Modern multidetector scans accurately demonstrate segmental jejunal wall thickening, focal mesenteric fat stranding, extraluminal fluid, and localized bubbles of pneumoperitoneum. Furthermore, radiologic imaging can effectively exclude active mechanical obstruction, volvulus, and mesenteric ischemia. When clinicians recognize these signs promptly, they can expedite operating room access before profound septic shock destabilizes hemodynamic performance.
Immediate surgical intervention provides definitive source control for complicated small bowel diverticular disease. Although stable patients with contained microperforations occasionally receive trial antibiotic therapy, free peritonitis demands urgent laparotomy. Surgeons must perform a thorough abdominal exploration to inspect the entire gastrointestinal tract. Because diverticula often appear in clusters, identifying the exact site of breakdown is paramount.
Segmental jejunal resection encompassing the perforated diverticular segment represents the gold standard operative strategy. Surgeons subsequently restore intestinal continuity using a tension-free, hand-sewn or stapled primary anastomosis. However, surgeons should avoid extensive, prophylactic small bowel resections for non-inflamed diverticula to prevent short bowel syndrome. In critical emergency settings, surgeons must maintain relentless, microscopic hemostasis. Operating teams must apply electrocautery judiciously, utilize modern vascular staplers, and inspect mesenteric cut edges carefully to eliminate residual occult bleeding.
Postoperative hemorrhage represents a life-threatening catastrophe that dramatically increases overall surgical morbidity. When an abdominal wall disruption or omental tear develops, patients can lose significant circulating red cell mass within hours. In patients who strictly refuse allogeneic transfusion, such as Jehovah's Witnesses, acute bleeding leaves clinicians with minimal physiological margin for error. Consequently, emergency re-exploration must happen without unnecessary delay.
Surgeons must re-enter the abdominal cavity swiftly to identify and ligate bleeding vessels directly. Furthermore, topical hemostatic agents, microfibrillar collagen, and gelatin sponges provide valuable adjunctive assistance. Concurrently, anesthesiologists must prioritize normothermia, correct metabolic acidosis, and maintain adequate end-organ perfusion. Fluid resuscitation requires balanced crystalloids rather than excessive non-buffered solutions to avoid severe dilutional coagulopathy. Clear surgical discipline and swift mechanical control prevent irreversible ischemic organ injury.
Successfully rehabilitating patients with severe anemia after major hemorrhage demands proactive patient blood management. Rather than relying on red cell transfusions, medical teams stimulate endogenous erythropoiesis using multimodal pharmacological therapy. High-dose intravenous iron formulations safely replenish iron stores without inducing enteric irritation. Concurrently, clinicians administer parenteral vitamin B12 and folic acid to support accelerated nucleated red cell division within the bone marrow.
In addition, synthetic erythropoiesis-stimulating agents can accelerate reticulocyte release in profound anemia. Critical care teams must also minimize phlebotomy losses through micro-sampling protocols and point-of-care testing. Clinicians should maintain strict cardiopulmonary monitoring, supplemental oxygen delivery, and judicious hemodynamic optimization to balance cellular oxygen demand. This collaborative clinical approach demonstrates that severe surgical complications can achieve complete recovery while honoring individual patient values.
Jejunal diverticula develop when increased intraluminal pressure forces mucosa through weak areas in the intestinal muscular layer where mesenteric vessels enter. When foreign material or enteroliths obstruct these false pouches, bacterial proliferation causes acute diverticulitis. Progressive mucosal ischemia and necrosis subsequently compromise the fragile wall, ultimately leading to free or contained small bowel perforation.
Surgeons generally avoid performing prophylactic bowel resection when encountering asymptomatic jejunal diverticula during routine abdominal operations. Uncomplicated diverticula carry a low lifetime complication rate, whereas unnecessary bowel resection introduces definite operative risks. Therefore, surgical management remains strictly reserved for acutely complicated presentations, including persistent diverticular hemorrhage, refractory mechanical obstruction, uncontained perforation, or generalized intra-abdominal sepsis.
Clinicians manage profound surgical anemia without donor blood by administering intravenous iron preparations to ensure high iron bio-availability for marrow production. Furthermore, daily supplementation with parenteral vitamin B12 and folic acid supports active erythrocyte synthesis. Physicians may also prescribe recombinant erythropoietin to stimulate erythroid progenitors, alongside minimal blood drawing protocols to preserve red cell volume.
Disclaimer: This content is for informational and educational purposes only. It is not intended to be a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition. Refer to the latest local and national guidelines for clinical practice.
References
Nikolovski A et al. Perforated jejunal diverticulitis in a Jehovah's Witness complicated by postoperative haemorrhage: a case report of successful bloodless management. J Surg Case Rep. 2026 Sep undefined. doi: 10.1093/jscr/rjag822. PMID: 42798336.
Harbi A et al. Perforated Jejunal Diverticulitis: A Retrospective Observational Study. Cureus. 2025 Nov;17(11):e97137. doi: 10.7759/cureus.97137.
Maqbool U et al. Perforated jejunal diverticulitis as an uncommon culprit of acute abdomen: A case report and review of literature. J Ayub Med Coll Abbottabad. 2024;36(4):833-837. doi: 10.55519/JAMC-04-13336.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Discover how clinicians successfully managed perforated jejunal diverticulitis and secondary postoperative hemorrhage in a Jehovah's Witness patient through prompt surgery, strict hemostasis, and non-blood hematinic therapy.
last month

A new study reveals that maternal longevity independently preserves offspring cognitive function into late life, highlighting the impact of matrilineal genetics and intergenerational support on cognitive reserve.
Today

Delhi is undergoing a major healthcare overhaul with enhanced Ayushman Bharat insurance up to ₹10 lakh, increased MBBS and PG medical training seats, expanded primary network mandirs, new tertiary neuro-ICUs, and public-private reproductive technology initiatives to build a resilient, preventative healthcare model.
Today
AI-enhanced remote monitoring successfully unmasks true asystole and high-grade atrioventricular block among numerous false implantable loop recorder alerts, guiding timely pacemaker therapy and preventing diagnostic delays in patients with unexplained recurrent syncope.
Today

Non-union fractures occur in 2-5% of cases, causing significant disability and cost. Conservative modalities such as LIPUS, PEMF, and focused ESWT offer non-surgical healing options for defects up to 5-10 mm when adequate mechanical stability exists without infection.
Yesterday
The randomized HOBIT-AF trial reveals that while structured weight loss after catheter ablation significantly improves cardiometabolic health in obese patients with paroxysmal atrial fibrillation, it does not reduce arrhythmia recurrence compared to standard care.
Today
