

Loading, please wait...
Loading, please wait...

Posterior reversible encephalopathy syndrome represents an acute neurovascular condition characterized by vasogenic brain edema. Clinicians frequently encounter severe headaches, encephalopathy, visual deficits, and acute seizures during clinical presentation. Although medical management often reverses the clinical deficits, secondary intracranial hemorrhage develops in a significant subset of individuals. Recent investigative work demonstrates that occipital cerebral microbleeds serve as an essential neuroimaging biomarker for hemorrhagic complications. Investigators retrospectively analyzed 165 confirmed cases of posterior reversible encephalopathy syndrome to explore vascular disruption patterns. Among these patients, 19 individuals experienced intracranial bleeding during their acute hospital presentation. Susceptibility-weighted sequences readily identify these microscopic hemorrhagic foci across vulnerable territories. Consequently, physicians must recognize that microbleed deposition indicates advanced endothelial breakdown rather than benign fluid extravasation. Furthermore, early detection enables timely risk stratification in intensive care units and emergency departments. When radiologic evaluations identify these focal signal voids, physicians should suspect impending macro-hemorrhages. Therefore, clinicians must prioritize prompt imaging reviews whenever patients exhibit severe neurological decline. In addition, recognizing these microscopic lesions changes how teams counsel families regarding neurological recovery trajectories. Ultimately, early neuroimaging provides crucial insight into structural vascular integrity during acute presentations.
The pathophysiology of reversible encephalopathy involves severe cerebral autoregulatory failure. Sudden elevations in systemic perfusion pressure easily overcome myogenic vascular responses in posterior circulation vessels. Specifically, the vertebrobasilar territory possesses sparse sympathetic perivascular innervation compared to anterior vessels. As a result, excessive hydrostatic pressure forces fluid across damaged capillaries into adjacent white matter tracts. This disruption exposes fragile microvessels to shear stress and subsequent petechial bleeding. Moreover, researchers observed marked anatomical variation in microbleed distribution across study cohorts. Patients presenting with frank intracranial hemorrhage displayed a significantly higher prevalence of parietal and occipital microbleeds. Specifically, occipital microbleeds appeared in 47.1% of bleeding patients compared to only 11.8% of non-bleeding patients. Similarly, parietal microbleeds occurred in 52.9% of hemorrhagic cases versus 21.3% of non-hemorrhagic cases. Consequently, focal regional damage indicates profound local capillary failure rather than generalized encephalopathy alone. Furthermore, endothelial cell activation causes secondary microthrombosis and localized ischemia within posterior cortical structures. This reperfusion injury exacerbates cellular leakage when cerebral blood flow normalizes. In addition, inflammatory cascades trigger matrix metalloproteinase release, degrading fragile basement membranes. Ultimately, these structural changes compromise vessel integrity and precipitate catastrophic cerebral bleeding.
Precise diagnostic imaging remains crucial for detecting occult microvascular hemorrhage in encephalopathic patients. Standard computed tomography scans quickly detect large hematomas but lack adequate sensitivity for punctate microhemorrhages. In contrast, magnetic resonance sequences offer exceptional sensitivity for identifying paramagnetic blood degradation products. Gradient-recalled echo sequences provide reliable visualization of acute and subacute microscopic petechial hemorrhages. However, susceptibility-weighted imaging demonstrates far superior sensitivity for smaller parenchymal hemorrhagic foci. Susceptibility sequences exploit magnetic field inhomogeneities caused by local hemosiderin deposition. As a result, radiologists detect blooming artifacts that conventional T2-weighted or fluid-attenuated sequences completely miss. In the landmark clinical cohort, imaging teams categorized microbleeds and hematomas using an objective five-millimeter threshold. They comprehensively examined nine distinct brain areas, separating lobar regions from deep subcortical structures. Notably, deep cerebral structures did not exhibit the same hemorrhagic vulnerability as posterior cortices. Therefore, specialized susceptibility sequences should form the standard diagnostic protocol for suspected posterior encephalopathy. In addition, timely detection prevents diagnostic delays and differentiates encephalopathy from acute ischemic stroke. Radiologists should systematically evaluate the occipital lobes for subtle punctate hypointensities. Ultimately, adopting advanced imaging protocols protects vulnerable patients from undetected hemorrhagic progression.
Medical dogma historically linked intracranial hemorrhage risk directly to extreme elevations in blood pressure. However, recent clinical findings challenge this simplistic assumption in posterior encephalopathy cohorts. Specifically, researchers discovered no significant blood pressure difference between patients who suffered hemorrhages and those who avoided them. The maximal systolic blood pressure reached 180.0 mmHg in hemorrhagic cases versus 183.5 mmHg in non-hemorrhagic individuals. Consequently, pure hemodynamic force alone does not dictate vessel rupture during acute encephalopathic episodes. Instead, intrinsic microvascular susceptibility and preexisting endothelial damage play substantial determining roles. Furthermore, systemic inflammatory states, toxic exposures, and autoimmune conditions accelerate endothelial breakdown independently of systemic pressure spikes. Immunosuppressive therapies and chemotherapeutic agents directly injure cerebral capillary tight junctions. As a result, even moderate arterial hypertension triggers capillary rupture when vascular endothelial health degrades. Similarly, renal failure and eclampsia disrupt biochemical defense mechanisms protecting brain microvessels. Clinicians must therefore avoid assuming that stable blood pressure numbers ensure vascular safety. In addition, practitioners must assess underlying metabolic disturbances and inflammatory burdens in high-risk patients. Because endothelial fragility drives hemorrhagic conversion, therapy must address systemic vascular stress. Ultimately, managing end-organ damage requires an integrated perspective beyond simplistic blood pressure targets.
The occurrence of intracranial hemorrhage dramatically alters clinical outcomes in reversible encephalopathy syndrome. Although many patients achieve full neurological recovery, hemorrhagic transformation substantially reduces complete remission rates. Statistical mediation analysis confirms that intracranial hemorrhage mediates the adverse association between microbleeds and poor clinical outcomes. Specifically, microbleeds signify extensive structural damage that directly predisposes vessels to macro-hemorrhage. Consequently, patients displaying microbleeds experience prolonged intensive care admissions and higher long-term disability rates. Therefore, medical teams must exercise extreme caution when considering antithrombotic or anticoagulant therapies. If a patient displays occipital microbleeds, physicians should reevaluate the necessity of prophylactic anticoagulation. Furthermore, clinicians must manage blood pressure smoothly to prevent acute perfusion fluctuations. Rapid overcorrection may induce cerebral ischemia, whereas severe rebound surges trigger catastrophic hematoma expansion. In addition, prompt withdrawal of offending immunosuppressive drugs promotes endothelial barrier recovery. Multidisciplinary collaboration between neurologists, intensivists, and radiologists ensures coordinated acute care. Clinicians should also schedule serial neuroimaging to monitor edema resolution and stability of hemorrhagic foci. Moreover, aggressive seizure control prevents sudden hemodynamic swings and secondary neuronal injury. Ultimately, recognizing microbleed distribution guides informed clinical decision-making and protects patients from preventable complications.
Intracranial hemorrhage complicates approximately fifteen percent of posterior encephalopathy cases. Clinical cohorts report rates ranging between ten and twenty percent across various hospital settings. Although medical treatment often resolves cerebral edema, secondary bleeding significantly worsens patient morbidity. Therefore, clinicians must promptly detect hemorrhage to tailor critical care management and prevent poor outcomes.
Occipital cerebral microbleeds reflect severe local capillary breakdown within vulnerable posterior vascular beds. Because posterior vessels possess sparse sympathetic autoregulatory control, hypertensive surges easily disrupt blood-brain barrier architecture. Consequently, petechial microbleeds signal extensive microvascular damage that readily escalates into overt hematomas. Thus, identifying occipital lesions alerts clinicians to advanced regional vascular fragility.
Surprisingly, peak systolic blood pressure does not differentiate patients with intracranial hemorrhage from those without bleeding. Clinical studies demonstrate nearly identical blood pressure elevations across both patient cohorts at symptom onset. Consequently, systemic pressure spikes alone do not trigger hemorrhage; rather, localized endothelial vulnerability and microvascular integrity dictate whether macroscopic bleeding occurs.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A study in the Journal of the Neurological Sciences reveals that occipital cerebral microbleeds strongly predict intracranial hemorrhage in posterior reversible encephalopathy syndrome (PRES), independent of peak blood pressure, serving as a critical biomarker for disease outcomes.
Today
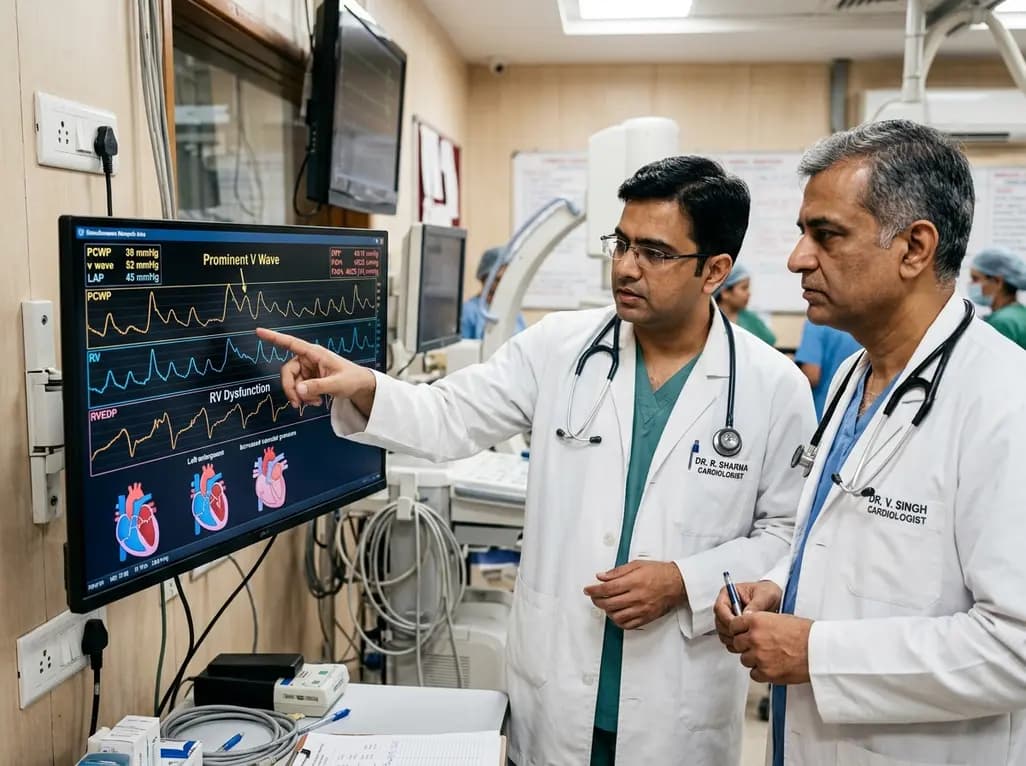
Left atrial stiffening generates prominent V waves that pressurize the pulmonary circulation and augment right ventricular afterload independently of intrinsic pulmonary vascular disease in patients with heart failure with preserved ejection fraction.
Today

A meta-analysis demonstrates that secondhand smoke exposure significantly elevates fetal loss risk by 21% among nonsmoking pregnant women. Clinicians must implement household screening and family-centered cessation interventions to prevent avoidable miscarriages and stillbirths.
Today

Preclinical validation demonstrates that a novel contact force-integrated pulsed field quantization index accurately predicts lesion depth in real time, achieving 100% durable pulmonary vein isolation without collateral injury.
Today
A new cross-sectional evaluation reveals how regional lean mass and bone mineral content interact in resistance-trained men, showing that whole-body size and allometric scaling explain shared musculoskeletal phenotypes and strength relationships.
Today

Explore the emerging role of glucose metabolic reprogramming in exercise-attenuated osteoporosis, examining how physical activity influences osteoblast glycolysis, osteoclast bioenergetics, and skeletal remodeling pathways to improve bone mineral density.
Today
