

Loading, please wait...
Loading, please wait...
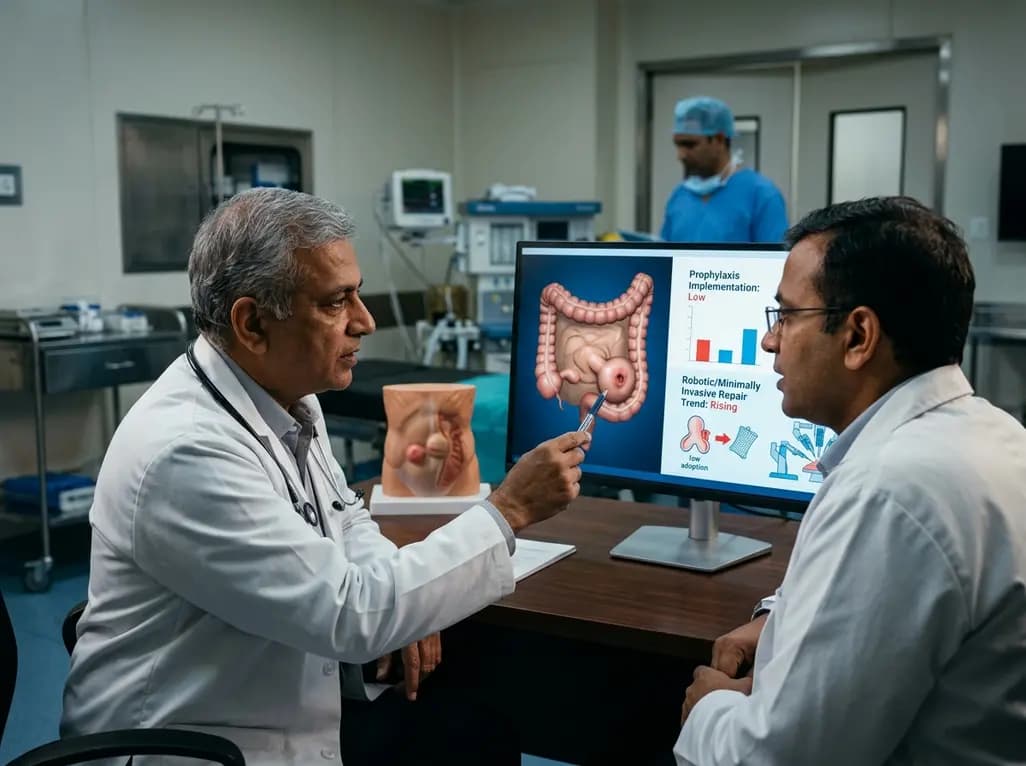
Parastomal hernia remains one of the most frustrating complications following stoma formation, often compromising patient quality of life and imposing significant healthcare costs. Despite clear evidence supporting preventive interventions, substantial controversy surrounds both prevention and parastomal hernia repair across surgical specialties. A landmark cross-sectional survey conducted across Denmark, Finland, Norway, and Sweden offers critical insights into contemporary surgical practices, clinical attitudes, and institutional policies. By examining these regional patterns, clinicians worldwide can better understand existing clinical dilemmas and optimize patient care pathways.
Although international guidelines strongly recommend prophylactic mesh placement during permanent end colostomy creation, widespread clinical adoption remains elusive. The Nordic survey revealed that among surgeons performing permanent end colostomies, only 28% routinely employ prophylactic mesh. Furthermore, 53% of surveyed surgeons admitted they have never placed a prophylactic mesh, whereas 19% previously used the technique but subsequently abandoned it. Consequently, this data reveals a profound implementation gap between evidence-based recommendations and daily surgical reality. Geographical variations further emphasize this disparity. For instance, an astonishing 81% of Finnish surgeons routinely utilize prophylactic mesh, whereas Danish surgeons reported zero percent adoption. This stark contrast highlights that regional medical dogma and surgical tradition often outweigh published clinical guidelines. Among those clinicians who actively insert prophylactic mesh, 54% favor the intraperitoneal funnel or chimney technique. Nevertheless, widespread hesitation persists among most general and colorectal surgeons. Clinicians frequently question whether the prophylactic benefit justifies the added complexity during index ostomy surgery.
Understanding the root causes of surgical hesitation is vital for closing the clinical divide. In the survey, 42% of respondents cited their firm belief in acceptable non-mesh outcomes as the primary reason for avoiding prophylaxis. Additionally, 40% of surgeons expressed persistent fears regarding mesh-related complications, including deep surgical site infection, chronic pain, and bowel erosion. Therefore, subjective risk perception continues to steer operative choices more than randomized trial findings. Interestingly, cultural philosophy heavily dictates surgical disposition. While Swedish surgeons demonstrated enthusiasm for expanding elective repair access, Danish colleagues voiced significant restraint. Specifically, 65% of Swedish surgeons argued that hospitals should offer elective repair to more patients. In sharp contrast, 42% of Danish practitioners favored performing fewer elective repairs. Danish clinicians typically rely on conservative non-operative measures, such as specialized support garments, unless severe symptoms develop. However, conservative pathways carry measurable trade-offs. Emergency hernia interventions carry alarming mortality rates reaching up to 29%. Thus, withholding elective intervention can expose elderly or comorbid individuals to catastrophic acute incarceration risks.
When non-operative management fails, selecting an effective operative strategy becomes paramount. Historically, open suture repair yielded unacceptably high recurrence rates, which prompted the adoption of prosthetic reinforcement. Currently, laparoscopic Sugarbaker repair represents both the most frequently performed procedure at 41% and the preferred method at 34% among Nordic surgeons. This technique lateralizes the bowel conduit and secures a prosthetic sheet intraperitoneally, effectively reducing recurrence. Concurrently, retromuscular techniques have gained remarkable momentum across abdominal wall reconstruction circles. Robotic parastomal hernia repair using the Pauli approach has emerged as the second most preferred modality, chosen by 20% of respondents. During the Pauli procedure, surgeons perform transversus abdominis release, dissect the retromuscular space, and lateralize the stoma conduit retro-peritoneally. Consequently, this strategy keeps the synthetic mesh outside the peritoneal cavity, decreasing long-term adhesion formation and bowel erosion risks. Specialist surgeons increasingly favor this meticulous anatomical reconstruction for complex or recurrent cases.
A striking finding from the investigation is the pronounced gap between surgical preferences and actual clinical practice. Although half of all participating surgeons still perform open repairs, only 20% genuinely prefer this open approach. This discrepancy highlights substantial logistical and infrastructural barriers within modern healthcare systems. Robotic systems offer enhanced visualization, articulating instruments, and superior ergonomics for delicate retroperitoneal dissection. Accordingly, 39% of hernia and abdominal wall reconstruction specialists prefer robotic-assisted parastomal hernia repair. However, only 17% of active repair surgeons currently perform robotic procedures. Limited robotic console availability, steep learning curves, and operating room scheduling constraints frequently force surgeons into performing conventional open surgery. Furthermore, junior trainees often lack structured training in advanced abdominal wall reconstruction. Therefore, institutional investment in advanced surgical platforms and specialized training modules remains imperative. Closing this technology-utilization divide will enable more patients to benefit from reduced wound morbidity, shorter hospital stays, and lower postoperative pain scores.
The striking divergence in surgical outcomes and strategies reinforces the urgent necessity for standardized, centralized clinical pathways. Denmark has demonstrated significant success through specialized tertiary centers that manage complex abdominal wall reconstruction. Centralization pools surgical volume, accelerates technical proficiency, and standardizes perioperative criteria for high-risk patients. Because emergency parastomal hernia operations entail up to 29% mortality, timely multidisciplinary evaluation in dedicated units can save lives. These findings carry profound clinical relevance for surgical communities across India and other emerging economies. In Indian surgical centers, colorectal procedures and stoma creations occur frequently across diverse resource settings. However, fear of mesh contamination and variable access to robotic systems mirror the Nordic experience. Implementing routine, evidence-based stoma prophylaxis could significantly decrease the national hernia burden. Concurrently, establishing dedicated abdominal wall units in tertiary Indian hospitals will streamline complex repairs, reduce emergency admissions, and improve long-term survivorship. Collaborative regional registries should monitor outcomes to guide future clinical policies.
Prophylactic mesh remains underutilized primarily because of pervasive surgical culture and entrenched risk perception. In clinical surveys, over 40% of surgeons report fears of devastating mesh infections, bowel erosion, and fistulization. Additionally, many practitioners erroneously believe that non-mesh stoma construction yields acceptable long-term outcomes. Consequently, surgeons often prioritize perceived immediate technical ease over preventive efficacy, demonstrating an urgent need for clearer regional implementation protocols.
The robotic Pauli technique provides superior anatomical reconstruction by placing the prosthetic mesh entirely in the retromuscular space. By combining transversus abdominis release with bowel lateralization, the surgeon avoids direct mesh contact with intra-abdominal viscera. Furthermore, the robotic platform enhances dexterity during complex adhesiolysis and deep retroperitoneal suturing. This approach effectively minimizes visceral adhesions, reduces wound morbidity, and provides durable defect closure with promising low recurrence rates.
Centralized referral pathways dramatically improve clinical outcomes by directing complex patients to specialized hernia surgeons. Because emergency operations for strangulated parastomal hernias carry mortality rates up to 29%, early elective risk assessment is crucial. Centralized centers facilitate standardized selection, multidisciplinary prehabilitation, and access to advanced robotic platforms. Furthermore, regional registries derived from centralized care allow continuous auditing, which reduces long-term recurrence rates and minimizes catastrophic perioperative complications.
Disclaimer: This content is for informational and educational purposes only, and does not constitute medical, surgical, or clinical advice. Surgical decision-making should be individualized based on clinical presentation and risk assessment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A comprehensive Nordic survey reveals a major implementation gap in parastomal hernia prophylaxis alongside a shift toward robotic parastomal hernia repair. While prophylactic mesh adoption remains low, advanced minimally invasive techniques and centralized referral systems offer promising pathways to cut mortality.
last month

Psoriasis is a chronic systemic inflammatory condition requiring comprehensive clinical intervention beyond topical care. Explore evidence-based insights into systemic comorbidities, patient quality of life, and targeted biologic options such as IL-23 inhibitors for sustained disease control.
Today

A nationwide cohort study published in JAMA Pediatrics reveals that maternal exposure to wildfire fine particulate matter, especially in late pregnancy, is linked to an elevated risk of childhood autism. Clinicians should evaluate ambient air quality risks and provide proactive protective counseling to mothers.
Today

Annual health checks only offer static snapshots. Real-world evidence from 2.1 million insured Indians reveals that tracking dynamic biomarker trends over time enables clinicians to spot evolving cardiometabolic risks early, reverse borderline pathology, and deliver tailored preventive interventions.
Today
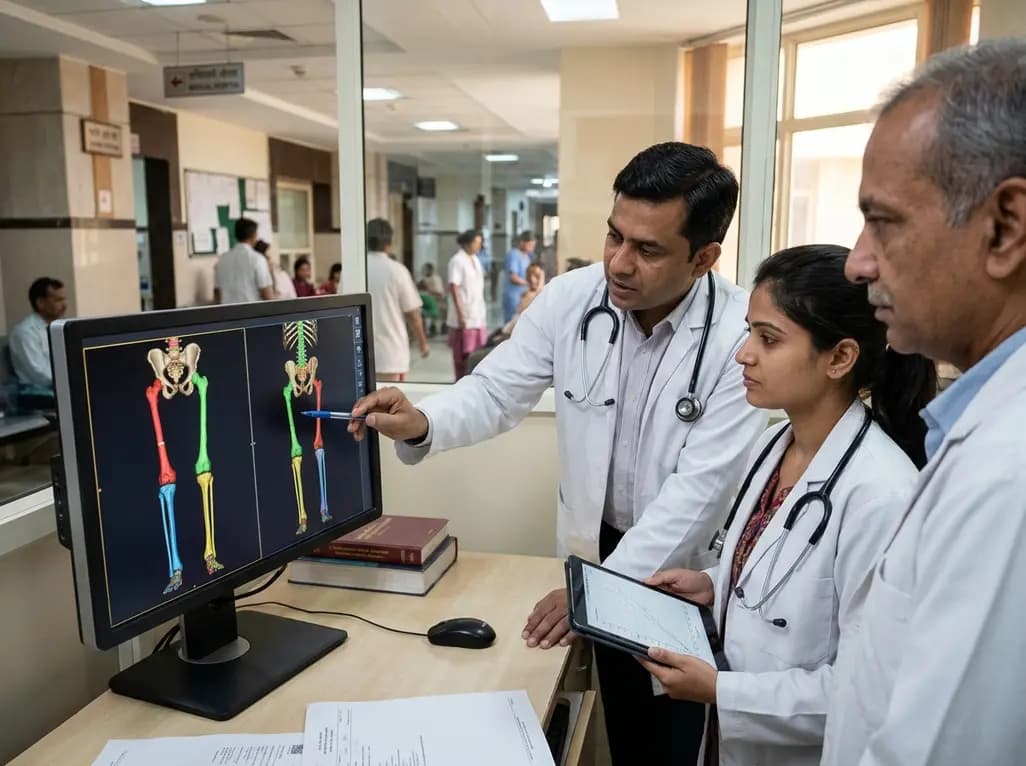
Modern 3D anthropometry reveals that pediatric leg growth ceases years before spinal elongation, exposing the clinical illusion of the classical Anderson-Green model. Learn how segmental growth dissociation improves surgical timing for epiphysiodesis in adolescent leg length discrepancy.
2 days back

With packaged goods giant HUL backing FSSAI's proposed front-of-pack red warning labels for foods high in fat, sugar, and salt, India takes a major step toward curbing non-communicable diseases. Learn how clearer nutrition disclosures empower clinicians, inform consumer choices, and drive dietary reform.
Today
