

Loading, please wait...
Loading, please wait...

Acute secondary deterioration represents one of the most devastating complications encountered during acute neurotrauma management. In routine neurocritical practice, neuroworsening in TBI affects more than one in five admitted patients. Historically, clinical definitions of this dangerous entity have remained highly heterogeneous and inconsistent across emergency centers. Furthermore, traditional diagnostic frameworks have maintained an inherently reactive posture toward evolving cerebral pathology. Clinicians frequently recognize deterioration only when severe intracranial hypertension triggers terminal brainstem herniation or fixed pupillary dilatation. Because delayed recognition leads to profound secondary ischemic damage, neurotrauma clinicians urgently require a standardized diagnostic approach. Modern neurotrauma protocols must integrate contemporary neuromonitoring variables alongside serial clinical examinations. Timely physiological detection permits prompt medical or surgical intervention before irreversible cellular necrosis develops. In response to this longstanding dilemma, international consensus groups have established standardized criteria to guide acute care. By focusing on timely identification, intensivists and neurosurgeons can fundamentally transform patient survival and functional recovery. Moreover, moving away from fragmented definitions enables trauma resuscitation teams to establish uniform intervention thresholds. Ultimately, precision neurotrauma care demands abandoning passive observation in favor of continuous, proactive physiological surveillance.
To eliminate diagnostic ambiguity, two major neurosurgical and neurocritical organizations established an international collaborative initiative. The Latin American Brain Injury Consortium (LABIC) partnered with the Latin American Federation of Neurosurgical Societies (FLANC) to address this unmet need. Together, they convened twenty-five leading neurotrauma specialists to conduct a formal, multi-stage Delphi consensus process. Prior to the formal deliberation, the steering committee executed an exhaustive systematic literature review covering five decades of published evidence. Subsequently, investigators administered structured electronic questionnaires featuring validated Likert scales and detailed multiple-choice items. The expert panel established a rigorous predefined consensus threshold requiring at least eighty percent agreement for every statement. Remarkably, the first Delphi survey round achieved an impressive ninety-five percent response rate among invited panelists. Even more notably, one hundred percent of the drafted consensus statements satisfied the required consensus threshold during this single round. This exceptional concordance demonstrates clear alignment regarding the clinical parameters of secondary deterioration. As a result, the initiative formulated seven definitive consensus statements to guide neurointensive practice. Consequently, the resulting guidelines provide high methodological reliability for emergency departments and intensive care units worldwide.
Central to this modern framework is a stratified three-tier diagnostic classification system. Rather than characterizing neurological decline as a binary event, the consensus defines three clinically distinct phenotypes. The first category comprises Established Neuroworsening, which represents overt neurological decline. During this phase, bedside examination reveals significant motor score drops or emerging pupillary abnormalities. However, awaiting these overt clinical signs exposes vulnerable brain parenchyma to prolonged, uncorrected ischemia. Therefore, the panel introduced the Subclinical Neuroworsening phenotype to capture early physiological failure. This category encompasses pathophysiological or imaging decompensation that occurs prior to detectable bedside clinical deterioration. Specifically, intracranial pressure spikes, expanding contusions on repeat computed tomography, or microvascular tissue hypoxia define this state. Finally, the framework introduces the High-Risk Phenotype. This tier encompasses patients possessing pre-existing systemic vulnerabilities, restricted intracranial compliance, or extensive structural contusions. Consequently, recognizing high-risk features alerts clinicians to intensify neurointensive monitoring before cerebral perfusion fails. In addition, this tripartite model aligns directly with the tenets of precision neurotrauma medicine. Thus, stratified phenotyping enables proactive clinical decision-making across emergency and intensive care settings.
A primary shortcoming of earlier diagnostic definitions was their exclusive dependence on clinical neurological exams. Although the Glasgow Coma Scale remains an indispensable bedside tool, sedation and paralysis frequently obscure clinical assessments. Consequently, the LABIC-FLANC consensus emphasizes integrating multimodal neuromonitoring into routine neurointensive care protocols. Continuous intracranial pressure monitoring provides immediate alerts when intracranial compliance reserve begins to fail. Furthermore, brain tissue oxygen tension sensors detect occult tissue hypoxia long before systemic vital signs deteriorate. Clinicians can also utilize bedside transcranial Doppler ultrasonography to quantify cerebral blood flow velocities and resistance indices. Similarly, automated quantitative pupillometry eliminates human subjectivity by providing precise, reproducible measurements of pupillary constriction velocities. In centers with limited invasive technology, serial non-invasive imaging and optic nerve sheath ultrasonography offer valuable diagnostic alternatives. By synthesizing these diverse physiological inputs, neurocritical teams can detect subclinical deterioration during the earliest window of opportunity. Therefore, multimodal data integration converts intermittent bedside assessments into continuous physiological intelligence. As neurointensive management advances, these technological tools will safeguard patients against unrecognized ischemic progression.
For more than half a century, neurotrauma practice has operated within a reactive management model. Physicians typically instituted salvage measures only after herniation syndromes produced irreversible neurological deficits. In contrast, the newly established consensus promotes an evidence-based paradigm of proactive, personalized neuroprotection. When clinical teams identify patients presenting with the high-risk phenotype, they can immediately optimize cerebral perfusion pressure. They can also promptly correct secondary systemic derangements such as hypotension and hypoxemia. Similarly, detecting subclinical deterioration enables prompt diagnostic imaging and early therapeutic titration before cerebral tissue suffers irreversible infarction. Furthermore, this precision framework holds profound clinical relevance for emergency and trauma systems across India. In high-volume public hospitals, standardized phenotyping assists clinicians in triaging scarce intensive care beds and surgical resources effectively. Standardizing the clinical terminology of deterioration also accelerates multi-center collaborative research and translational neurotrauma trials. Most importantly, adopting this preventive methodology protects salvageable penumbral brain tissue from cumulative secondary insults. Consequently, as multidisciplinary teams implement these recommendations into routine workflows, clinical outcomes and long-term functional recovery will noticeably improve.
Neuroworsening in traumatic brain injury describes acute clinical, radiological, or physiological deterioration occurring after head trauma. It indicates disease progression caused by expanding intracranial lesions, elevated pressure, or secondary systemic insults. Modern definitions classify this deterioration into established, subclinical, and high-risk phenotypes to guide prompt interventions.
Established neuroworsening presents with overt clinical manifestations, such as motor score drops or pupillary abnormalities. In contrast, subclinical neuroworsening reflects physiological or radiological decompensation without visible bedside examination changes. It is identified through multimodal monitoring, intracranial pressure elevations, progressive microvascular hypoxia, or early lesion growth on neuroimaging.
The high-risk phenotype identifies vulnerable patients possessing pre-existing systemic insults or severely exhausted intracranial compliance reserves. Recognizing this state enables intensivists to initiate preemptive surveillance, optimize cerebral perfusion pressure, and correct physiological derangements. Consequently, clinicians prevent irreversible brainstem compression before overt clinical or subclinical neurological deterioration occurs.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References
Godoy DA et al. Neuroworsening in traumatic brain injury: A consensus of the Latin American Brain Injury Consortium (LABIC) and the Latin American Federation of Neurosurgical Societies (FLANC) expert group. Neurosurg Rev. 2026 May 07. doi: 10.1007/s10143-026-04284-z. PMID: 42095959.
Godoy DA, de Amorim RLO, Paranhos JL, et al. Neuroworsening in Traumatic Brain Injury: A Scoping Review of Definition, Prevalence, and Outcome. Neurocrit Care. 2025;40(2):415-426. doi: 10.1007/s12028-025-02234-z.
Picetti E, Galarza L, Arroyo Diez M, et al. Staircase strategy, tier-three therapies, and effects on outcome in traumatic brain injured patients: the Triple-T TBI study. Intensive Care Med. 2023;49(12):1478-1488. doi: 10.1007/s00134-023-07234-x.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





An expert consensus from LABIC and FLANC establishes an updated framework for neuroworsening in traumatic brain injury (TBI). By stratifying deterioration into established, subclinical, and high-risk phenotypes, the consensus shifts neurotrauma practice from reactive rescue to early precision-guided prevention.
Today
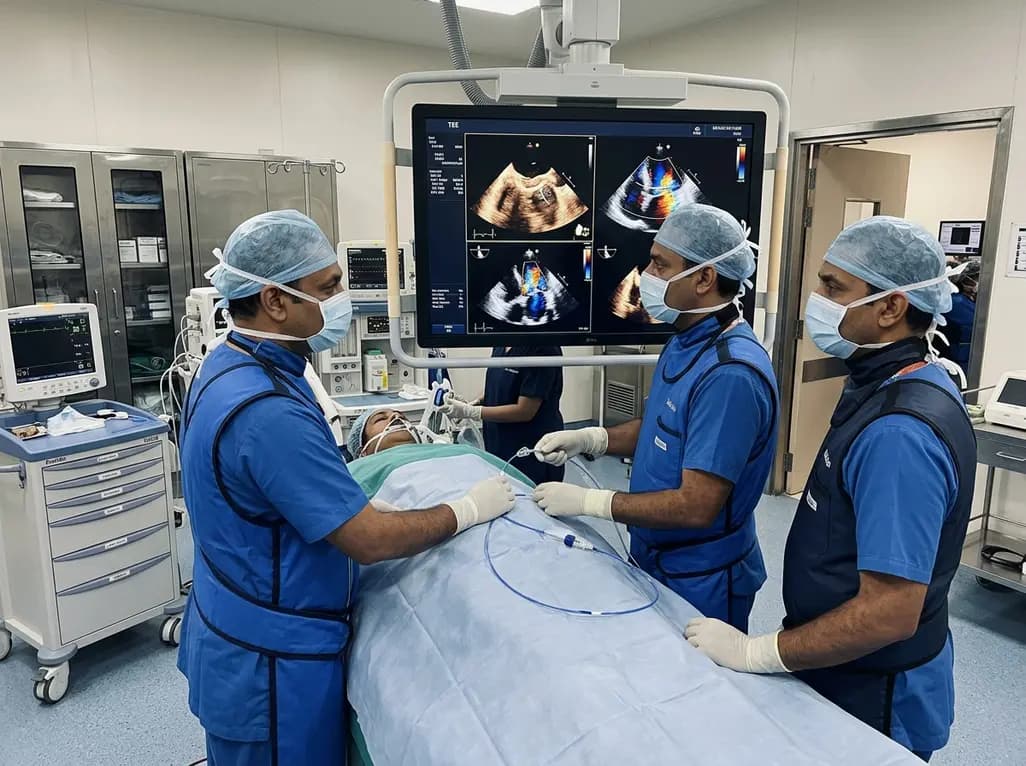
Transcatheter edge-to-edge repair (TEER) successfully treated severe mitral regurgitation from a posterior leaflet perforation. Guided by 3D multiplanar reconstruction, operators sandwiched the defect using two MitraClip devices, providing safe hemodynamic recovery without requiring open-heart surgery.
Today
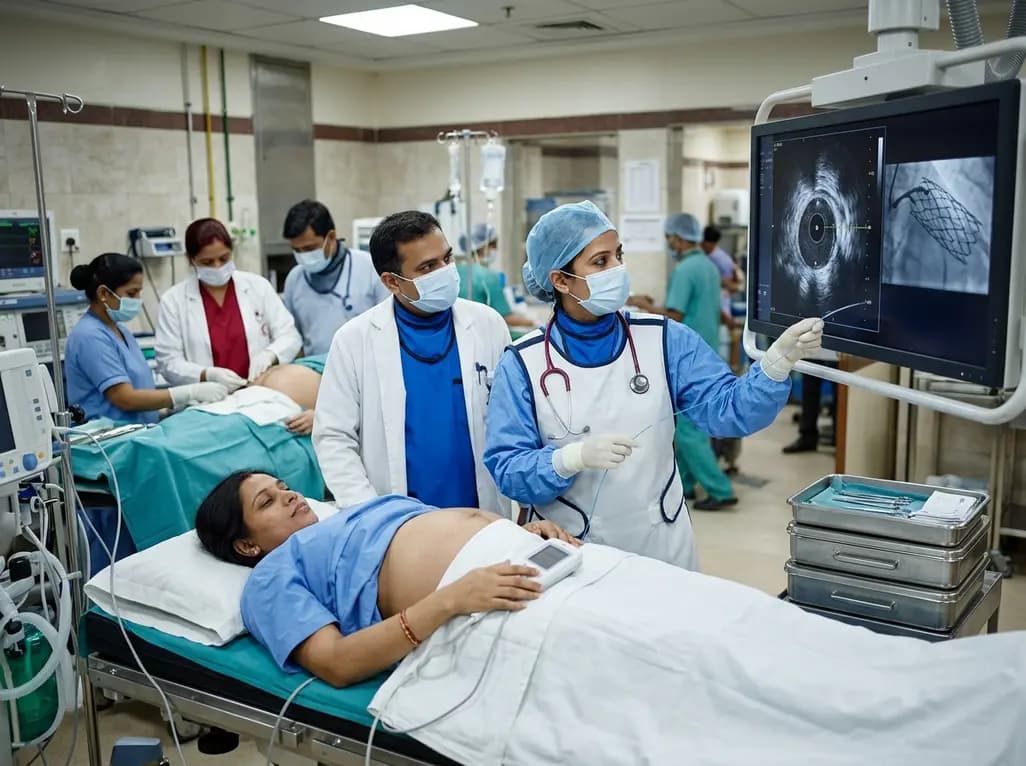
A 32-year-old gravida at 38 weeks with anterior STEMI underwent emergent IVUS-guided PCI and successful cesarean delivery under uninterrupted DAPT, highlighting cardio-obstetric care.
Today

A systematic review and meta-analysis of 5,406 participants reveals that tirzepatide significantly reduces hsCRP by 34.3%, improves cardiorenal biomarkers, and enhances functional capacity and exercise endurance in patients with heart failure.
Today

A landmark biomechanical study demonstrates that sports bra support and running shoe cushioning interact significantly to influence tibial acceleration, breast motion, and comfort in female runners, providing crucial insights for clinical counseling in sports medicine and women's health.
Yesterday
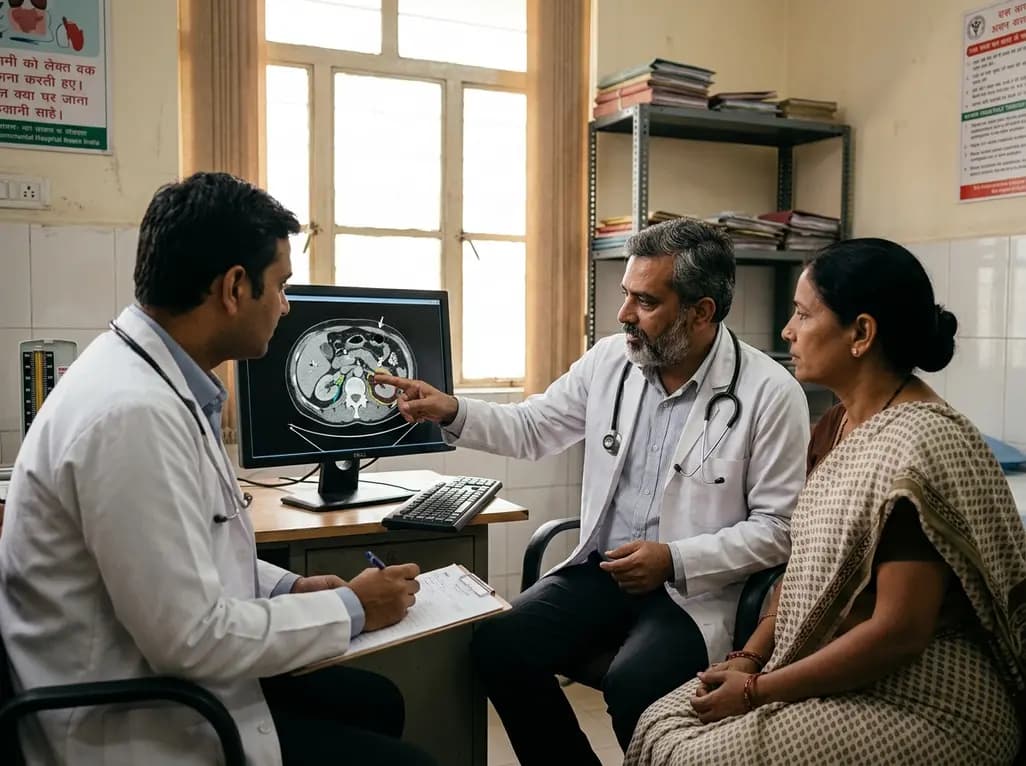
New ADIPO-CKD study findings demonstrate that both GLP-1 receptor agonists and SGLT2 inhibitors significantly reduce perirenal adipose tissue thickness in chronic kidney disease patients, with GLP-1 therapy achieving greater reductions, highlighting a novel mechanism for cardiorenal metabolic protection.
Today
