

Loading, please wait...
Loading, please wait...

Rapidly progressive cognitive impairment often defines the classic presentation of sporadic Creutzfeldt-Jakob disease, yet non-cognitive manifestations frequently precede or overshadow early neurological signs. Historically, clinicians have categorized prion disorders predominantly by motor, cerebellar, and cognitive decline. However, behavioral disturbances represent a substantial yet under-recognized component of the initial presentation. Emerging prospective evidence demonstrates that psychiatric features appear early and intensely in sporadic Creutzfeldt-Jakob disease. Consequently, recognizing these behavioral markers allows clinicians to improve diagnostic accuracy, reduce diagnostic delays, and deliver timely palliative support to patients and their families.
Although conventional diagnostic frameworks focus heavily on ataxia, myoclonus, and rapid dementia, neuropsychiatric changes frequently dominate the early clinical phase. In a landmark prospective study conducted at the University of California San Francisco Memory and Aging Center, investigators evaluated serial patients using the Neuropsychiatric Inventory. Remarkably, ninety-seven percent of patients with sporadic Creutzfeldt-Jakob disease exhibited at least one neuropsychiatric symptom at their initial evaluation. Furthermore, half of the cohort demonstrated six or more abnormal behavioral domains concurrently. These data illustrate that behavioral manifestations are ubiquitous rather than exceptional. The most prevalent symptoms identified included appetite and eating disturbances in sixty-eight percent of cases, followed closely by apathy and indifference in sixty-six percent. In addition, nighttime behavioral disruptions and aberrant motor behaviors each affected fifty-three percent of individuals, while fifty-two percent suffered from significant anxiety. Even less frequent features like disinhibition emerged in nearly a fifth of all cases. Therefore, clinicians must appreciate that sporadic Creutzfeldt-Jakob disease routinely presents as an aggressive neuropsychiatric condition rather than an isolated motor disturbance.
To contextualize these findings, researchers compared the behavioral profile of prion disease against five established neurodegenerative disorders. Specifically, the investigation analyzed cohorts with Alzheimer's disease, dementia with Lewy bodies, progressive supranuclear palsy, behavioral variant frontotemporal dementia, and semantic variant primary progressive aphasia. Intriguingly, patients with sporadic Creutzfeldt-Jakob disease exhibited markedly higher frequency-by-severity composite scores for delusions and nighttime behavioral disturbances than patients with dementia with Lewy bodies or frontotemporal dementia. Moreover, patients scored significantly higher for hallucinations and dysphoria compared to individuals with behavioral variant frontotemporal dementia. When compared directly with dementia with Lewy bodies, the prion cohort experienced considerably worse agitation, aberrant motor behavior, and eating disturbances. Similarly, sporadic Creutzfeldt-Jakob disease surpassed Alzheimer's disease across nine of the twelve Neuropsychiatric Inventory domains. Consequently, these findings confirm that the sheer intensity and breadth of neuropsychiatric dysfunction in prion disease rival and frequently outpace conditions where behavioral changes define the primary diagnostic criteria.
Current diagnostic guidelines established by international surveillance networks and health authorities prioritize specific neurological features alongside objective paraclinical biomarkers. These tools include diffusion-weighted magnetic resonance imaging showing cortical ribboning or basal ganglia hyperintensity, real-time quaking-induced conversion assays, and periodic sharp-wave complexes on electroencephalography. Nevertheless, the diagnostic criteria omit behavioral symptoms entirely. Because psychiatric presentations frequently prompt initial referrals to outpatient psychiatry or general medical clinics, patients frequently undergo protracted evaluations for primary mood disorders or late-onset psychoses. Meanwhile, the neurodegenerative pathology progresses relentlessly. Incorporating standardized behavioral markers into diagnostic pathways could alert clinicians earlier in the clinical trajectory. In particular, the rapid emergence of severe delusions, profound sleep disturbances, and abrupt appetite shifts should raise immediate suspicion for an underlying prion encephalopathy. Thus, modernizing clinical criteria to encompass neuropsychiatric features will bridge the gap between initial psychiatric presentation and definitive neurological diagnosis.
Differentiating rapidly progressive dementia from reversible encephalopathies and other neurodegenerative mimics represents a significant clinical challenge. In daily practice, clinicians frequently misdiagnose early sporadic Creutzfeldt-Jakob disease as severe depression, late-onset schizophrenia, or acute delirium. Furthermore, autoimmune encephalitis, paraneoplastic syndromes, and central nervous system infections can present with remarkably similar neuropsychiatric trajectories. However, while psychiatric symptoms in sporadic Creutzfeldt-Jakob disease lack individual pathognomonic specificity, their rapid evolution provides essential diagnostic clues. Unlike the insidious behavioral progression observed in typical frontotemporal dementia or Alzheimer's disease, prion-induced behavioral changes intensify over mere weeks. In addition, these psychiatric manifestations quickly coalesce with subtle ataxia, myoclonic twitches, and visual distortions. Therefore, physicians must maintain a high index of suspicion whenever severe affective or psychotic symptoms occur alongside rapid cognitive deterioration. Prompt cerebrospinal fluid analysis and specialized neuroimaging remain vital to exclude treatable autoimmune conditions and confirm prion neuropathology.
The aggressive neuropsychiatric profile of sporadic Creutzfeldt-Jakob disease imposes an extraordinary emotional and physical burden on caregivers. Families must navigate sudden personality transformations, unprovoked agitation, and severe sleep disturbances in their loved ones within an extraordinarily compressed timeframe. In contrast to more slowly progressing dementias, where families gradually adapt to functional decline, prion diseases necessitate immediate and intensive crisis management. Accordingly, multidisciplinary clinical care must integrate aggressive symptomatic palliation alongside emotional and social support. Clinicians should exercise extreme caution when prescribing psychotropic medications. Specifically, typical antipsychotics can exacerbate extrapyramidal signs and induce severe parkinsonism, whereas sedating agents may worsen gait instability and aspiration risk. Instead, physicians should implement targeted environmental adjustments, gentle behavioral de-escalation techniques, and judicious low-dose atypical antipsychotics or sleep aids when distress becomes intolerable. Ultimately, early recognition of the behavioral burden ensures that palliative resources, hospice coordination, and compassionate caregiver counseling occur well before terminal stages unfold.
What are the most common neuropsychiatric symptoms observed in sporadic Creutzfeldt-Jakob disease?
Prospective data reveal that appetite and eating disturbances represent the most common manifestation, occurring in sixty-eight percent of patients. Apathy affects sixty-six percent, while nighttime behavioral disturbances, aberrant motor behaviors, and anxiety each occur in over half of affected individuals, demonstrating an extensive and pervasive behavioral burden.
How do psychiatric symptoms in sporadic Creutzfeldt-Jakob disease compare with frontotemporal dementia?
Patients with sporadic Creutzfeldt-Jakob disease experience significantly higher composite scores for delusions, hallucinations, nighttime sleep disruptions, and depressive dysphoria than patients with behavioral variant frontotemporal dementia. This reality demonstrates that prion diseases often exhibit a more intense behavioral footprint than disorders defined by psychiatric criteria.
Why is recognizing early behavioral changes critical in suspected prion diseases?
Recognizing early neuropsychiatric manifestations prevents prolonged diagnostic odysseys and reduces inappropriate psychiatric admissions. Because prion conditions progress rapidly, early diagnostic suspicion allows timely execution of confirmatory testing, avoids futile invasive interventions, facilitates appropriate symptom control, and ensures that comprehensive palliative care begins without delay.
Disclaimer: This content is for informational and educational purposes only and does not constitute medical advice, diagnosis, or treatment. Healthcare professionals should exercise their clinical judgment and verify information with primary sources. Refer to the latest local and national guidelines for clinical practice.
References
Zitser J et al. Neuropsychiatric symptoms in sporadic Creutzfeldt-Jakob disease. Brain. 2026 Jan 08. doi: 10.1093/brain/awaf077. PMID: 40152909.
Hermann P, Appleby B, Brandel JP, et al. Biomarkers and diagnostic guidelines for sporadic Creutzfeldt-Jakob disease. Lancet Neurol. 2021;20(3):235-246.
Geschwind MD. Prion Diseases. Continuum (Minneap Minn). 2015;21(6 Neuroinfectious Disease):1612-1638.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A prospective cohort study reveals that sporadic Creutzfeldt-Jakob disease presents with prominent early neuropsychiatric symptoms, often exceeding other dementias in severity. These findings advocate for updating diagnostic criteria to include behavioral manifestations.
Today

An Australian cohort of 34,449 adults in an unsubsidized tirzepatide digital weight loss service showed that peer-referred patients achieved significantly higher 6-month adherence (48% vs 42%) and greater weight loss (16.16% vs 14.06%) than matched non-referred peers, highlighting social support in obesity care.
Today

A randomized crossover study demonstrates that conventional and robotic laparoscopy require distinct neuropsychological and psychomotor skills. While trainees master conventional laparoscopy faster, robotic proficiency demands individualized, adaptive curricula tailored to specific learner profiles.
Today
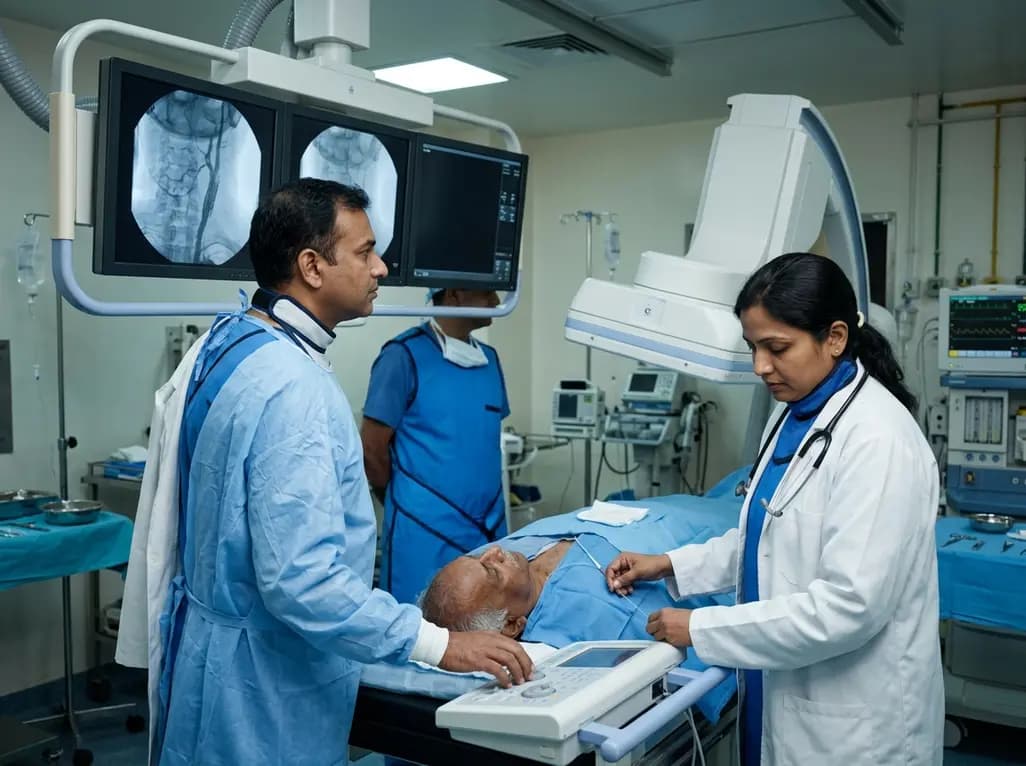
A retrospective study of 109 patients undergoing elective carotid artery stenting evaluated radiation exposure on biplane flat-panel systems. Standardized workflows and dedicated low-dose protocols provide crucial baseline data to establish neurointerventional diagnostic reference levels and optimize patient safety.
Today
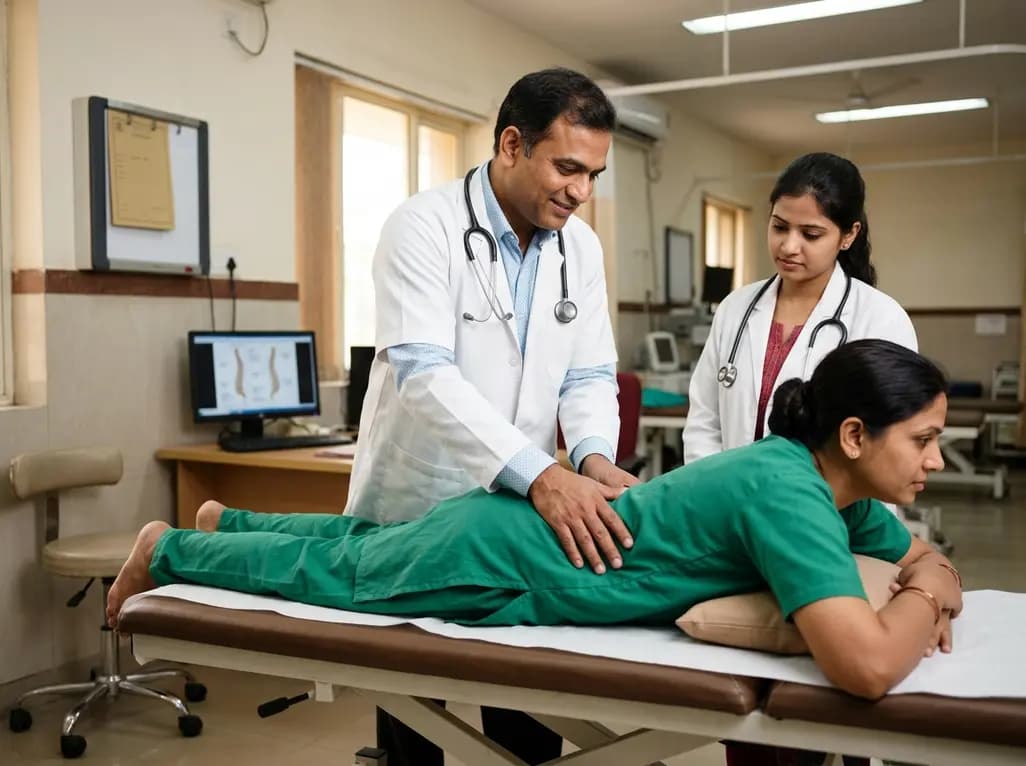
A scoping review of 51 studies reveals that spinal manual therapy on the lumbo-pelvic area is commonly used for isolated lower extremity pain, predominantly knee conditions. While thrust manipulation is frequent, reporting deficits highlight the need for standardized technique descriptions to guide practice.
Today

The Supreme Court has reserved its judgment on FSSAI's proposed front-of-pack nutritional warning labels for packaged foods. With debates over compliance timelines, added versus total sugars, and ultra-processed food definitions, this landmark decision carries profound public health implications for India.
Today
