

Loading, please wait...
Loading, please wait...
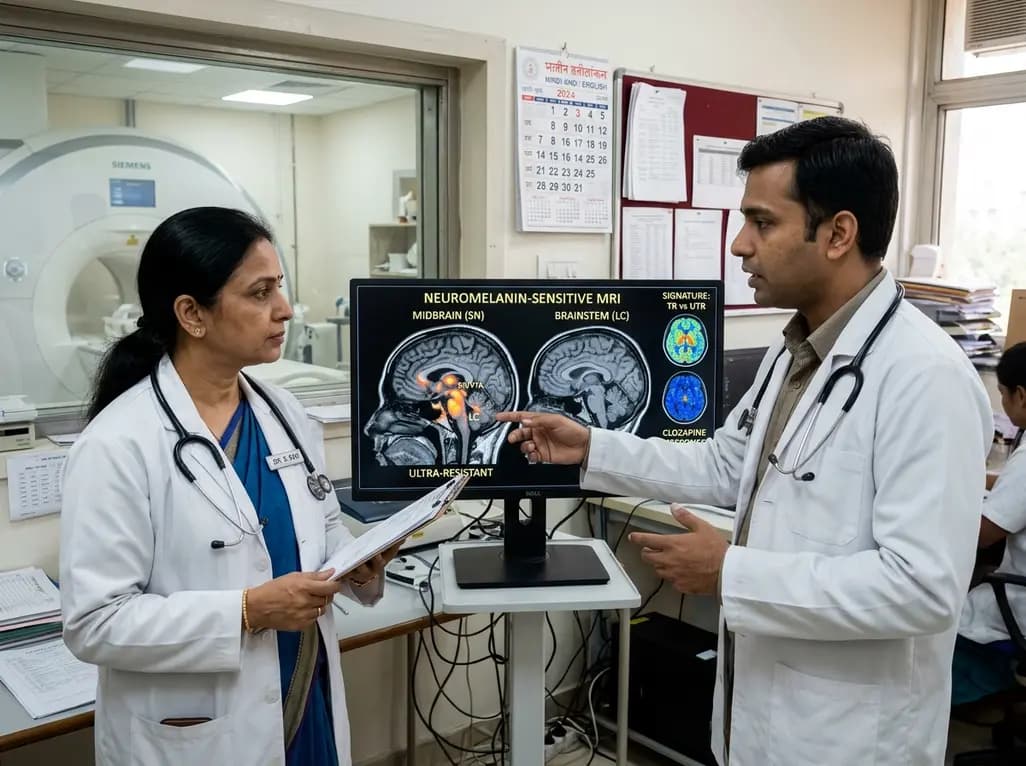
Clinicians frequently encounter marked heterogeneity when managing schizophrenia across various stages of psychiatric care. Although dopaminergic hyperactivity traditionally explains positive psychotic symptoms, conventional therapies fail to produce adequate remission in nearly one-third of individuals. Therefore, identifying noninvasive biomarkers that explain distinct therapeutic trajectories represents a crucial priority. Recent advances demonstrate that neuromelanin MRI in schizophrenia serves as an innovative tool to examine monoaminergic nuclei directly. Neuromelanin forms within catecholaminergic neurons through the oxidative metabolism of cytosolic dopamine and norepinephrine. Consequently, paramagnetic neuromelanin-iron complexes create distinct hyperintense signals on T1-weighted sequences. Because this pigment accumulates steadily over the lifespan, signal contrast provides a durable proxy for long-term monoaminergic activity. In this context, researchers investigate whether monoaminergic signatures differentiate first-line antipsychotic responders from individuals experiencing treatment resistance. Furthermore, clinicians urgently require objective markers to separate clozapine-responsive schizophrenia from ultra-resistant schizophrenia. By evaluating the substantia nigra, ventral tegmental area, and locus coeruleus, novel imaging protocols establish objective biological boundaries. Ultimately, these structural measurements may illuminate why standard neuroleptic regimens succeed in certain presentations while failing completely in others.
To evaluate these neurochemical distinctions, investigators established a rigorous cross-sectional imaging protocol across four well-characterized participant cohorts. Specifically, the study enrolled sixteen individuals with ultra-resistant schizophrenia, sixteen clozapine-responsive patients, twenty first-line responders, and twenty-six healthy control subjects. The research team defined ultra-resistant illness as persistent psychosis despite adequate dosages and durations of clozapine therapy. Meanwhile, first-line responders maintained clinical stability using conventional dopamine D2-receptor antagonist agents. Using high-resolution three-tesla scanners, the team acquired neuromelanin-sensitive scans targeting the midbrain and pontine brainstem. Subsequently, image analysts calculated standardized contrast ratios within the substantia nigra-ventral tegmental area complex and the locus coeruleus. The crus cerebri and central pontine regions served as background reference structures for signal normalization. Additionally, the investigators utilized covariate-adjusted statistical frameworks to control for potential confounding variables, including age and biological sex. Voxel-wise analytical mapping further allowed precise spatial localization of contrast differences within distinct subregions of the midbrain. Thus, this methodology achieved robust anatomical precision without subjecting vulnerable psychiatric patients to radioactive tracers.
The statistical analyses yielded intriguing insights regarding dopaminergic involvement across different treatment responses. Specifically, substantia nigra-ventral tegmental area contrast ratios were significantly elevated in both ultra-resistant patients and first-line responders relative to healthy controls. Moreover, the statistical models demonstrated substantial effect sizes for these elevations in both cohorts. Voxel-wise mapping localized these signal increases predominantly within dorsal subregions of the substantia nigra and ventral tegmental area. In contrast, clozapine-responsive treatment-resistant patients did not exhibit significant midbrain contrast elevations compared to controls. This surprising divergence indicates that first-line responders and ultra-resistant patients share heightened baseline dopaminergic activity. However, standard dopamine blockade easily stabilizes first-line responders, whereas ultra-resistant patients remain profoundly psychotic despite identical receptor antagonism. Furthermore, the absence of dopaminergic elevations in clozapine-responsive individuals suggests an alternative pathophysiological mechanism, such as glutamatergic or neuroinflammatory dysregulation. Therefore, midbrain neuromelanin elevation alone cannot distinguish treatment sensitivity from extreme clozapine resistance. Clinicians must consequently look beyond isolated striatal dopamine paradigms when evaluating severe, refractory schizophrenia.
While dopaminergic alterations linked both ends of the response spectrum, locus coeruleus imaging revealed a distinctive biological pattern. Notably, locus coeruleus contrast ratios were significantly elevated in ultra-resistant schizophrenia compared to first-line responders. Although contrast values in ultra-resistant patients did not differ statistically from healthy controls, the clear elevation above first-line responders indicates meaningful noradrenergic divergence. The locus coeruleus serves as the principal site of noradrenaline synthesis in the central nervous system. Consequently, aberrant noradrenergic projection activity alters prefrontal cortical gating and intensifies hyperarousal, paranoia, and cognitive fragmentation. Furthermore, hyperactive noradrenergic signaling could overcome standard dopamine receptor blockade, creating persistent psychotic symptoms. In contrast, clozapine possesses prominent alpha-adrenergic antagonist properties, which might explain its unique efficacy in refractory patients with intact noradrenergic modulation. However, when noradrenergic signaling becomes severely dysfunctional, even high-dose clozapine regimens fail to restore clinical equilibrium. Thus, locus coeruleus alterations likely represent an additional pathophysiological hit that converts standard treatment resistance into absolute clozapine refractoriness.
Interestingly, the investigators observed no significant correlations between contrast ratio metrics and current psychiatric symptom severity. Similarly, cognitive assessment scores showed no linear associations with monoaminergic signal intensity in either nucleus. Because acute symptom scales fluctuate with environmental stress and recent medication adjustments, they reflect transient clinical states rather than underlying structural biology. In contrast, neuromelanin accumulation represents an integrated, cumulative metric of monoaminergic turnover spanning multiple decades. Therefore, neuromelanin contrast ratios capture enduring trait-level neurobiology rather than transient state-dependent symptom fluctuations. This critical distinction explains why stable first-line responders and severely ill ultra-resistant patients exhibit overlapping substantia nigra contrast elevations. Moreover, these findings imply that treatment resistance in schizophrenia does not merely stem from exaggerated symptom intensity. Instead, resistance emerges from fundamentally distinct neurobiological architectures operating within subcortical monoaminergic networks. Consequently, neuromelanin imaging functions as an objective trait biomarker, identifying immutable neurochemical phenotypes that dictate pharmacotherapeutic receptivity over the patient lifespan.
These neuroimaging insights offer profound implications for contemporary psychiatric practice and precision medicine initiatives. Currently, clinicians must wait through successive failed antipsychotic trials before diagnosing treatment resistance, causing substantial therapeutic delays. Furthermore, diagnosing ultra-resistant schizophrenia requires months of unsuccessful clozapine therapy, exposing patients to severe metabolic and hematologic risks. However, incorporating neuromelanin-sensitive protocols into baseline psychiatric evaluations could accelerate clinical decision-making significantly. For instance, detecting dual midbrain and locus coeruleus signal elevations early in the disease course might identify candidates for augmented intervention strategies. In addition, recognizing clozapine-responsive profiles could prompt earlier initiation of clozapine, minimizing prolonged morbidity. Future longitudinal investigations must determine whether these monoaminergic alterations predate initial psychotic decompensation or develop during active pharmacotherapy. Moreover, multi-center trials should validate standardized scanner sequences to facilitate widespread clinical adoption across diverse hospital settings. Ultimately, objective imaging biomarkers promise to transform trial-and-error psychopharmacology into an individualized, biologically guided discipline.
Neuromelanin contrast ratios quantify the paramagnetic signal generated by neuromelanin-iron complexes inside catecholaminergic neurons. Because neuromelanin accumulates over years of dopamine and norepinephrine metabolism, these signals serve as an established, noninvasive proxy for long-term monoaminergic activity rather than transient, state-dependent neurotransmitter fluctuations.
First-line responders and ultra-resistant patients both display elevated substantia nigra dopaminergic contrast compared to healthy controls. However, ultra-resistant individuals uniquely exhibit significantly elevated locus coeruleus contrast compared to first-line responders, suggesting that concurrent noradrenergic hyperactivity drives extreme refractoriness to conventional antipsychotics and clozapine.
While positron emission tomography remains the gold standard for measuring acute dopamine synthesis capacity, it requires costly radiotracers and radiation exposure. In contrast, neuromelanin MRI provides an accessible, noninvasive structural alternative on standard three-tesla scanners, making widespread clinical staging and repeated assessments feasible for psychiatric patients.
Disclaimer: This content is for informational and educational purposes only and should not be considered professional medical advice. Always seek the guidance of a qualified healthcare provider with any questions regarding medical conditions or treatments. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A novel neuromelanin MRI study reveals distinct monoaminergic signatures across schizophrenia subgroups. While dopaminergic midbrain signals increase in both first-line responders and ultra-resistant patients, locus coeruleus noradrenergic elevations specifically mark clozapine nonresponse.
Today

A large retrospective cohort study demonstrates that explainable machine learning models, notably XGBoost, accurately predict hospital admission at emergency triage. By analyzing routine triage parameters, hospitals can streamline bed allocation, decrease boarding times, and alleviate acute care overcrowding.
Today

A new quality-improvement initiative reveals that universal maternal mental health screening in the NICU increased screening rates from 29.5% to 95.0%, with nearly 60% of screened mothers requiring psychosocial referrals, highlighting the urgent need for embedded mental health resources.
Today

The Department of Pharmaceuticals has extended the medical devices PLI scheme to 2035-36 with a Rs 2,700 crore outlay. Featuring relaxed investment barriers and eliminated sales thresholds, the revised framework targets deep manufacturing, high-end diagnostics, critical MedTech components, and supply resilience.
Today
A metabolomic study reveals that aging delays glutathione synthesis and gamma-glutamylcysteine accumulation following muscle injury. Although precursor supplementation targets this enzymatic bottleneck, in vitro tests show no immediate effect on myogenesis, highlighting the complexity of muscle repair in older adults.
Today

A systematic review evaluates psychological interventions for smoking cessation in diabetes, showing short-term success but highlighting challenges in long-term abstinence.
Today
