

Loading, please wait...
Loading, please wait...
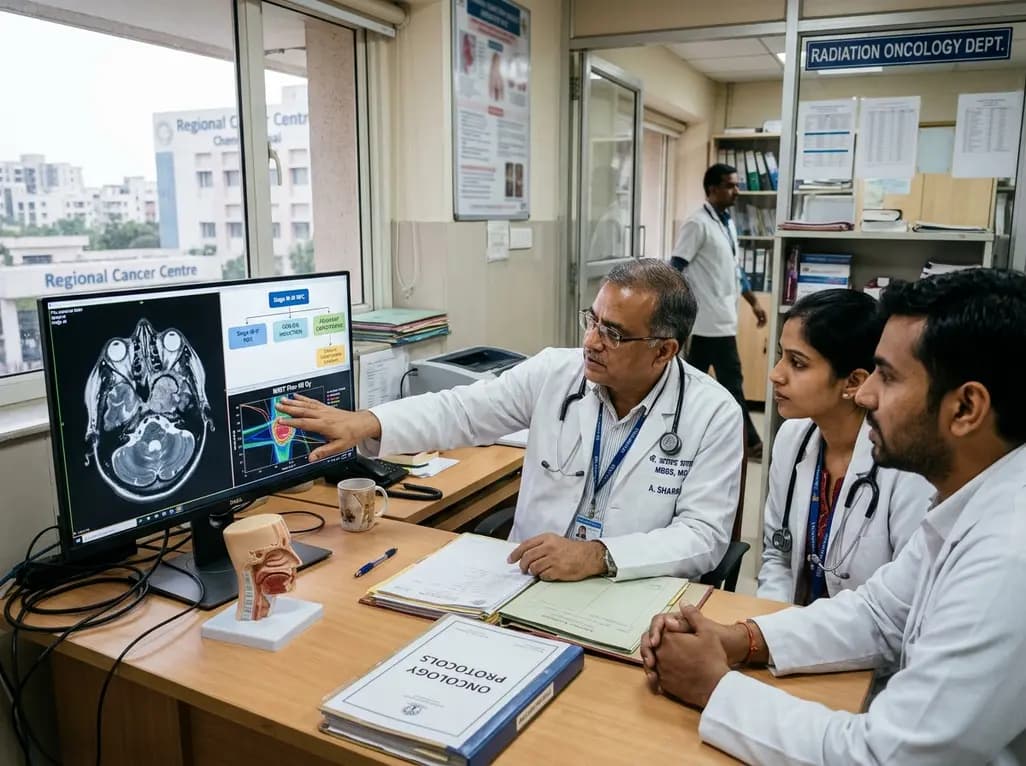
Definitive management of non-metastatic nasopharyngeal cancer requires careful precision and evidence-based multidisciplinary coordination. The updated CSCO-ASCO guideline delivers timely direction for nasopharyngeal carcinoma treatment in patients presenting with stage IB to stage III disease. This comprehensive clinical consensus integrates practice-changing evidence regarding modern radiotherapy planning, risk-adapted systemic sequencing, targeted de-escalation, and novel immunotherapies. Consequently, treating oncologists worldwide can refine clinical protocols to optimize survival and preserve patient quality of life. In addition, these evidence-based updates guide clinicians in tailoring therapies according to individual anatomical and biological risk profiles.
Intensity-modulated radiation therapy represents the undisputed cornerstone for definitive treatment. Modern radiation oncology departments must incorporate daily image guidance and diagnostic magnetic resonance imaging to ensure millimeter-level precision. In addition, high-resolution cross-sectional imaging accurately delineates anatomical boundaries while protecting critical organs at risk. These vulnerable structures include the brainstem, spinal cord, optic chiasm, and salivary glands. Therefore, radiation oncologists can safely maintain full therapeutic prescription doses to gross tumor volumes. Furthermore, international planning guidelines emphasize rigorous peer review and standardized contouring atlases across multidisciplinary teams. Consequently, treated patients achieve locoregional control rates exceeding ninety percent while experiencing fewer debilitating late sequelae like severe xerostomia and temporal lobe radionecrosis. Moreover, adaptive replanning during radiotherapy accounts for tumor shrinkage and significant anatomical variations caused by patient weight loss. Routine verification imaging ensures high target coverage throughout the seven-week course. Thus, comprehensive dosimetric optimization preserves critical functional abilities, including speech and deglutition. Clinical teams should therefore prioritize access to high-precision radiotherapy technologies for all eligible patients.
Historically, radiation protocols delivered uniform high prophylactic doses to extensive bilateral neck nodal basins. However, contemporary multicenter clinical trials confirm that elective nodal de-escalation safely reduces treatment toxicity. Specifically, oncologists can omit prophylactic irradiation of level four and level five-b in patients with negative lower neck disease. As a result, patients experience significantly lower rates of severe dysphagia, neck fibrosis, and hypothyroidism. Furthermore, response-adapted target delineation following induction chemotherapy provides an additional strategy to minimize irradiated healthy tissue. When patients achieve substantial tumor regression after upfront chemotherapy, contouring can safely adapt to the post-induction boundaries. Nevertheless, treating physicians must maintain pre-chemotherapy margins around areas of gross bone invasion to prevent marginal failures. Consequently, precise diagnostic evaluation using high-resolution magnetic resonance imaging remains essential before attempting volume reduction. In addition, quality control reviews prevent geographical target missing during de-escalation. By personalizing radiation volumes to biological response, oncologists successfully preserve patient functional outcomes without compromising locoregional disease control.
Systemic chemotherapy sequencing depends directly on disease stage and individual biological recurrence risks. For instance, patients presenting with stage IB nasopharyngeal carcinoma achieve excellent long-term local control with definitive radiotherapy alone. Therefore, guideline authors advise against routine systemic chemotherapy in stage IB disease. In contrast, patients with stage II disease benefit selectively from concurrent cisplatin-based chemoradiotherapy, particularly when adverse features like elevated pretreatment circulating Epstein-Barr virus DNA are present. For stage III disease, induction chemotherapy followed by concurrent chemoradiotherapy represents the universally recommended standard of care. Large phase three randomized trials confirm that induction regimens significantly improve progression-free and distant metastasis-free survival. Specifically, the guideline panel highlights gemcitabine plus cisplatin and docetaxel, cisplatin, and fluorouracil as preferred induction protocols. Most clinicians favor gemcitabine-cisplatin because it delivers comparable therapeutic efficacy with a noticeably lower rate of neutropenic infections. Moreover, administering systemic therapy upfront eradicates occult micro-metastases early in the disease course. Clinicians should ensure completion of two to three cycles before initiating definitive radiation.
Although induction regimens have largely superseded adjuvant chemotherapy, post-radiation systemic therapy retains importance in specific clinical subgroups. Historically, severe acute toxicity from concurrent chemoradiotherapy limited patient tolerance for intense adjuvant cisplatin combinations. Consequently, recent clinical investigations evaluated oral metronomic chemotherapy as a better-tolerated maintenance alternative. The updated guideline recognizes one year of metronomic capecitabine for patients with high residual recurrence risk following definitive chemoradiotherapy. This includes individuals presenting with persistent post-treatment circulating Epstein-Barr virus DNA or advanced nodal stages. Metronomic capecitabine demonstrates meaningful improvements in failure-free and overall survival without causing intolerable bone marrow suppression or gastrointestinal toxicity. Additionally, traditional intravenous adjuvant doublets remain an option for high-risk patients who did not receive upfront induction therapy. Thus, contemporary practice employs dynamic, response-guided risk stratification rather than applying uniform adjuvant therapies to all individuals. Clinicians should routinely monitor molecular biomarkers after radiotherapy to identify patients requiring prolonged maintenance intervention. Furthermore, close toxicity monitoring ensures optimal medication adherence throughout the maintenance period.
Recent phase three clinical trials have investigated the integration of programmed death-1 inhibitors with definitive chemoradiotherapy. These landmark studies demonstrate statistically significant improvements in event-free and recurrence-free survival among high-risk patients. However, overall survival data remain immature across all published randomized trials to date. Because mature survival benefits are not yet established, the joint panel makes no recommendation for or against routinely adding immunotherapy to induction-concurrent chemoradiotherapy. Furthermore, immune checkpoint inhibition introduces distinct autoimmune toxicities, including endocrinopathies, pneumonitis, and severe colitis. These adverse events demand intensive laboratory monitoring and prompt clinical management. In addition, healthcare teams must consider drug availability, regulatory authorizations, and significant financial toxicity before recommending off-protocol immunotherapy. Therefore, clinicians must engage patients in shared decision-making regarding potential risks and unproven survival advantages. Ongoing clinical follow-up will soon provide definitive evidence regarding the long-term survival impact of immune checkpoint inhibitors in non-metastatic nasopharyngeal cancer. Until then, enrollment in well-designed prospective clinical trials remains the preferred path for testing novel immunotherapeutic combinations.
The updated guidelines specifically endorse gemcitabine plus cisplatin or docetaxel, cisplatin, and fluorouracil as preferred induction chemotherapy regimens. Both combinations consistently demonstrate superior progression-free survival and overall disease control compared to concurrent chemoradiotherapy alone. Clinicians prefer gemcitabine-cisplatin because it produces comparable efficacy with a favorable toxicity profile. Therefore, oncologists recommend completing two to three cycles before initiating definitive radiation therapy for patients with locoregionally advanced presentations.
Radiation oncologists may consider elective nodal de-escalation in highly selected patients showing uninvolved lower neck levels. For instance, sparing nodal levels four and five-b reduces severe radiation-induced toxicity without compromising regional disease control. However, teams must confirm negative nodal involvement using high-resolution magnetic resonance imaging and strict diagnostic criteria. In addition, response-adapted volume reduction requires careful evaluation of post-induction baseline response to prevent marginal recurrences.
Currently, the joint panel makes no recommendation for or against routinely adding immune checkpoint inhibitors to definitive chemoradiotherapy. Although randomized clinical trials demonstrate improvements in failure-free survival, overall survival data remain immature across international cohorts. Furthermore, treatment-related adverse events and economic burdens warrant thorough consideration. Consequently, multidisciplinary cancer teams should individualize decisions based on patient preferences, regulatory drug approvals, affordability, and specific institutional trial protocols.
Disclaimer: This content is for informational and educational purposes only and is not intended as medical advice. Healthcare professionals should always rely on their independent clinical judgment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





The updated CSCO-ASCO guideline outlines modern treatment standards for stage IB-III nasopharyngeal carcinoma, highlighting image-guided IMRT, target de-escalation, preferred gemcitabine-cisplatin induction, and risk-adapted adjuvant capecitabine.
Today

A large retrospective cohort study demonstrates that explainable machine learning models, notably XGBoost, accurately predict hospital admission at emergency triage. By analyzing routine triage parameters, hospitals can streamline bed allocation, decrease boarding times, and alleviate acute care overcrowding.
Today

A new quality-improvement initiative reveals that universal maternal mental health screening in the NICU increased screening rates from 29.5% to 95.0%, with nearly 60% of screened mothers requiring psychosocial referrals, highlighting the urgent need for embedded mental health resources.
Today

The Department of Pharmaceuticals has extended the medical devices PLI scheme to 2035-36 with a Rs 2,700 crore outlay. Featuring relaxed investment barriers and eliminated sales thresholds, the revised framework targets deep manufacturing, high-end diagnostics, critical MedTech components, and supply resilience.
Today
A metabolomic study reveals that aging delays glutathione synthesis and gamma-glutamylcysteine accumulation following muscle injury. Although precursor supplementation targets this enzymatic bottleneck, in vitro tests show no immediate effect on myogenesis, highlighting the complexity of muscle repair in older adults.
Today

A systematic review evaluates psychological interventions for smoking cessation in diabetes, showing short-term success but highlighting challenges in long-term abstinence.
Today
