

Loading, please wait...
Loading, please wait...
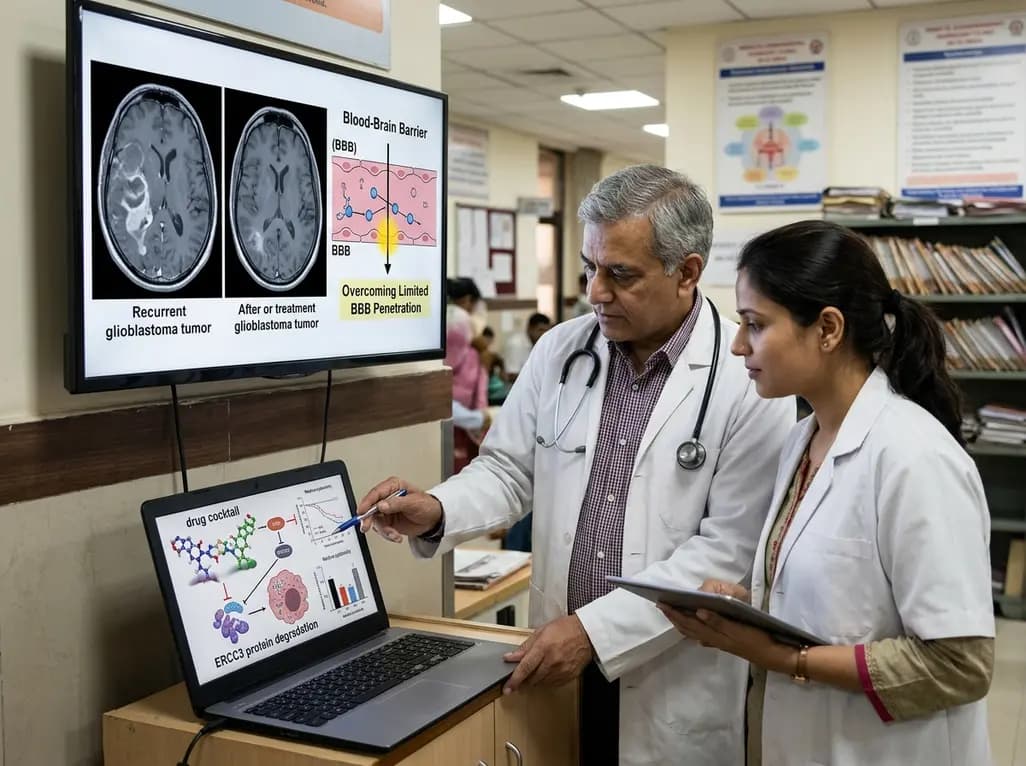
Glioblastoma multiforme remains an aggressive primary brain neoplasm that presents formidable clinical hurdles in neuro-oncology. The recent clinical evaluation of LP-184 in recurrent glioblastoma provides a compelling strategy for patients failing standard temozolomide therapy. LP-184, also known chemically as zirdafulven, belongs to the synthetic acylfulvene class of DNA-alkylating compounds. Unlike traditional non-specific alkylating agents, LP-184 functions as an inactive prodrug. The intracellular oxidoreductase prostaglandin reductase 1, termed PTGR1, bioactivates LP-184 into potent cytotoxic metabolites. Crucially, over seventy percent of glioblastoma tumors overexpress PTGR1, creating an inherent molecular vulnerability. Furthermore, conventional alkylating agents depend heavily on O6-methylguanine-DNA methyltransferase promoter methylation for cytotoxic activity. In contrast, LP-184 exhibits an entirely MGMT-agnostic mechanism of action. This vital characteristic allows the drug to induce lethal DNA lesions in temozolomide-resistant malignancies. Preclinical evaluations demonstrate that transcription-coupled nucleotide excision repair primarily resolves these specific adducts. Consequently, tumors lacking competent excision repair demonstrate heightened susceptibility to the compound. Laboratory cellular models consistently confirm robust growth inhibition and apoptosis across diverse glioblastoma lines.
Central nervous system bioavailability remains the primary obstacle when clinicians administer systemic therapies for intracerebral malignancies. The blood-brain barrier shields infiltrative glioblastoma cells from circulating antineoplastic agents. Therefore, achieving adequate intracranial exposure without excessive peripheral toxicity represents an enduring neuro-oncology challenge. Pharmacokinetic analyses revealed that LP-184 achieves approximately twenty percent intratumoral penetration in clinical settings. Although this penetration is noteworthy, monotherapy concentrations at the recommended dose for expansion might achieve only modest cytotoxicity alone. Consequently, investigators explored rational combinatorial strategies to augment tumor chemosensitivity in the brain. Specifically, laboratory evidence indicated that targeting DNA repair pathways dramatically potentiates drug efficacy. Because transcription-coupled nucleotide excision repair repairs LP-184-induced lesions, inhibiting this pathway leaves cancer cells vulnerable. Impairing repair mechanisms converts tolerable drug exposures into lethal cytotoxic insults inside tumor cells. In addition, this synthetic lethal interaction selectively targets malignant tissue while sparing non-replicating neurons. Thus, transient biochemical sensitization circumvents physical delivery limitations. This novel pharmacological strategy optimizes therapeutic efficacy without requiring hazardous dose escalations.
The Phase 1a trial evaluated intravenous LP-184 across sixty-three adult patients with advanced, refractory solid tumors. Among these participants, sixteen patients presented with recurrent glioblastoma following extensive prior interventions. Importantly, all glioblastoma patients had received standard surgical resection, radiotherapy, and temozolomide before study enrollment. Most participants had also failed additional salvage regimens. Investigators determined that LP-184 exhibited an acceptable and manageable toxicity profile at the recommended dose. Glioblastoma patients frequently experienced Grade 1 or 2 nausea, which medical teams controlled with standard antiemetics. Furthermore, clinicians observed occasional severe thrombocytopenia and elevated transaminase levels in the brain tumor cohort. Compared to non-CNS cohorts, glioblastoma patients displayed a mild tendency toward hepatic and platelet fluctuations. However, severe treatment-related adverse events rarely prompted permanent treatment discontinuations. Most toxicities remained transient and resolved promptly with routine supportive care and dose scheduling. Consequently, the Phase 1a results confirm the clinical safety of LP-184, establishing a clear path for future combination studies.
To overcome limited intracranial bioavailability, translational researchers identified spironolactone as an unexpected synergistic partner. Spironolactone functions as an effective degrader of ERCC3, an indispensable helicase within nucleotide excision repair. Because LP-184 lesions require ERCC3 for repair, its targeted depletion renders glioblastoma cells profoundly chemosensitive. Preclinical experiments showed that three daily doses of spironolactone deplete orthotopic glioblastoma xenograft ERCC3 protein by eighty percent. Furthermore, this depletion sensitizes glioblastoma cell lines to LP-184 by three- to six-fold in vitro. In orthotopic patient-derived xenograft models, spironolactone co-administration doubled tumor LP-184 cytotoxicity. Importantly, spironolactone penetrates the blood-brain barrier effectively and possesses a well-established safety profile. Repurposing this accessible agent induces transient synthetic lethality in malignant gliomas without damaging healthy tissues. Therefore, combining spironolactone with LP-184 converts subtherapeutic tissue concentrations into potent tumoricidal exposures. Consequently, this pairing represents a scientifically robust method to amplify central nervous system efficacy in aggressive brain cancers.
The successful completion of the Phase 1a trial lays the foundation for upcoming Phase 1b and 2a studies. Investigators established a practical, clinically translatable dosing schedule combining pulsed spironolactone with intravenous LP-184. Under this scheme, patients will receive spironolactone preceding LP-184 infusions to achieve maximal ERCC3 degradation during peak drug delivery. Additionally, future trials will evaluate PTGR1 expression as a predictive biomarker to enrich for potential responders. Because seventy percent of glioblastoma tumors overexpress PTGR1, patient selection could accelerate clinical validation. In countries like India, recurrent glioblastoma represents an urgent clinical priority with extremely limited therapeutic alternatives. The inclusion of spironolactone, an inexpensive and globally available cardiovascular drug, offers substantial socioeconomic and logistical advantages. Indian neuro-oncologists frequently encounter recurrent cases where temozolomide resistance precludes effective treatment. While these findings remain investigational, oncologists should monitor ongoing development closely. Ultimately, combining brain-penetrant alkylators with synthetic lethal sensitizers introduces a promising paradigm for aggressive cerebral malignancies.
LP-184 functions as a synthetic acylfulvene prodrug bioactivated specifically by intracellular prostaglandin reductase 1. Unlike temozolomide, which relies heavily on O6-methylguanine-DNA methyltransferase promoter methylation for efficacy, LP-184 operates via an MGMT-agnostic mechanism. Consequently, it creates profound DNA damage even in temozolomide-resistant glioblastoma cells. Repair of LP-184 damage depends on transcription-coupled nucleotide excision repair. Therefore, combining it with specific pathway inhibitors bypasses established clinical resistance patterns in refractory tumors.
Spironolactone acts as a brain-penetrant degrader of ERCC3, an essential helicase component of transcription-coupled nucleotide excision repair. Because LP-184 induces DNA lesions primarily repaired by this machinery, ERCC3 degradation prevents efficient tumor repair. Preclinical studies show that three daily doses of spironolactone deplete tumor ERCC3 protein by eighty percent. Consequently, this targeted combination enhances glioblastoma sensitivity to LP-184 by several folds, achieving potent antitumor cytotoxicity at achievable clinical doses.
During Phase 1a evaluation, patients receiving LP-184 tolerated the compound relatively well without frequent dose-limiting toxicity. The most common adverse events included mild Grade 1 or 2 nausea. However, investigators noted occasional transaminitis and severe thrombocytopenia in patients with glioblastoma. Therefore, oncologists must monitor complete blood counts and liver enzymes diligently during therapy. Early recognition of myelosuppression allows timely supportive interventions and dose adjustments, ensuring patient safety during systemic treatment cycles.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





The Phase 1a trial of LP-184 in recurrent glioblastoma demonstrated manageable tolerability. Translational analyses reveal that pairing LP-184 with spironolactone degrades ERCC3, overcoming limited blood-brain barrier penetration and significantly enhancing central nervous system antitumor cytotoxicity.
Today

A comprehensive analysis of serum bile acid variability establishes robust reference ranges and reveals how sex, age, BMI, and smoking alter circulating profiles.
Today

A retrospective cost-minimization study of 16,695 Medicare patients reveals that pelvic floor muscle therapy and pessaries incur less than half the 1-year costs of primary sling surgery, supporting conservative management as initial therapy.
Today

A user-centered study demonstrates that AI-assisted carotid ultrasound enables nonexpert primary care staff to detect subclinical atherosclerosis. With real-time guidance and workflow optimization, this technology supports early cardiovascular risk communication and task-shifting in routine clinical practice.
Today

A hyaluronic acid-modified metal-polyphenol nanocomposite successfully eliminates reactive oxygen species in chondrocytes, halts cartilage breakdown, and promotes tissue anabolism, presenting a novel disease-modifying strategy for early osteoarthritis.
Today

A pilot randomized trial demonstrates that digital wellness applications and medically tailored meals significantly attenuate rapid weight regain following GLP-1 receptor agonist discontinuation, providing valuable transitional support for long-term obesity management.
Today
