

Loading, please wait...
Loading, please wait...

Clinicians routinely manage pharmacotherapy across diverse patient demographics, yet they frequently overlook the impact of reduced body mass on drug disposition. While extensive medical literature provides clear dosing frameworks for obesity, low body weight dosing remains remarkably understudied in clinical practice. Most pharmaceutical clinical trials enroll healthy adult volunteers who weigh between seventy and eighty kilograms. Consequently, manufacturers establish fixed-dose regimens that fail to account for the unique physiology of underweight individuals. Administering standardized adult doses to patients with low body weight often causes disproportionate drug exposure, unexpected adverse events, and narrow therapeutic margins. Therefore, medical practitioners must understand the distinct pharmacokinetic shifts that characterize cachectic, malnourished, and frail individuals. By adopting an individualized pharmacotherapy approach, healthcare teams can prevent severe medication toxicity while ensuring optimal clinical efficacy across diverse inpatient and outpatient settings.
Patients with low body weight exhibit profound physiological alterations that directly disrupt standard drug handling. First, cachexia and malnutrition markedly change body composition by reducing adipose stores and skeletal muscle mass. Because of this muscle depletion, total body water frequently represents an elevated proportion of overall weight. Hydrophilic medications therefore experience an expanded volume of distribution relative to total mass, which dilutes initial serum peak levels. In contrast, serum albumin concentrations often fall drastically in chronically ill or malnourished individuals. When albumin levels decline, protein-bound medications have fewer binding sites available in the circulation. As a result, the unbound, pharmacologically active drug fraction increases significantly, which escalates toxicity risks even if total measured serum concentrations appear normal. Furthermore, altered hepatic enzyme expression can suppress baseline metabolic clearance pathways. In addition, hemodynamic shifts and critical illness may paradoxically produce augmented renal clearance or cause rapid renal function decline. Consequently, clinicians cannot rely on conventional assumptions regarding steady-state plasma concentrations in these vulnerable individuals. Physicians must recognize that these dynamic alterations transform both loading dose requirements and maintenance regimens. When clinicians fail to anticipate these rapid kinetic changes, patients quickly face severe pharmacological consequences.
Prescribers routinely select body size descriptors to calculate weight-based drug regimens, yet existing metrics show substantial limitations in underweight cohorts. Most established size scalars, including ideal body weight and adjusted body weight, originated from investigations of patients with obesity. However, clinical evidence demonstrates that ideal body weight provides minimal practical utility when clinicians calculate regimens for patients with low body weight. If a physician uses ideal body weight for an underweight patient, the calculated dose frequently exceeds the patient's actual weight-based needs. Consequently, this practice introduces a substantial risk of drug overdosing and acute toxicity. Furthermore, serum creatinine measurements often mislead prescribers who assess renal function in patients with severe muscle wasting. Because malnourished individuals produce less creatinine, baseline serum creatinine levels remain artificially low. As a result, standard mathematical formulas, such as the Cockcroft-Gault equation, substantially overestimate creatinine clearance. Clinicians must therefore avoid relying solely on automated laboratory estimates of kidney function. Instead, healthcare teams should carefully examine actual physical weight, historical weight changes, and temporal clinical trends before selecting a definitive dosing scalar. Moreover, clinicians should incorporate direct measures of renal excretion when adjusting critical narrow-index medications.
A medication's physicochemical characteristics dictate its distribution and elimination behavior in patients with low body weight. Currently, published literature predominantly describes the behavior of hydrophilic agents, such as beta-lactams and aminoglycosides, in underweight populations. Because hydrophilic drugs distribute primarily into extracellular fluid and clear through renal elimination, clinicians can predict their clearance profiles with moderate accuracy. In contrast, researchers have gathered very little pharmacokinetic data regarding lipophilic agents in underweight cohorts. Lipophilic compounds, including many psychotropics, sedatives, and cardiovascular agents, distribute heavily into adipose tissue and clear through complex hepatic pathways. In a patient who lacks adipose reserves, lipophilic drugs cannot accumulate in peripheral fat compartments. Consequently, these medications remain confined to a smaller central volume of distribution, which dramatically increases initial peak plasma concentrations. Furthermore, hepatic metabolic capacity in malnourished patients often declines due to depleted enzymatic cofactors and reduced hepatic blood flow. Therefore, standard adult doses of lipophilic drugs can precipitate severe central nervous system depression or cardiovascular instability. Clinicians must exercise extreme vigilance when initiating lipophilic therapies without established monitoring protocols. Specifically, practitioners should start these agents at the lowest possible doses and titrate upward with close observation.
Antimicrobial and anticoagulant therapies represent the two drug classes with the most documented clinical evidence in underweight populations. Fortunately, both drug classes utilize established surrogate markers, such as therapeutic drug monitoring levels and coagulation assays, that assist clinical decision-making. For example, clinicians routinely measure trough concentrations of vancomycin and aminoglycosides to adjust daily doses safely. In patients with low body weight, standard empiric antibiotic dosing can cause acute nephrotoxicity or lead to clinical failure due to unpredictable distribution volumes. Therefore, clinical pharmacists must obtain early serum trough levels to guide subsequent dosing intervals. Similarly, anticoagulant agents require diligent oversight in low-weight individuals. Low-molecular-weight heparins and direct oral anticoagulants present significant bleeding hazards when prescribers administer fixed adult doses to patients weighing under fifty kilograms. In fact, regulatory agencies explicitly advise dose reductions for specific oral anticoagulants, like apixaban, when body weight drops below sixty kilograms alongside elevated creatinine or advanced age. Consequently, clinicians must consistently verify manufacturer guidelines and measure anti-factor Xa activity or functional coagulation parameters whenever clinical ambiguity arises. In addition, frequent re-evaluation of renal clearance ensures that accumulating drug metabolites do not trigger sudden hemorrhagic complications.
To overcome the hazards of empiric regimens, healthcare institutions must implement structured protocols for low body weight dosing. First, hospital admission workflows should accurately identify individuals who have a body mass index below eighteen or an actual weight under fifty kilograms. Once clinicians identify a patient with low body weight, the multidisciplinary team must classify that individual as belonging to a distinct, vulnerable population. Second, prescribers should actively collaborate with clinical pharmacists to select individualized drug regimens rather than unadjusted fixed doses. Whenever possible, pharmacists should utilize therapeutic drug monitoring for agents that possess narrow therapeutic indices. In addition, bedside nurses must monitor these patients closely for early signs of drug-induced adverse reactions, including unexpected sedation, hypotension, or metabolic disturbances. Furthermore, clinicians should regularly re-evaluate total body weight throughout prolonged hospital admissions. Significant fluid shifts, recovery from acute illness, or progressive nutritional decline will alter clearance mechanics over time. By combining baseline individualized dosing with ongoing clinical surveillance, medical teams successfully safeguard low-weight patients from preventable pharmacological harm. Ultimately, proactive institutional guidelines empower clinicians to navigate the current evidence gap and achieve consistent therapeutic success.
Underweight patients require tailored pharmacological approaches to ensure therapeutic efficacy and avoid toxicity. Below are answers to common clinical inquiries.
Ideal body weight formulas calculate a theoretical weight based on height and gender, which works well for standardizing doses in patients with excess weight. However, when applied to underweight individuals, ideal body weight consistently exceeds the patient's actual total body weight. Consequently, calculating medication doses using ideal body weight leads clinicians to prescribe excessive drug quantities, which directly increases the risk of severe toxicity and dangerous drug accumulation.
Serum creatinine originates from the breakdown of skeletal muscle tissue. Because patients with low body weight often suffer from significant sarcopenia and malnutrition, their baseline creatinine production remains exceptionally low. Therefore, serum creatinine measurements appear deceptively normal or reduced, leading standard mathematical equations to overestimate actual renal clearance. Clinicians must recognize this physiological limitation to avoid inappropriately high dosing of nephrotoxic or renally cleared drugs.
Medications with narrow therapeutic margins, such as anticoagulants, aminoglycosides, glycopeptides, and lipophilic central nervous system agents, carry the greatest risk in underweight individuals. Because standard fixed doses often exceed metabolic or excretory capacity, these drugs can trigger severe hemorrhages, ototoxicity, nephrotoxicity, or profound sedation. Clinicians must prioritize therapeutic drug monitoring, frequent laboratory surveillance, and proactive dose reductions when prescribing these high-risk agents.
Disclaimer: This content is for informational and educational purposes only and does not constitute formal medical advice, diagnosis, or treatment. Healthcare professionals should exercise their independent clinical judgment when evaluating patient care strategies. Always verify dosing regimens, drug indications, and safety profiles against current manufacturer product information and institutional protocols. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Standard adult doses often cause toxicity or therapeutic failure in underweight individuals. This clinical guide explores pharmacokinetic alterations, weight descriptors, and individualized dosing strategies for patients with low body weight.
Today

A recent longitudinal study evaluated the link between prenatal loss of control eating and cardiovascular health using Life's Essential 8 frameworks. While direct associations across pregnancy were non-significant, the high prevalence of dysregulated eating highlights critical implications for obstetric practice.
Today

Explore modern perioperative management protocols for clinical xenotransplantation. Learn how costimulation blockade, anti-inflammatory perfusion, and coagulopathy rescue overcome interspecies hurdles.
Today
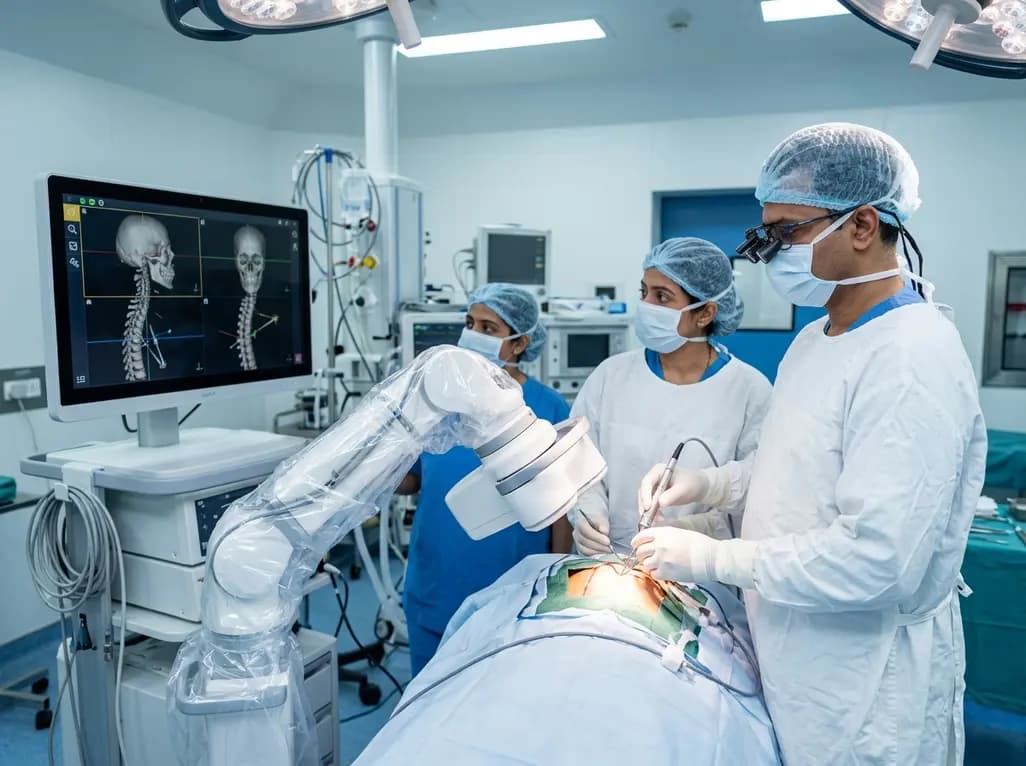
North India's first Centre of Excellence for Brain and Spine at Amrita Hospital Faridabad integrates Brainlab's Loop-X mobile robot. This landmark facility combines cone-beam computed tomography with surgical navigation to elevate precision, optimize operative workflows, and enhance specialized clinician training.
Today

At Homa CME 2026 at Hyderabad's T-Hub, healthcare leaders emphasized moving beyond routine metrics through digital calculators and precision stratification. Discover why characterizing individual insulin secretion, resistance patterns, and vascular risks transforms chronic metabolic care in India.
Today
