

Loading, please wait...
Loading, please wait...

Phakic intraocular lenses offer excellent refractive correction for moderate to high ametropia, particularly when corneal refractive procedures are contraindicated. Over the past two decades, posterior chamber phakic implants have gained significant global popularity among refractive surgeons. However, as these myopic patients age, many eventually develop crystalline lens opacities that require cataract extraction. In these complex clinical scenarios, executing an accurate IOL power calculation becomes critical to achieve target refractive outcomes and avoid post-surgical surprises. Surgeons must recognize that the physical presence of an intraocular implant directly influences modern optical biometers, modifying the baseline measurements needed for intraocular lens selection.
The insertion of an artificial optical element into the posterior chamber alters the path of diagnostic light beams during optical biometry. Swept-source optical coherence tomography biometers, such as the IOLMaster 700, precisely register ocular dimensions from the corneal epithelium to the retinal pigment epithelium. Consequently, the presence of a collamer lens introduces an interface with a distinct refractive index compared to native aqueous humor. Recent clinical trials demonstrate that axial length, steep keratometry, lens thickness, and central corneal thickness show statistically significant shifts one year following implantation. Specifically, axial length displays a measurable increase of roughly 0.02 millimeters. Although this axial deviation appears subtle, it can skew downstream vergence calculations if left unaddressed. Furthermore, crystalline lens thickness measurements often register an apparent increase because the biometric instrument detects the additional optical interfaces created by the implant vault. Therefore, clinicians must interpret post-implantation optical biometry with rigorous care.
Keratometric stability remains a cornerstone of refractive predictability. Interestingly, biometric evaluations reveal minor steepening in corneal curvature following collamer lens surgery, with steep keratometry increasing by approximately 0.08 diopters. Because clear corneal temporal incisions induce subtle biomechanical remodeling, postoperative corneal topography can shift slightly over time. Meanwhile, optical axial length elongation arises primarily from differences in acoustic and optical propagation velocities through collamer material. Swept-source platforms calculate physical distances by assuming standard refractive indices across anatomical ocular compartments. When light traverses a synthetic polymer with a higher refractive index than aqueous fluid, the biometer registers an elongated optical path length. Thus, the system calculates a marginally longer ocular axis than truly exists. While an axial discrepancy of 0.02 millimeters shifts predicted refraction by only a fraction of a diopter, cumulative errors across multiple biometric parameters can compound refractive inaccuracies in highly myopic eyes.
Achieving refractive emmetropia requires selecting robust computational algorithms tailored to atypical anterior segment anatomy. Clinicians now evaluate multiple generations of formulas, ranging from classic vergence models to advanced artificial intelligence systems. Notable platforms include the Barrett Universal II, Cooke K6, Emmetropic Vergence Optical (EVO), Hill-RBF, Hoffer QST, Holladay 1, Kane, Pearl-DGS, and SRK/T formulas. Recent comparative data indicate that the predicted spherical equivalent difference before and after phakic lens implantation varies across these algorithms. Artificial intelligence and theoretical thick-lens formulas, such as Kane and Barrett Universal II, demonstrate excellent resilience against biometric shifts. Conversely, older vergence formulas often exhibit wider deviations in predicted post-surgical refraction. Because high myopes have elongated vitreous cavities, modern formulas compensate better for altered effective lens positions. Consequently, surgeons planning cataract extraction in eyes with existing phakic implants should prioritize new-generation calculators to preserve refractive predictability.
Accurate prediction of the effective lens position represents the single greatest hurdle in modern cataract surgery biometry. Most standard formulas estimate the post-cataract intraocular lens resting plane using preoperative anterior chamber depth, white-to-white corneal diameter, and keratometry. However, an implantable collamer lens occupies space within the posterior chamber, directly vaulting over the crystalline lens capsule. This anatomical displacement can alter anterior chamber depth readouts on optical coherence tomography biometers. If a machine misinterprets the collamer implant as the anterior capsule of the crystalline lens, it calculates a falsely shallow anterior chamber depth. Consequently, the formula predicts an erroneous effective lens position, which drives the algorithm to recommend an incorrect dioptric power. To avoid hyperopic or myopic errors, refractive surgeons should cross-verify automated segmentation lines on swept-source scans. By manually verifying internal ocular landmarks, clinicians ensure that formula inputs reflect genuine anatomical dimensions.
When an eye with a phakic collamer lens requires cataract surgery, clinicians must follow a structured diagnostic workflow. First, obtain pre-implantation biometric records whenever possible, as historic baseline corneal curvature and virgin axial length provide invaluable validation. Second, acquire multiple high-resolution swept-source optical coherence tomography scans to verify that automated software correctly identifies true crystalline lens boundaries. Third, avoid relying on a single computational model. Instead, compare results across multiple modern algorithms, emphasizing the Kane, Barrett Universal II, and EVO formulas. If significant discrepancies emerge between formulas, review anterior chamber depth segmentation and consider optimizing lens constants. Furthermore, counsel patients about potential refractive nuances associated with high axial myopia and prior refractive interventions. By systematically analyzing optical biometry and understanding the physical interactions between phakic implants and biometers, cataract surgeons can consistently achieve outstanding refractive visual outcomes.
Optical biometers measure axial length by evaluating group refractive index across ocular media. Because a collamer lens possesses an optical index different from aqueous humor, it marginally increases total optical path length. Consequently, swept-source optical coherence tomography registers an apparent axial elongation of approximately 0.02 millimeters. Although this slight difference appears minor in routine practice, clinicians must account for it when targeting precise refractive endpoints during subsequent cataract surgery.
Recent clinical investigations show that artificial intelligence and modern vergence formulas maintain high predictive accuracy. Specifically, formulas like Barrett Universal II, Kane, and EVO demonstrate superior reliability because they better accommodate anterior segment variations. Nevertheless, clinicians should double-check keratometry and anterior chamber depth values. Using both the online calculator and device-integrated platforms ensures that minor biometric shifts do not produce unexpected postoperative spherical equivalent surprises.
Surgeons generally do not need to remove the phakic lens prior to biometry. In fact, performing a preliminary lens extraction requires an additional invasive entry and delays definitive visual rehabilitation. Instead, clinicians should acquire high-resolution swept-source optical coherence tomography while the lens remains in place. If significant cataractous opacities prevent reliable optical biometry, surgeons can perform pre-extraction scans or utilize intraoperative aberrometry alongside optimized modern formulas.
Disclaimer: This content is for informational and educational purposes only, and is not a substitute for professional medical advice, diagnosis, or treatment. It does not establish a doctor-patient relationship, nor is it intended to guide clinical intervention. Healthcare professionals should make decisions independently based on clinical judgment and validated research. The opinions expressed do not reflect the institutional views of the author’s employer, organization, or any affiliated entities. For personalized medical advice, always consult a qualified healthcare provider. While information is updated regularly, it may not reflect the latest developments. Neither the author nor publisher assumes liability for any errors, omissions, or actions taken based on this content. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Implantation of an implantable collamer lens modifies anterior segment biometry, slightly altering axial length and keratometry. This clinical review evaluates how these optical changes influence modern IOL power calculation formulas, guiding cataract surgeons toward accurate refractive targeting.
Today

The Delhi High Court has directed the FSSAI and Centre to address petitions regarding dairy analogue products sold as genuine paneer. Learn about the statutory standards, nutritional differences, cardiometabolic health risks, and required consumer disclosure mandates in eateries across India.
Today

The government of Maharashtra is establishing a novel state-level Living Lab to elevate clinical outcomes, bridge public-private service gaps, and test real-world health interventions. By integrating digital innovations and frontline feedback, the platform fosters sustainable, equitable care models across communities.
Today

Cardiac involvement is the leading cause of mortality in EGPA. This report highlights an overlap phenotype of lymphocyte-predominant myocardial injury, Takotsubo-like cardiomyopathy, and left ventricular thrombus, emphasizing early multimodality diagnostics and aggressive immunosuppressive biologic therapy.
Today
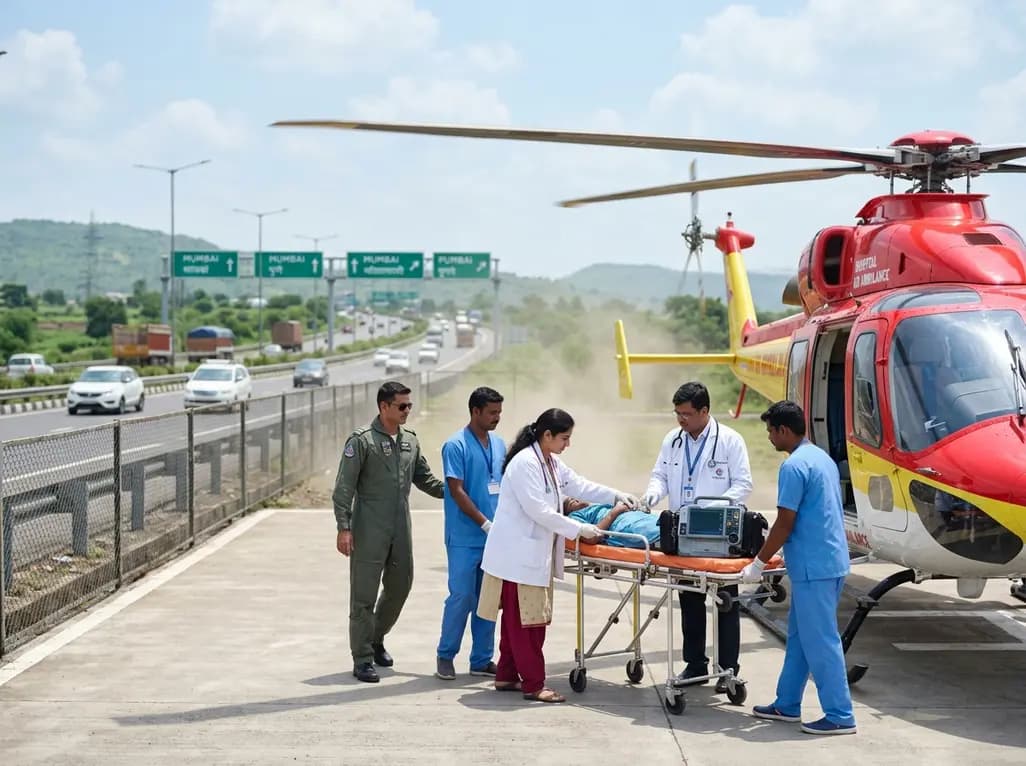
The state government is deploying helicopter emergency medical services across the Mumbai-Pune Expressway, Samruddhi Mahamarg, and Mumbai-Goa Highway. This initiative establishes unified standard operating procedures to enable rapid triage, advanced prehospital resuscitation, and seamless trauma care transfers.
Today

A systematic review and meta-analysis of 5,406 participants reveals that tirzepatide significantly reduces hsCRP by 34.3%, improves cardiorenal biomarkers, and enhances functional capacity and exercise endurance in patients with heart failure.
Today
