

Loading, please wait...
Loading, please wait...

The Food Safety and Standards Authority of India (FSSAI) has intensified its regulatory oversight of popular functional beverage manufacturers. Recently, the national watchdog issued a formal show-cause notice to Red Bull India, challenging its widespread energy drink labeling. The regulatory body pointed out that this beverage derives significant calories from added sugars and caffeine rather than wholesome nutrients. Consequently, authorities demanded robust scientific justification from the company. They questioned why the manufacturer should not face a ban on this designation. For medical practitioners across India, this regulatory action highlights critical clinical concerns regarding stimulant formulations. These beverages present escalating public health challenges, especially among adolescents. Young professionals and fitness enthusiasts also consume them regularly. As retail availability surges, physicians must remain alert to both regulatory actions and the pathophysiological risks of chronic consumption.
The recent notice to Red Bull India marks a decisive step in clarifying national standards for commercial beverages. Historically, statutory frameworks in India categorized these products under general caffeinated beverage provisions. They were not classified as specialized health-promoting tonics. However, commercial marketing strategies frequently blur these distinctions for everyday consumers. The regulatory authority emphasized that designating high-caffeine beverages as functional energy drinks misleads the public. Therefore, FSSAI ordered the manufacturer to submit a detailed scientific explanation within seven days. Furthermore, the regulator flagged the product packaging advisory. This advisory suggests that consumers should avoid exceeding 500 milliliters daily. A serving size of 500 milliliters contains approximately 55 grams of added sugars. This amount exceeds recommended daily intake thresholds for adults. The Delhi High Court had earlier set aside an order against the manufacturer on procedural grounds. The court permitted the regulator to conduct a fresh evaluation. Consequently, this updated action signals an uncompromising approach toward misleading nutritional marketing. Clinicians must understand that commercial branding often conceals potent stimulant mixtures behind promises of physical performance. Moreover, deceptive advertising creates a false sense of healthiness among vulnerable demographic groups.
Caffeine acts primarily as a competitive, non-selective antagonist of central and peripheral adenosine receptors. Consequently, acute ingestion blocks adenosine-mediated neuroinhibition. This blockade increases circulating catecholamines and initiates profound sympathetic nervous system activation. While modest caffeine intake promotes alertness, concentrated doses place significant mechanical stress on the heart. For instance, rapid consumption can induce sinus tachycardia, acute blood pressure surges, and ventricular ectopy. Furthermore, excessive caffeine intake impairs endothelial vasodilation, reducing myocardial perfusion during vigorous exercise. Patients with undiagnosed channelopathies or accessory electrical pathways face elevated risks of sustained arrhythmias. In addition, acute caffeine exposure increases systemic vascular resistance, elevating cardiac afterload in susceptible patients. When young adults consume these drinks rapidly during sports, adrenergic stimulation and dehydration amplify adverse cardiac events. Therefore, physicians evaluating patients presenting with palpitations or chest tightness must specifically ask about energy drink use. Moreover, chronic high-dose caffeine intake disrupts normal sleep architecture by suppressing restorative slow-wave sleep. Persistent sleep disruption elevates diurnal cortisol levels and perpetuates chronic sympathetic overactivity. Consequently, patients enter a dangerous cycle of persistent fatigue and recurrent stimulant dependency.
Beyond potent neurohumoral stimulation, the substantial glycemic burden within commercial energy formulations presents a major health threat. A standard 250-milliliter can often contains more than 27 grams of simple sugars. These carbohydrates consist predominantly of refined sucrose and glucose. Consequently, rapid ingestion triggers an immediate spike in blood glucose levels. This spike prompts massive compensatory insulin secretion from pancreatic beta cells. Repeated exposure to severe postprandial glycemic excursions promotes systemic insulin resistance. Furthermore, this glycemic stress accelerates hepatic de novo lipogenesis. Liquid carbohydrates also fail to elicit normal neuroendocrine satiety responses in the hypothalamus. Therefore, individuals consume substantial excess calories without reducing their solid food consumption. Over time, this recurring nutritional insult promotes visceral adiposity, metabolic syndrome, and non-alcoholic fatty liver disease. Ultimately, these pathways accelerate the onset of type 2 diabetes mellitus. In addition, rapid swings in serum glucose commonly induce reactive hypoglycemia. This rebound leaves consumers fatigued, irritable, and craving further stimulants. Dentists also warn that combining high sugar concentrations with extreme acidity causes rapid enamel erosion. Thus, the metabolic and oral health consequences of routine consumption represent substantial clinical challenges.
The primary commercial target for caffeinated stimulant drinks consists of adolescents, university students, and young athletes. Unfortunately, this younger demographic remains exceptionally vulnerable to promotional messaging and adverse physiological effects. Neurobiologically, the adolescent brain features an actively developing prefrontal cortex. This developmental stage limits impulse control and long-term risk assessment. Consequently, younger individuals readily embrace promotional campaigns that associate these beverages with athletic dominance. Moreover, adolescents have lower average body weights. Standard can sizes deliver substantially higher weight-adjusted doses of caffeine to teenagers. Pediatric practitioners frequently encounter acute caffeine toxicity in youth. Typical presentations include psychomotor agitation, tremors, nausea, severe anxiety, and sleep disorders. Furthermore, combining caffeinated beverages with alcoholic drinks has emerged as a dangerous practice among young adults. The stimulant properties of caffeine mask the subjective feelings of alcohol intoxication without alleviating neuromuscular impairment. As a result, intoxicated individuals often underestimate their impairment, leading to severe injuries and risky behaviors. Therefore, leading pediatric authorities strongly advise that children and adolescents should avoid caffeinated energy drinks entirely. Medical professionals must proactively screen for stimulant use whenever evaluating adolescents presenting with emotional distress.
Physicians across general practice, cardiology, pediatrics, and endocrinology must adopt proactive dietary counseling methods. Clinicians should routinely include specific questions about caffeinated beverages when obtaining lifestyle and nutritional histories. When patients present with chronic exhaustion or daytime somnolence, doctors must identify root etiologies. They should avoid permitting self-treatment with stimulants. For instance, persistent fatigue frequently indicates untreated sleep apnea, iron deficiency anemia, or endocrine disorders. Consequently, relying on stimulant drinks merely masks treatable medical disorders and delays appropriate intervention. Furthermore, healthcare providers should counsel patients on evidence-based strategies for maintaining physiological energy. These strategies include balanced whole-food nutrition, adequate restorative sleep, and regular exercise. For athletic training, doctors should recommend proper oral hydration with water and balanced electrolyte solutions. They should steer athletes away from hypertonic, caffeinated formulations. In addition, physicians must recommend strict avoidance of commercial energy drinks for patients with hypertension. Displaying clear educational materials in outpatient waiting areas can also dispel widespread consumer myths. Ultimately, dedicated patient counseling empowers individuals to make informed choices that safeguard their long-term health.
Q1: Why did FSSAI issue a show-cause notice regarding energy drink labeling?
The Food Safety and Standards Authority of India challenged the term because these beverages derive most of their caloric energy from added sugars and caffeine rather than wholesome nutrients. Regulators noted that promoting such formulations as energy drinks misleads consumers and encourages excessive sugar consumption. Therefore, the authority demanded scientific evidence and regulatory justification from the manufacturer to support its marketing claims and ensure consumer safety across India.
Q2: What primary cardiovascular risks do high-caffeine energy drinks pose?
High caffeine concentrations activate the sympathetic nervous system, leading to elevated heart rates, acute arterial vasoconstriction, and higher blood pressure. In susceptible patients or those with occult cardiac anomalies, rapid consumption can precipitate atrial fibrillation, supraventricular tachycardias, or severe ventricular arrhythmias. Furthermore, combining strenuous physical exercise with energy drink intake increases myocardial oxygen demand while simultaneously reducing endothelial flow, substantially elevating the risk of acute adverse cardiovascular events.
Q3: How should clinicians advise adolescents regarding caffeinated beverage consumption?
Clinicians must firmly advise adolescents to avoid high-caffeine stimulant beverages entirely due to risks of neurological agitation, sleep disruption, and cardiometabolic strain. Pediatric guidelines emphasize that youth possess lower caffeine clearance rates and higher physiological vulnerability. Doctors should recommend balanced hydration with water or natural coconut water for sports. Furthermore, physicians must warn teenagers against mixing energy drinks with alcohol, which masks alcohol intoxication and promotes dangerous, life-threatening impulsive behaviors.
Disclaimer: This content is for informational and educational purposes only. It does not constitute medical advice or replace professional judgment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





The Food Safety and Standards Authority of India has challenged Red Bull over its marketing claims, demanding scientific evidence for the term energy drink. With products packing massive amounts of caffeine and added sugar, clinicians must recognize the critical cardiovascular and metabolic implications for young patients.
Today

A qualitative evaluation of the novel Weight History Interview highlights how capturing weight suppression informs eating disorder assessment while addressing patient emotional acceptability in clinical practice.
Today

Maternal codeine therapy during breastfeeding sparks debate regarding neonatal opioid toxicity. This review re-evaluates the Toronto case, explores PBPK modeling, and highlights how maternal and neonatal pharmacogenomics converge to inform safer postpartum pain management.
Today

A 491-patient cohort study in Sudan reveals critical insights into war trauma reconstructive surgery, analyzing injury patterns, soft-tissue procedures, and a 25.5% complication rate in resource-limited conflict zones.
Today
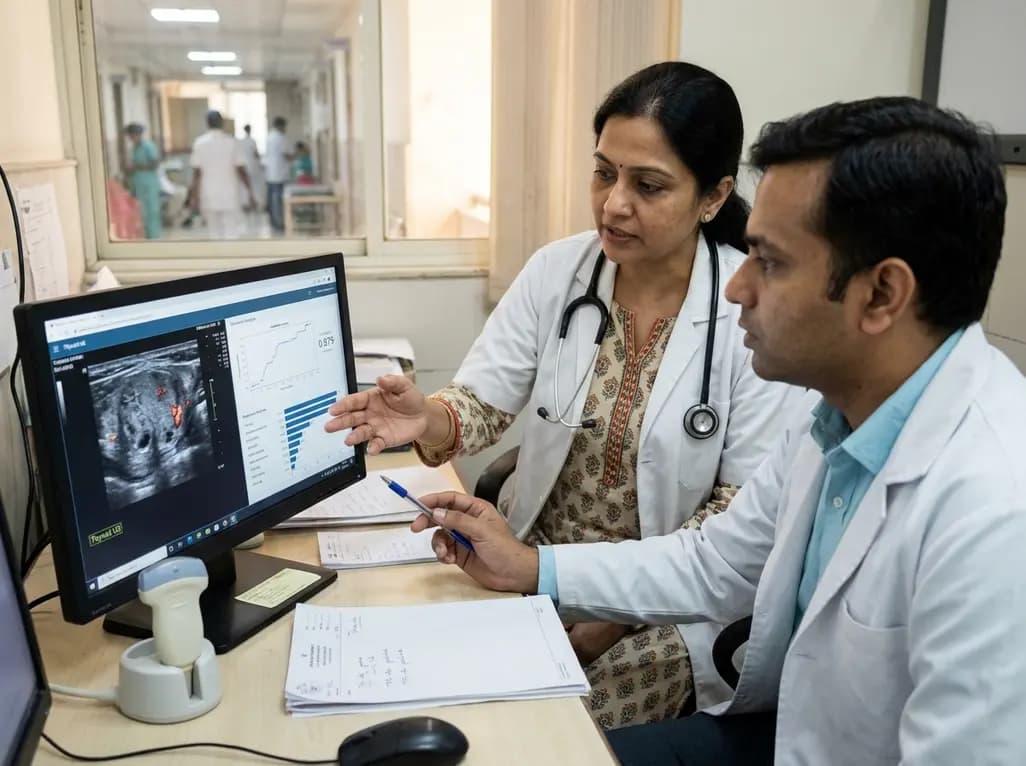
A multi-modal machine learning model integrating ultrasound radiomics, tumor morphology, TPO-Ab, and BRAF V600E accurately predicts lymph node metastasis in papillary thyroid carcinoma with concurrent Hashimoto's thyroiditis, achieving 0.879 accuracy.
Today
