

Loading, please wait...
Loading, please wait...
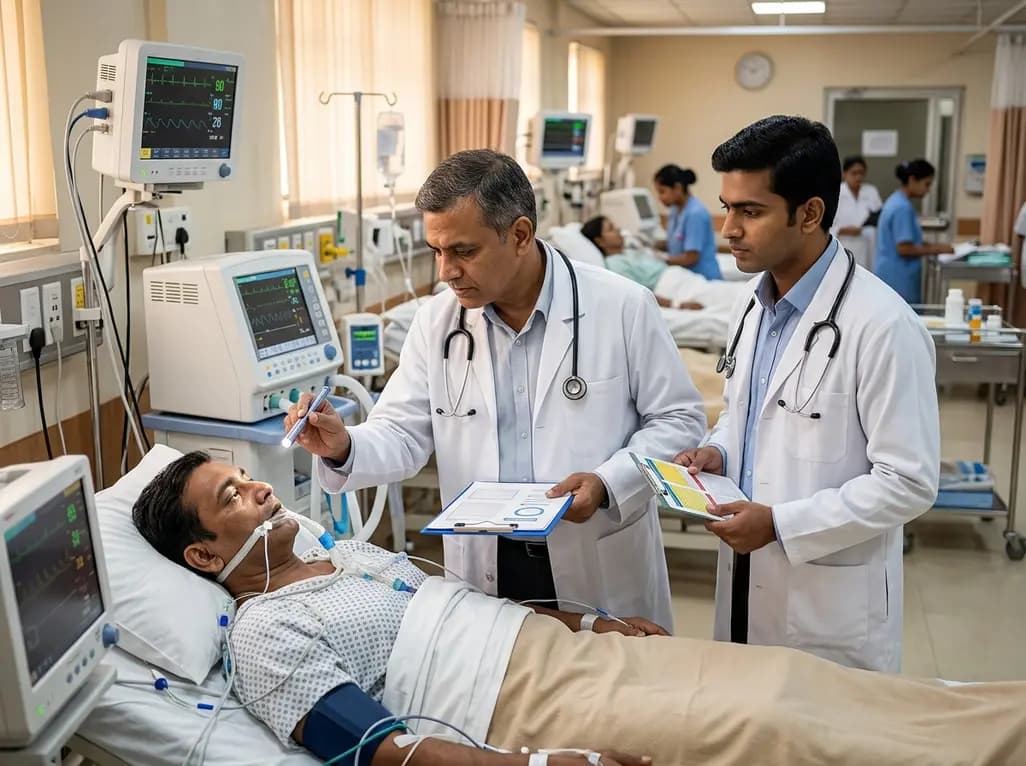
Accurate neurological assessment remains essential in critical care medicine. For decades, clinicians have used the Glasgow Coma Scale (GCS) to measure impaired consciousness and guide clinical management. However, intensive care unit (ICU) teams encounter significant limitations when applying the GCS to critically ill patients. The inability to assess verbal responses in intubated individuals obscures subtle changes in central nervous system function. Consequently, researchers developed the Full Outline of UnResponsiveness (FOUR) score as a comprehensive alternative designed specifically for critical care environments. Comparing the utility of the FOUR score vs GCS helps clinicians evaluate which tool offers superior prognostic accuracy in acute care settings.
The FOUR score evaluates four clinical categories: eye responses, motor responses, brainstem reflexes, and respiratory patterns. Each category receives a score from zero to four, producing a total score between 0 and 16. By incorporating direct testing of pupillary, corneal, and cough reflexes, the tool preserves diagnostic capacity even in non-verbal patients. Monitoring breathing patterns and ventilator synchronization provides actionable clinical data regarding brainstem integrity. Systematic evaluations clarify why the FOUR score offers key clinical advantages in modern intensive care units.
To evaluate the comparative performance of these coma scales, investigators prospectively registered a systematic review in PROSPERO. The authors systematically searched major biomedical databases, including CINAHL, MEDLINE, and Embase, to retrieve prospective observational studies. Eligible investigations enrolled adult patients in the ICU where clinicians measured both the GCS and FOUR score concurrently. Included studies recorded primary clinical outcomes, specifically mortality rates or validated functional outcome scores. Researchers excluded studies that exclusively examined traumatic brain injury cohorts to evaluate general ICU populations effectively.
Two independent reviewers completed screening, data extraction, and quality assessment using the Quality in Prognosis Studies tool. The search strategy identified twenty observational studies representing diverse critical care populations. Quality evaluation revealed that included studies ranged from poor to moderate methodological quality. A key limitation identified across many trials was the exclusion of sedated patients, despite high proportions of endotracheal intubation. Many studies also restricted enrollment exclusively to patients with primary neurological illnesses. These selection choices highlight important methodological gaps that clinicians must consider when interpreting prognostic accuracy.
The systematic review demonstrated notable differences in predictive validity between the two scoring tools. Analysis of receiver operating characteristic curves revealed that the FOUR score achieved higher overall area under the curve (AUROC) values for mortality prediction compared to the GCS. Crucially, the FOUR score demonstrated significantly higher AUROC values when specifically predicting ICU mortality. This enhanced performance stems directly from assessing brainstem reflexes, which provide critical prognostic information regarding severe neurological compromise.
Despite superior mortality prediction, both coma scales exhibited comparable accuracy regarding functional outcomes. Specifically, both scales predicted unfavorable functional performance at discharge with similar diagnostic sensitivity and specificity. However, the FOUR score demonstrated greater clinical responsiveness among patients with profound consciousness impairment. Most patients presenting with a baseline GCS score of 3 received FOUR scores ranging between 1 and 8. This distribution occurred because the FOUR score identified preserved brainstem reflexes and spontaneous respiratory efforts. Consequently, the FOUR score prevents clinical floor effects that obscure baseline neurological variation in deeply comatose patients.
Applying neurological coma scales in general intensive care settings introduces practical challenges. In real-world ICU environments, many patients receive sedative medications or neuromuscular blockade to facilitate mechanical ventilation. Excluding sedated individuals from prospective studies creates selection bias, reducing the generalizability of findings to broad ICU populations. Although sedatives influence eye opening and motor responses, clinicians can still systematically record brainstem reflexes and respiratory drive using the FOUR score format.
Moreover, the heavy representation of primary neurological patients in published literature leaves questions regarding general medical and surgical ICU cohorts. Non-neurological critically ill patients often develop secondary encephalopathy due to sepsis, hepatic dysfunction, or metabolic derangements. Evaluating consciousness accurately in these heterogeneous groups remains essential for early clinical decision-making. Demonstrating that the FOUR score maintains high predictive validity in general ICU patients, including those receiving light sedation, remains a priority for ongoing critical care research. Expanding clinical adoption requires addressing these practical realities through standardized nursing education and routine bedside implementation.
The systematic review findings provide compelling evidence for incorporating the FOUR score into routine intensive care practice. Because mechanical ventilation invalidates the verbal component of the GCS, critical care teams require an objective tool that maintains diagnostic fidelity. The FOUR score enables nurses and physicians to detect subtle neurological deterioration early. Preserving brainstem reflex evaluation allows clinicians to recognize herniation syndromes or brainstem ischemia before complete clinical arrest occurs.
Furthermore, adopting the FOUR score enhances interprofessional communication within multidisciplinary ICU teams. Standardized subscore reporting ensures that physicians, nurses, and neurointensivists share a precise, objective understanding of patient status. Accumulating evidence suggests that the FOUR score offers superior prognostic value for short-term mortality. Integrating FOUR score assessments into electronic health record workflows can streamline clinical documentation. Ultimately, adopting comprehensive scoring tools supports timely diagnostic interventions, refined prognostic estimates, and improved clinical decision-making for critically ill patients.
The main advantage is that the FOUR score does not rely on a verbal response. Instead, it evaluates eye responses, motor responses, brainstem reflexes, and respiratory patterns. This design allows accurate neurological assessment and outcome prediction in mechanically ventilated patients who cannot speak.
The FOUR score overcomes floor effects by testing brainstem reflexes and respiratory drive. Patients with a baseline GCS score of 3 often achieve FOUR scores between 1 and 8. This granular scoring differentiates complete brainstem failure from preserved reflexes, offering better prognostic responsiveness.
The FOUR score achieves higher mortality prediction accuracy because it directly assesses critical brainstem functions, including pupillary, corneal, and breathing reflexes. Loss of these vital brainstem functions strongly correlates with severe brain injury and short-term ICU mortality compared to basic motor or eye responses measured by GCS.
Disclaimer: This content is for informational and educational purposes only and does not constitute medical advice, diagnosis, or treatment. Healthcare professionals should rely on their clinical judgment and refer to current institutional guidelines when assessing critically ill patients. Refer to the latest local and national guidelines for clinical practice.
References
1. Schey JE et al. The Predictive Validity of the Full Outline of UnResponsiveness Score Compared to the Glasgow Coma Scale in the Intensive Care Unit: A Systematic Review. Neurocrit Care. 2025 Oct. doi: 10.1007/s12028-024-02150-8. PMID: 39496882.
2. Wijdicks EF et al. Comparison of the Full Outline of UnResponsiveness score and the Glasgow Coma Scale in predicting mortality in critically ill patients. Crit Care Med. 2015 Feb;43(2):439-45. doi: 10.1097/CCM.0000000000000707. PMID: 25393699.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A systematic review evaluating the FOUR score versus the Glasgow Coma Scale (GCS) in intensive care units demonstrates that the FOUR score offers superior predictive validity for ICU mortality and higher responsiveness in patients with severely impaired consciousness.
2 months ago

As monsoon seasons elevate arboviral disease threats, Tamil Nadu has initiated an ICMR-monitored evaluation of the tetravalent dengue vaccine in Tenkasi district. Clinicians emphasize clinical monitoring, public prevention, and high-quality early pediatric care to reduce disease morbidity across endemic regions.
Today
A comparative cohort study evaluates vNOTES vs TLH hysterectomy for benign conditions, demonstrating shorter operative duration, faster return to daily activities, and equivalent female sexual function scores without increased dyspareunia.
Today

Review how tailored exercise programs benefit frail older patients with heart failure. Explore pathophysiological mechanisms, individualized training prescriptions, and strategies to overcome adherence barriers in clinical practice.
Today
This comparative study evaluates posterior labral tears with and without glenohumeral instability, highlighting distinct demographic patterns, MRI underestimation in stable shoulders, and successful arthroscopic repair outcomes.
Today

A clinical study demonstrates that early intervention with tocilizumab, either as monotherapy or bridged with corticosteroids, achieves significant proptosis reduction and resolves active inflammation in treatment-naive thyroid eye disease.
Today
