

Loading, please wait...
Loading, please wait...

Adult mood disorders represent an escalating public health crisis worldwide, yet clinical detection typically occurs long after maladaptive neurodevelopmental pathways have solidified. Consequently, researchers actively seek early markers of depression during infancy and toddlerhood to inform timely interventions. Identifying actionable developmental signals during early childhood provides a unique window to alter lifelong psychological trajectories.
Longitudinal population cohorts offer exceptional opportunities to trace mental health outcomes across key developmental transitions. The Western Australian Pregnancy Cohort, known as the Raine Study, originally enrolled nearly three thousand mothers between 1989 and 1991. Subsequently, investigators monitored their offspring through infancy, childhood, adolescence, and young adulthood. In this evaluation, researchers analyzed data from fourteen hundred participants who completed assessments during infancy and adult follow-up. Specifically, the study team gathered parent-reported behavioral ratings at ages one and two years. Decades later, participants self-reported depressive and anxiety symptoms between ages twenty and twenty-seven through the Depression, Anxiety and Stress Scale. Because prospective birth cohorts spanning a quarter-century remain scarce, these evaluations provide critical empirical insights into developmental continuity. Therefore, clinicians gain an invaluable window into how toddler behavioral patterns correlate with adult affective distress. Ultimately, such extensive observation clarifies whether brief early behavioral assessments hold enduring prognostic value.
The primary investigation examined whether parental evaluations during early toddlerhood could reliably serve as early markers of depression in adulthood. Clinicians utilized the Child Behaviour Checklist total problem score, a standardized screening tool that measures emotional and behavioral difficulties. Importantly, the analysis demonstrated that a one standard deviation increase in the age-two score heightened the odds of moderate adult depression by thirty-two percent. However, the checklist demonstrated much weaker predictive capability for adult anxiety symptoms, indicating a distinct trajectory for depressive pathology. Exploratory evaluations also revealed modest associations for internalizing and externalizing subscales. Additionally, specific infant temperament domains, such as high intensity of reaction and distractibility at age one, exhibited minor predictive value. In contrast, the infant monitoring questionnaire administered at ages one and two failed to forecast adult outcomes. These findings indicate that while parental toddler evaluations remain imprecise, they clearly capture meaningful developmental signals. Consequently, healthcare practitioners should recognize elevated early behavioral difficulty as an informative indicator of future affective vulnerability.
Observational studies spanning multiple decades naturally encounter substantial risks regarding attrition and parental reporting biases. To counteract these methodological limitations, the investigators implemented rigorous multivariable statistical modeling. Furthermore, the researchers incorporated parental self-evaluations and external teacher ratings to examine whether maternal mood influenced the toddler assessments. Reassuringly, the statistical analyses demonstrated that shared familial evaluative bias did not significantly alter the primary conclusions. In addition, selective participant attrition across the two-decade follow-up period did not skew the central statistical associations. The robust methodology thus strengthens confidence in the observed predictive connection between early toddler behavior and adult affective states. Nevertheless, clinicians must interpret these results with appropriate nuance and caution. Toddler checklist scores provide probabilistic risk estimates rather than definitive individual diagnostic forecasts. Therefore, early behavioral markers should prompt supportive surveillance rather than premature clinical labeling. By addressing systematic biases, the study establishes a credible baseline for psychiatric risk stratification across childhood.
Understanding why toddler behavioral difficulties foreshadow adult depressive symptoms requires examining fundamental neurodevelopmental processes. Early childhood represents a sensitive period of rapid synaptogenesis, neural myelination, and emotional circuit formation. During this stage, innate emotional reactivity and emerging executive control systems establish foundational self-regulation capacities. When young toddlers exhibit persistent internalizing or externalizing challenges, they may already experience dysregulated stress-response circuitry. For instance, heightened hypothalamic-pituitary-adrenal axis reactivity frequently accompanies dysregulated childhood temperament. Moreover, persistent early behavioral challenges can disrupt positive parent-child interactions, generating bidirectional developmental stress. In addition, persistent emotional dysregulation often impairs early peer relationships, further compounding internalizing vulnerabilities. Over time, these dynamic exchanges compound, increasing vulnerability to depressive episodes during emerging adulthood. Consequently, early behavioral manifestations likely represent early phenotypic markers of underlying neurobiological vulnerabilities. Thus, neurodevelopmental continuity underscores the biological plausibility of early childhood risk identification.
Pediatricians and primary care physicians occupy prime positions to identify emerging developmental concerns during routine health supervision visits. However, clinicians must avoid applying definitive diagnostic labels to toddlers based solely on screening instruments. Instead, providers should view elevated toddler problem scores as practical catalysts for supportive caregiver guidance. For example, clinicians can recommend structured parent guidance programs that strengthen responsive caregiving and child emotional regulation. Furthermore, the study offers valuable pragmatic implications for psychiatric clinical trial design. Conducting preventive trials that monitor human cohorts across three decades presents nearly insurmountable logistical and financial hurdles. Therefore, clinical investigators urgently require validated intermediate surrogate endpoints for prevention research. The study authors cautiously suggest that age-two checklist scores could serve as practical outcome measures in early intervention studies. Although these scores remain imprecise prognostic tools for individual patients, they provide sufficient population-level sensitivity for pragmatic research. Ultimately, establishing viable early surrogate endpoints accelerates the discovery of effective preventive interventions.
No, the Child Behaviour Checklist cannot diagnose adult depression. While elevated scores at age two correlate with a thirty-two percent increased risk of moderate adult depression, the tool remains an imprecise screening instrument. Clinicians use it to identify early developmental vulnerabilities and guide supportive parenting rather than establishing adult psychiatric diagnoses.
Infant monitoring questionnaires primarily assess general motor, communication, and cognitive milestones rather than affective and socioemotional functioning. In contrast, the Child Behaviour Checklist measures internalizing and externalizing behavioral patterns. Because adult depressive disorders originate within emotional regulatory circuits rather than basic developmental milestones, general developmental questionnaires lack predictive sensitivity for psychiatric outcomes.
Clinicians can support toddlers by offering anticipatory caregiver guidance and evidence-based positive parenting strategies. Interventions focusing on parental responsiveness, predictable daily routines, and emotion co-regulation help soothe dysregulated stress systems. Furthermore, pediatricians should schedule periodic developmental follow-ups to track emotional progression and connect struggling families with community support resources.
Disclaimer: This content is for informational and educational purposes only and should not be considered medical advice or relied upon for clinical decisions. What works for one person may not work for another. Please consult a qualified healthcare professional before making health-related decisions. The opinions expressed here are those of the author and do not reflect the views of any other organization. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A 25-year longitudinal analysis from the Raine Study reveals that elevated Child Behaviour Checklist scores at age two predict adult depressive symptoms. Learn how toddler behavioral markers offer surrogate endpoints for early intervention trials and guide preventive pediatric care.
Today
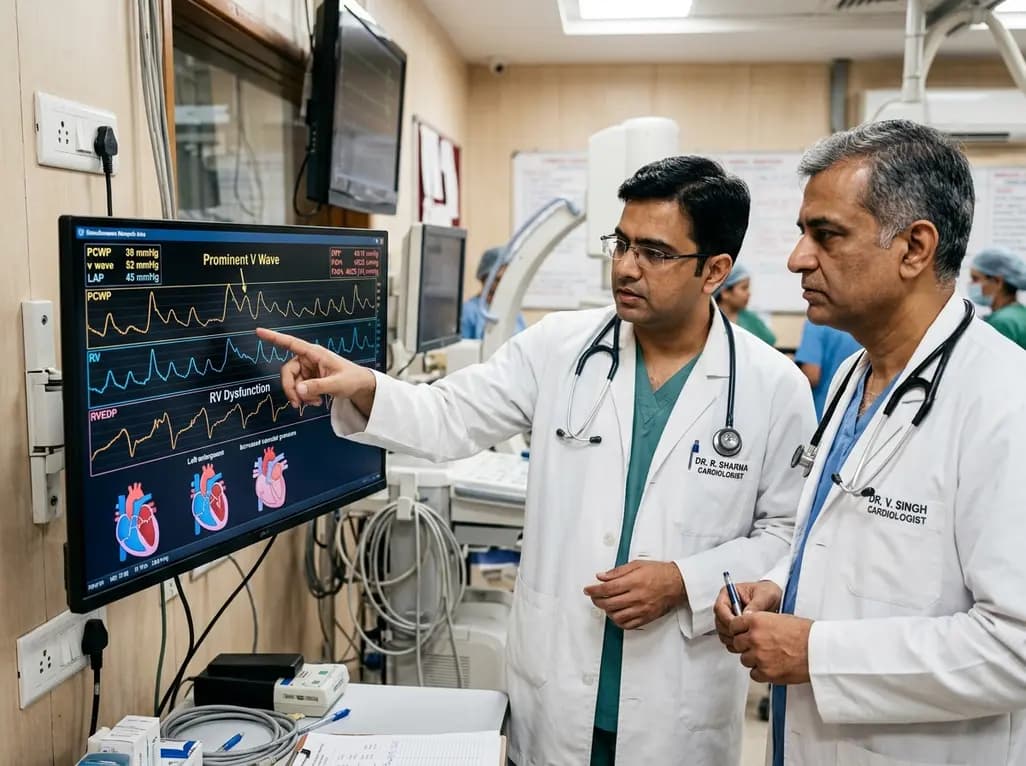
Left atrial stiffening generates prominent V waves that pressurize the pulmonary circulation and augment right ventricular afterload independently of intrinsic pulmonary vascular disease in patients with heart failure with preserved ejection fraction.
Today

A meta-analysis demonstrates that secondhand smoke exposure significantly elevates fetal loss risk by 21% among nonsmoking pregnant women. Clinicians must implement household screening and family-centered cessation interventions to prevent avoidable miscarriages and stillbirths.
Today

Preclinical validation demonstrates that a novel contact force-integrated pulsed field quantization index accurately predicts lesion depth in real time, achieving 100% durable pulmonary vein isolation without collateral injury.
Today
A new cross-sectional evaluation reveals how regional lean mass and bone mineral content interact in resistance-trained men, showing that whole-body size and allometric scaling explain shared musculoskeletal phenotypes and strength relationships.
Today

Explore the emerging role of glucose metabolic reprogramming in exercise-attenuated osteoporosis, examining how physical activity influences osteoblast glycolysis, osteoclast bioenergetics, and skeletal remodeling pathways to improve bone mineral density.
Today
