

Loading, please wait...
Loading, please wait...

Artificial intelligence continues to transform modern clinical workflows, diagnostic pathways, and risk stratification systems. However, machine learning algorithms frequently inherit systemic disparities embedded within legacy electronic health records. Addressing AI bias in healthcare requires rigorous, multistage evaluation rather than isolated statistical adjustments. A landmark study published in JMIR AI by Mateedulsatit and colleagues introduces a comprehensive framework designed to detect and mitigate multifaceted biases across diverse clinical datasets. This systematic approach reveals critical trade-offs between mathematical fairness, predictive discrimination, and statistical calibration.
Clinical decision support systems rely heavily on historical data that reflect existing healthcare disparities. Consequently, standard algorithmic models can inadvertently propagate these inequities across patient populations. Bias in machine learning rarely arises from a single, isolated anomaly. Instead, it stems from interconnected issues including representation gaps, proxy variable errors, data integrity failures, and temporal shifts. For example, underrepresented minority cohorts frequently experience higher rates of unmeasured clinical confounders and missing documentation. Furthermore, traditional imputation methods often treat missing values as completely random occurrences. In real-world hospital environments, clinicians order laboratory tests selectively based on acute severity, clinical suspicion, or insurance status. Therefore, omitting or mishandling informative missingness distorts risk scores significantly. When data science teams apply naive correction techniques, they often address only one dimension while ignoring systemic data skew. Ultimately, developing robust clinical algorithms demands an overarching strategy that methodically audits data ingestion, feature transformation, and post-prediction equity.
To tackle multiple sources of disparity simultaneously, researchers engineered a reproducible, prespecified multistage auditing and mitigation framework. The investigators evaluated this unified workflow against standard baseline algorithms using extensive clinical cohorts, including the Diabetes 130-US Hospitals dataset and the Centers for Medicare and Medicaid Services Synthetic Public Use Files. The baseline model utilized a conventional random forest architecture with median and mode imputation. In contrast, the advanced mitigation model incorporated explicit missingness indicators alongside poststratification sample weights clipped at the 95th percentile. Furthermore, the protocol strictly excluded sensitive attributes such as race from direct predictive feature sets, reserving demographic parameters strictly for downstream auditing and reweighting. The authors evaluated multiple audit domains across five distinct stages: representation balance, missingness patterns, proxy target validity, laboratory data integrity, and temporal stability. By applying deterministic data splits and hundreds of stratified bootstrap replicates, the research team established an audit standard that rigorously evaluates algorithm fairness across diverse demographic subgroups.
The primary evaluation in the Diabetes 130-US Hospitals cohort encompassed 20,203 test encounters from 14,304 unique patients, capturing 2,254 positive readmission outcomes. The missingness-aware, poststratified mitigation pipeline demonstrated notable improvements across several core performance metrics. Specifically, the macro F1-score increased from 0.514 in the baseline model to 0.546 in the mitigated architecture. Additionally, the model improved overall probability calibration, reducing the Brier score from 0.231 to 0.213. Demographic parity difference dropped substantially from 0.206 to 0.124, indicating more equitable positive prediction rates across racial groups. However, these equity gains came with measurable trade-offs. The area under the receiver operating characteristic curve decreased slightly from 0.648 to 0.640. Furthermore, the equalized odds ratio deteriorated from 0.444 to 0.291, highlighting divergent true positive and false positive rates. When the authors tested this methodology on Medicare claims episodes, the mitigation architecture failed to reproduce the fairness gains observed in the diabetes cohort. Similarly, an exploratory rule-gated mixture of experts architecture failed to outperform the primary mitigation model.
The empirical findings underscore a fundamental mathematical and ethical dilemma in digital health: the pervasive trade-off among fairness, calibration, and discrimination. Clinical machine learning systems rarely achieve simultaneous optimization across every desirable metric. For instance, adjusting algorithmic decision thresholds to achieve demographic parity often impairs classification discrimination or degrades equalized odds. When a model balances selection rates across demographic groups, it may inadvertently alter false positive rates in specific sub-cohorts. Moreover, claims-based administrative datasets present distinct statistical properties compared to granular inpatient electronic health records. Claims data often lack physiological nuances, resulting in disparate algorithmic behavior when data scientists apply identical mitigation scripts. Consequently, healthcare leaders cannot rely on universal debiasing recipes across different clinical contexts. Instead, clinical informatics teams must explicitly decide which fairness definitions align with clinical safety, therapeutic utility, and ethical resource distribution. Relying solely on aggregate area under the curve metrics conceals critical demographic vulnerabilities and creates a false sense of algorithmic reliability.
For healthcare providers and health system administrators, these findings carry profound practical implications. First, technical mitigation alone does not establish clinical deployment readiness. Healthcare institutions must implement continuous, multidimensional algorithmic surveillance before deploying predictive models at the bedside. Second, clinical teams must actively participate in defining fairness criteria for predictive algorithms. Clinicians understand the direct medical consequences of false negative classifications, such as missed diabetic decompensation or delayed post-discharge monitoring. Therefore, clinical governance committees must weigh whether demographic parity, predictive parity, or equalized opportunity best serves patient safety. Third, hospitals should adopt transparent reporting standards that mandate stratified bootstrap evaluations and calibration assessments across all demographic subgroups. Finally, medical software developers must treat missing data as informative clinical signals rather than administrative nuisances. By combining comprehensive data auditing, clinical oversight, and context-specific mitigation strategies, healthcare organizations can safely harness artificial intelligence while safeguarding equitable patient care.
AI bias in healthcare stems from historical disparities embedded within medical records, non-representative training datasets, and systemic care access differences across diverse populations. Furthermore, flawed proxy variables, unmeasured clinical confounders, selective laboratory ordering, and inconsistent documentation practices distort machine learning models. When algorithms learn from these skewed patterns, they unintentionally perpetuate or amplify unequal clinical decisions and diagnostic inaccuracies across vulnerable demographic groups.
Missingness-aware weighting incorporates explicit indicators for missing clinical values and applies poststratification adjustments to balance demographic representation during model training. In clinical evaluations, this approach significantly improves demographic parity, macro F1-scores, and probability calibration across hospital cohorts. However, it can also induce measurable trade-offs by slightly lowering discrimination metrics and altering equalized odds ratios across diverse patient populations.
Debiasing techniques frequently create complex trade-offs between mathematical fairness, discriminative accuracy, and probability calibration rather than providing uniform performance gains across all clinical endpoints. Moreover, a mitigation strategy that succeeds on inpatient records may fail on claims-based datasets. Therefore, healthcare organizations must conduct extensive prospective validation, subgroup auditing, and local clinical risk assessments before deploying models in real-world patient care.
Disclaimer: This content is for informational and educational purposes only. It is not intended to replace professional medical advice, diagnosis, or treatment. Healthcare professionals should apply their clinical judgment and verify details independently. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A new study in JMIR AI validates a unified multistage framework to detect and mitigate AI bias in healthcare, revealing critical trade-offs between demographic fairness, calibration, and discrimination.
3 weeks back

Explore the emerging role of Brixadi, an extended-release buprenorphine injection, for managing stimulant use disorder through kappa opioid receptor antagonism and steady plasma levels.
Today

A premature neonate developed upper limb compartment syndrome after uterine rupture extruded the arm through a scar defect. Conservative management with continuous monitoring yielded complete functional recovery and normal limb growth at 10-year follow-up, highlighting non-operative safety in selected cases.
Today
Dendritic cells bridge innate and adaptive immunity in myocardial infarction. This review explores their pathological roles, circulating dynamics, novel tolerogenic interventions, and how standard cardiovascular medications modulate dendritic cells to improve post-infarction myocardial repair and patient outcomes.
Today
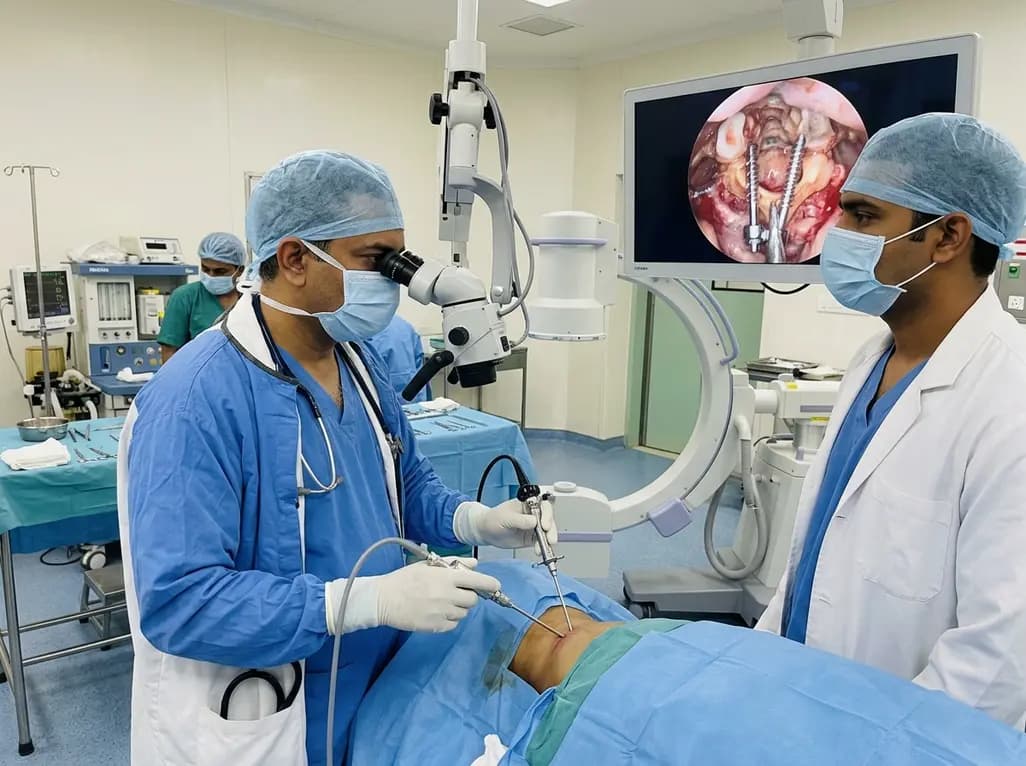
Endoscopic posterior cervical fusion combines minimally invasive decompression, joint preparation, and rigid screw-rod fixation for atlantoaxial pathologies. Early clinical findings demonstrate solid bony union, excellent symptom relief, and minimal soft-tissue morbidity without significant vascular compromise.
Yesterday
Atherosclerosis involves extensive glycometabolic reprogramming across immune and vascular cells. This review examines how glycolysis, the pentose phosphate pathway, and lactate-driven epigenetic shifts fuel plaque vulnerability, while highlighting novel therapeutic targets like PFKFB3 and LDHA.
Today
