

Loading, please wait...
Loading, please wait...

Trauma teams frequently encounter mild traumatic brain injury in emergency departments across the globe. Traditional triage protocols emphasize neurological scores and immediate intracranial findings on neuroimaging. However, clinicians often overlook baseline medical health when estimating early mortality. Emerging nationwide evidence shows that pre-existing comorbidity strongly shapes early survival among conscious trauma patients.
For decades, emergency assessment of head trauma has focused on the Glasgow Coma Scale. Clinicians readily categorize patients presenting with scores between thirteen and fifteen as mild cases. Consequently, standard pathways often assume favorable prognoses for these conscious patients. However, this narrow focus creates dangerous blind spots during early clinical triage. A patient may present fully awake yet harbor substantial systemic frailty. Furthermore, structural intracranial hemorrhage frequently accompanies blunt cranial trauma, even among awake individuals. When physiological reserves are depleted, minor mechanical insults trigger catastrophic downstream complications. Chronically diseased vascular beds cannot tolerate acute swings in blood pressure. Additionally, impaired organ function limits clearance of resuscitation fluids and emergency medications. Traditional trauma scores fail to capture these underlying vulnerabilities. Therefore, acute care teams must look beyond cranial computed tomography scans alone. Integrating pre-injury physical status into routine evaluation offers a clearer understanding of genuine patient vulnerability. Recognizing pre-existing deficits allows clinicians to intervene aggressively before systemic decompensation occurs.
A recent nationwide investigation examined the prognostic value of baseline health using the Swedish Trauma Registry. Researchers analyzed data collected between 2018 and 2023, capturing over eight thousand adults with blunt cranial trauma. Specifically, every enrolled subject had an admission Glasgow Coma Scale score above twelve. Investigators compared these head-injured patients against an age-matched trauma cohort without intracranial pathology. Notably, the mild cranial injury cohort demonstrated a significantly worse pre-injury health profile. Over twenty-seven percent of these individuals presented with severe baseline systemic illnesses. In contrast, only twenty-four percent of non-head trauma controls presented with comparable systemic disease. Moreover, low-energy falls caused twenty-eight percent of brain injuries, compared to twenty percent among controls. This mechanism highlights the growing burden of ground-level falls among vulnerable older adults. Thirty-day all-cause mortality reached five percent in the cranial injury cohort. Conversely, the non-head injury group suffered a mortality rate of only 2.8 percent. Furthermore, unfavorable functional outcomes afflicted nearly a quarter of brain injury survivors. These robust registry data confirm that awake cranial trauma carries substantial risk.
The investigation revealed a striking graded relationship between pre-existing health and short-term survival. The American Society of Anesthesiologists physical status classification reliably stratified patient risk across the cohort. After researchers adjusted for chronological age and intracranial injury severity, baseline health remained strongly predictive. Specifically, patients with mild systemic disease faced nearly triple the odds of death compared to healthy individuals. Furthermore, individuals presenting with severe systemic illness experienced more than four times higher mortality odds. Most alarmingly, patients classified with life-threatening comorbidity endured twenty-one times greater odds of thirty-day death. These dramatic risk escalations persisted independently of structural neuroimaging severity. Thus, baseline physiological impairment actively drives mortality in awake head trauma presentations. Comorbid cardiovascular disease, chronic obstructive pulmonary disease, and diabetes limit systemic resilience following acute trauma. In addition, coagulopathies and antiplatelet therapies increase the risk of progressive intracranial hematoma expansion. Therefore, mortality in awake patients often reflects systemic failure rather than direct brain herniation alone. Clinicians must acknowledge baseline physiological status as an essential prognostic marker.
The Swedish study also evaluated whether baseline health behaves differently in non-neurological trauma cases. Intriguingly, the age-matched non-brain trauma cohort exhibited a remarkably parallel graded mortality pattern. Patients with higher physical status scores faced steep survival penalties regardless of anatomical injury location. However, the pattern of injury-related covariates differed substantially between the two clinical groups. In cranial trauma, localized hemorrhagic progression interacts synergistically with systemic metabolic stress. Meanwhile, systemic trauma patients frequently face severe hemorrhagic shock, long bone fractures, and soft tissue disruptions. Nevertheless, baseline comorbidity independently amplified early mortality across both clinical populations. This finding demonstrates that pre-existing health governs how the human body withstands physical injury. When baseline physiological reserves are compromised, even minor traumatic insults can provoke irreversible clinical decline. Consequently, hospital systems cannot evaluate acute trauma purely through the lens of anatomical damage scores. Instead, clinicians must adopt an integrated perspective combining injury metrics with comprehensive physiological assessments. Understanding this shared biological vulnerability helps hospital teams design standardized critical pathways across surgical disciplines.
These empirical findings demand meaningful changes in how emergency departments manage awake head injury patients. Traditionally, physicians discharge many conscious patients after obtaining an unremarkable initial neurological examination. However, individuals with high physical status scores require elevated clinical suspicion and vigilant observation. Hospital teams should consider admitting these patients to intermediate care or step-down monitoring units. In addition, clinicians must review chronic pharmacotherapy immediately upon emergency arrival. Antiplatelet agents and direct oral anticoagulants require rapid laboratory assessment and prompt reversal when appropriate. Furthermore, acute care physicians must aggressively manage physiological parameters, including blood pressure, oxygenation, and glucose levels. Secondary cerebral insults exacerbate primary microvascular injury when systemic reserves are fragile. Moreover, trauma services should incorporate routine geriatric and internal medicine consultations into clinical pathways. Multidisciplinary collaboration ensures that chronic cardiac, renal, and pulmonary diseases receive optimal concurrent management. Ultimately, proactive supportive care prevents systemic decompensation and reduces preventable post-injury mortality. Adopting comprehensive risk scoring transforms routine trauma care into precision emergency medicine.
The American Society of Anesthesiologists classification provides an objective, rapid summary of baseline systemic health and physiological reserve. Consequently, it enables emergency clinicians to identify awake trauma patients who carry a substantially elevated risk of secondary deterioration and thirty-day mortality, even when initial neurologic examinations appear deceptively benign and stable.
Although advancing age increases baseline vulnerability, multivariable regression models confirm that systemic comorbidity exerts an independent effect. Specifically, patients with higher classification scores experience significantly increased mortality risk across all age groups. Therefore, physiological illness severity contributes distinct prognostic information beyond chronological age when evaluating acute trauma outcomes.
Clinicians should consider intensive monitoring and early repeated neurological assessments for high-risk patients. In addition, admitting teams must optimize concurrent chronic medical disorders, manage anticoagulation promptly, and maintain adequate cerebral perfusion. Furthermore, multidisciplinary collaboration between neurosurgeons, emergency physicians, and geriatricians ensures comprehensive support during the critical post-injury window.
Disclaimer: This content is for informational and educational purposes only and should not be considered medical advice. Always consult a qualified healthcare provider for diagnosis and treatment recommendations. Refer to the latest local and national guidelines for clinical practice.
References
Kiwanuka O et al. ASA class is independently associated with 30-day mortality after mild traumatic brain injury with intracranial injury: a national retrospective cohort study. Acta Neurochir (Wien). 2026 May 09. doi: 10.1007/s00701-026-06900-9. PMID: 42105095.
Thelin EP, Nelson DW, Bellander BM. ASA-score is associated with 90-day mortality after complicated mild traumatic brain injury – a retrospective cohort study. Acta Neurochir (Wien). 2024;166(1):354.
Skaga NO, Eken T, Søvik S, Jones JM, Steen PA. Pre-injury ASA physical status classification is an independent predictor of mortality after trauma. J Trauma. 2007;63(5):972-978.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Swedish registry data show that pre-injury ASA physical status independently predicts 30-day mortality after mild traumatic brain injury. Patients with severe systemic disease face significantly higher odds of death, emphasizing the urgent need to integrate comorbidity into acute trauma risk stratification.
Today

An Australian cohort of 34,449 adults in an unsubsidized tirzepatide digital weight loss service showed that peer-referred patients achieved significantly higher 6-month adherence (48% vs 42%) and greater weight loss (16.16% vs 14.06%) than matched non-referred peers, highlighting social support in obesity care.
Today

A randomized crossover study demonstrates that conventional and robotic laparoscopy require distinct neuropsychological and psychomotor skills. While trainees master conventional laparoscopy faster, robotic proficiency demands individualized, adaptive curricula tailored to specific learner profiles.
Today
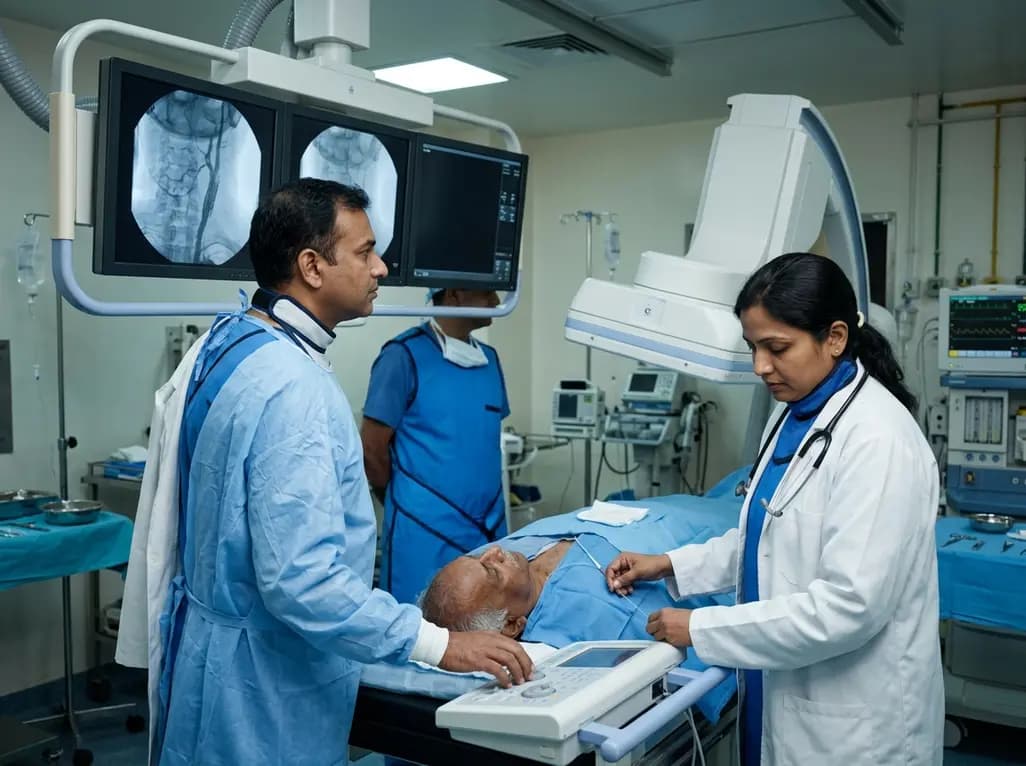
A retrospective study of 109 patients undergoing elective carotid artery stenting evaluated radiation exposure on biplane flat-panel systems. Standardized workflows and dedicated low-dose protocols provide crucial baseline data to establish neurointerventional diagnostic reference levels and optimize patient safety.
Today
A scoping review of 51 studies reveals that spinal manual therapy on the lumbo-pelvic area is commonly used for isolated lower extremity pain, predominantly knee conditions. While thrust manipulation is frequent, reporting deficits highlight the need for standardized technique descriptions to guide practice.
Today

The Supreme Court has reserved its judgment on FSSAI's proposed front-of-pack nutritional warning labels for packaged foods. With debates over compliance timelines, added versus total sugars, and ultra-processed food definitions, this landmark decision carries profound public health implications for India.
Today
