

Loading, please wait...
Loading, please wait...
Pediatric neuro-oncology teams continuously balance curative tumor eradication against treatment-related toxicities. Postoperative craniospinal irradiation serves as an essential standard of care for children presenting with embryonal central nervous system malignancies. However, delivering radiotherapy for medulloblastoma presents substantial clinical challenges due to the extreme radiosensitivity of developing pediatric tissues. Historically, conventional photon radiotherapy delivered exit doses that traversed anterior thoracic structures, pelvic organs, and uninvolved brain parenchyma. Consequently, children frequently suffered acute systemic toxicities and debilitating late cognitive deficits. Over recent years, particle beam therapy has emerged as a promising alternative. Protons exhibit a unique physical Bragg peak, depositing ionizing radiation within targeted tissues with minimal exit dose. Therefore, protons significantly reduce radiation exposure to healthy organs at risk surrounding the neuraxis. Recently, a Swedish national multicenter study compared acute side effects between proton and photon modalities. This pivotal trial provides crucial real-world data regarding whether proton delivery truly reduces early treatment complications among pediatric medulloblastoma patients. Furthermore, these findings assist multidisciplinary pediatric oncology tumor boards in evaluating radiation techniques during treatment planning.
The Swedish multicenter retrospective investigation evaluated 96 consecutive pediatric patients diagnosed with medulloblastoma who received craniospinal irradiation. Within this nationwide cohort, 37 children received active pencil-beam scanning proton therapy, whereas 59 children underwent photon-based radiotherapy. Researchers collected comprehensive demographic, clinical, and dosimetric data from all major academic medical centers across Sweden. Additionally, the investigators graded acute adverse events using the Common Terminology Criteria for Adverse Events version 5.0. Clinicians meticulously documented side effects occurring from the initiation of irradiation up to three months post-treatment. Because patient characteristics and chemotherapy protocols were comparable between both cohorts, confounding variables were minimized. Furthermore, the researchers calculated absorbed radiation doses to critical intracranial organs at risk. These evaluated structures included the cochleae, brainstem, hippocampus, vestibular apparatus, and hypothalamic-pituitary axis. As a result, the investigators established an exceptional framework to assess both symptom severity and physical radiation absorption. Ultimately, this rigorous design ensures dependable evidence for radiation oncologists globally. Notably, the long-term inclusion period captured evolving technological advances in radiation delivery, reflecting modern clinical oncology standards.
During craniospinal irradiation, pediatric patients routinely experience acute treatment-related symptoms that require aggressive supportive intervention. In this multicenter cohort, researchers observed no statistically significant differences in acute toxicity rates between proton and photon cohorts. For example, grade 2 or higher fatigue developed in 5.4 percent of proton recipients compared to 10.2 percent of photon recipients. Similarly, headache of grade 2 or greater severity occurred in 2.7 percent of proton patients versus 3.4 percent of photon patients. Nausea represented the most common acute adverse event across both therapeutic groups. Specifically, grade 2 nausea affected 24.3 percent of proton patients and 25.4 percent of photon patients. Moreover, grade 3 nausea developed in 18.9 percent and 16.9 percent of children, respectively. Radiation dermatitis appeared somewhat less frequently among proton recipients, occurring in 5.4 percent compared to 15.3 percent of photon patients. However, this numerical difference remained statistically non-significant. In addition, no patient in either cohort developed grade 2 or greater gastrointestinal toxicity during active radiotherapy. Consequently, clinicians can reassure families that acute symptom severity remains broadly equivalent between these two advanced radiation techniques.
Maintaining baseline nutritional status and preserving bone marrow reserves are critical goals during intensive pediatric neuro-oncology treatment. Throughout craniospinal irradiation, acute mucosal irritation and persistent nausea frequently impair oral intake in young children. In this national cohort, grade 2 or greater weight loss occurred in 10.8 percent of proton patients and 8.5 percent of photon patients. Because these trajectories remained statistically indistinguishable, supportive nutritional interventions proved equally vital across both groups. Furthermore, children in both treatment arms required comparable frequencies of antiemetic prescriptions and supplemental feeding strategies. Similarly, hematologic suppression occurred with comparable frequency during active treatment. Radiation oncologists originally hypothesized that proton therapy might spare circulating blood cells by eliminating exit doses through anterior vertebral structures. However, craniospinal target volumes still encompass extensive bone marrow reservoirs throughout the spine and cranium. Therefore, transient cytopenias remain common regardless of beam modality. Clinicians must maintain routine laboratory surveillance, dedicated pediatric nursing, and proactive supportive care to prevent infectious complications or treatment interruptions. Additionally, early dietitian involvement helps young patients maintain optimal nutritional parameters during demanding treatment courses.
Although acute symptom profiles demonstrated parity, dosimetric evaluations established undeniable physical advantages for proton beam delivery. Specifically, proton therapy achieved statistically significant dose reductions to multiple intracranial organs at risk outside the primary tumor bed. By eliminating exit radiation, proton beams protected the cochleae, vestibular structures, and temporal lobes from superfluous exposure. Furthermore, proton therapy delivered substantially lower mean absorbed doses to the hypothalamic-pituitary axis and hippocampal formations. While these dosimetric reductions do not immediately alter acute side effects like nausea or fatigue, they critically determine long-term functional survivorship. Pediatric radiation oncologists recognize that radiation exposure to hippocampal structures strongly correlates with late neurocognitive decline. Similarly, excessive radiation to the pituitary gland precipitates growth hormone deficiency and other lifelong endocrine sequelae. Therefore, dosimetric sparing during treatment provides a profound foundation for preserving intellectual capacity and hormonal health in growing children. Ultimately, these physical advantages justify expanding specialized proton infrastructure to optimize long-term pediatric survivorship. Consequently, reducing incidental tissue irradiation remains a primary objective in modern pediatric curative cancer management.
Proton and photon radiotherapy produce highly comparable acute side effect profiles during pediatric treatment. Retrospective multicenter evidence confirms no significant variance in the rates or severity of acute fatigue, headache, nausea, dermatitis, or weight loss. Consequently, pediatric patients tolerate both radiation modalities similarly throughout active craniospinal irradiation courses.
Although acute toxicities remain similar, proton radiotherapy provides superior physical dose distribution. Protons deposit energy precisely at the Bragg peak with zero exit dose, sparing sensitive non-target tissues. This dosimetric advantage drastically reduces absorbed radiation to the cochleae, hippocampi, and endocrine organs, preventing devastating late cognitive, hearing, and hormonal deficits.
Comprehensive supportive care requires proactive antiemetic management, structured nutritional interventions, and rigorous skin care protocols. Clinicians frequently prescribe 5-HT3 receptor antagonists to counteract nausea during craniospinal delivery. Additionally, regular monitoring of complete blood counts, weight trajectories, and caloric consumption ensures prompt intervention before complications cause unintended treatment delays or clinical decline.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A nationwide multicenter study compared acute side effects between proton and photon radiotherapy for medulloblastoma in 96 pediatric patients. Both modalities exhibited comparable acute toxicity profiles, while proton therapy provided superior dosimetric sparing of critical intracranial organs at risk.
last month
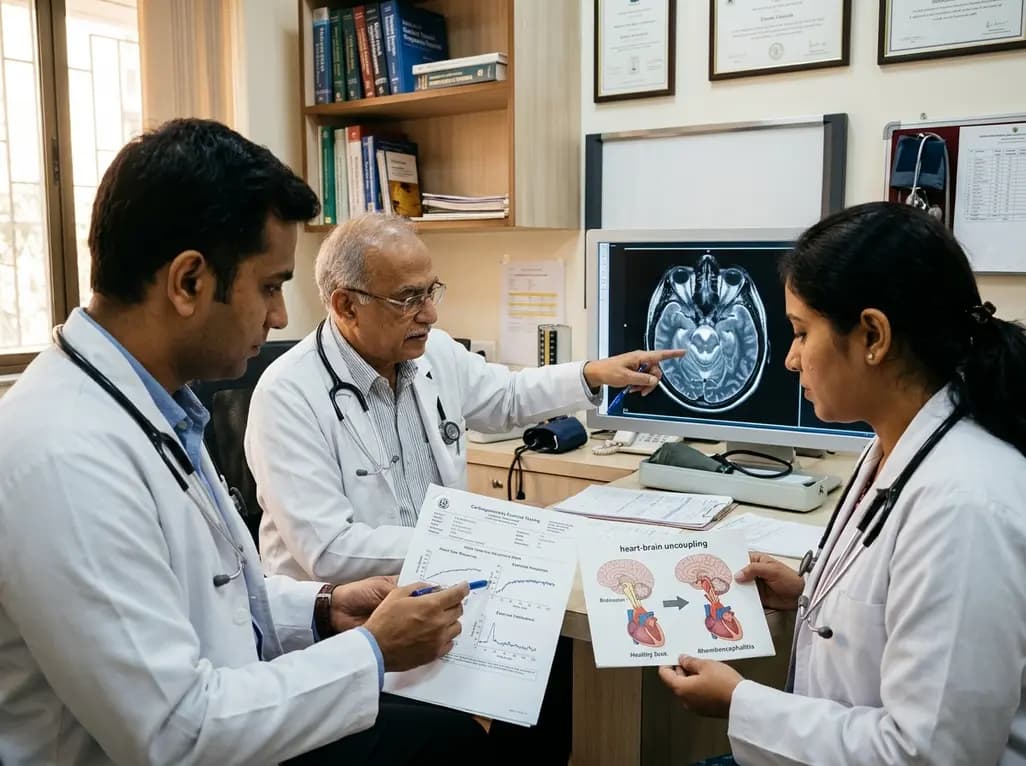
Central chronotropic incompetence is an underrecognized sequela of rhombencephalitis causing exertional dyspnea despite normal resting cardiac function. Cardiopulmonary exercise testing unmasks this heart-brain uncoupling, guiding rate-responsive pacing and targeted rehabilitation.
Today
Perimenopause brings erratic hormonal surges and metabolic shifts that significantly affect breast tissue. This comprehensive clinical review examines benign breast conditions, cancer risk stratification, mammographic density challenges, and endocrine therapy transitions in midlife women.
Today
A registry study of 4,989 patients evaluates transvenous lead extraction for right-sided cardiac devices. Despite longer dwell times and older leads, right-sided extractions achieve high procedural success and comparable safety to left-sided approaches.
Today
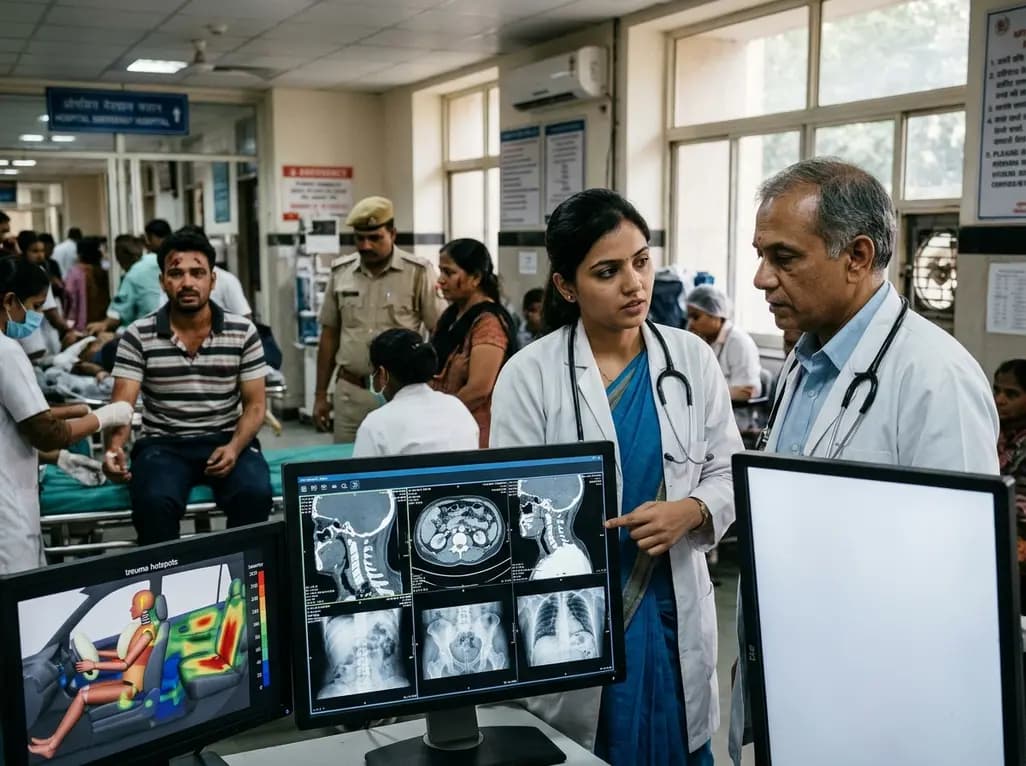
Recent crash analyses demonstrate significant variations in traffic injury severity across vehicle seating positions. Electric vehicle passengers face disproportionately higher trauma risks than drivers, particularly during airbag deployments, demanding adapted emergency assessment and clinical vigilance.
Today

Understand the causal role of Lipoprotein(a) in cardiovascular disease, why international guidelines recommend once-in-a-lifetime molar testing, and the clinical implications of recent phase 3 RNA outcome trials.
Today
