

Loading, please wait...
Loading, please wait...

Asthma remains a major global respiratory challenge that affects over 300 million individuals globally. Although standard inhaled therapies control symptoms for most patients, approximately 3% to 10% suffer from severe asthma. For these difficult cases, the emerging role of depemokimab in severe asthma represents a transformative therapeutic milestone. Specifically, this innovative biologic targets eosinophilic airway inflammation through a sustained ultra-long-acting dosing strategy.
Severe asthma imposes substantial clinical, physical, and economic burdens on patients and modern healthcare systems. In most uncontrolled cases, persistent type 2 airway inflammation orchestrates chronic bronchial hyperresponsiveness, tissue remodeling, and unpredictable disease flares. Eosinophils act as primary effector cells within this immunological pathway, releasing cytotoxic proteins that directly damage respiratory epithelium. Consequently, patients with elevated eosinophil levels suffer frequent exacerbations that require emergency visits or hospitalization. Furthermore, clinicians often prescribe rescue systemic corticosteroids to control these acute episodes. However, frequent systemic steroid exposure causes serious complications, including osteopenia, metabolic derangements, hypertension, and adrenal suppression. Therefore, suppressing eosinophil-driven inflammation represents a vital cornerstone in clinical management. Existing biological therapies successfully target specific cytokine pathways to alleviate this burden. Nevertheless, many patients experience significant treatment fatigue from frequent injections every few weeks. In addition, missed appointments compromise long-term disease stability. Because of these challenges, pulmonologists actively seek potent therapeutic agents that ensure durable eosinophil clearance while substantially reducing administration frequency.
Depemokimab is the first ultra-long-acting monoclonal antibody developed specifically for type 2 respiratory diseases. The fully humanized immunoglobulin molecule binds to interleukin-5 with sub-picomolar affinity, exerting potent antagonistic effects. Because interleukin-5 regulates eosinophil maturation, activation, and survival, blocking this cytokine effectively dismantles the downstream inflammatory cascade. Additionally, molecular modifications within the constant domain enhance neonatal Fc receptor affinity. This engineering promotes cellular recycling and substantially prolongs the elimination half-life. As a result, depemokimab produces rapid and sustained reductions in blood and tissue eosinophils following subcutaneous delivery. While conventional anti-IL-5 monoclonal antibodies require dosing every four to eight weeks, depemokimab enables a 26-week administration interval. Consequently, patients receive only two subcutaneous injections each year. Moreover, persistent target inhibition ensures continuous cytokine suppression throughout the six-month window. Pharmacodynamic evaluations confirm that circulating eosinophil counts drop promptly and remain suppressed for six full months. Ultimately, this sustained suppression prevents inflammatory rebounds and reinforces durable clinical stability.
Robust clinical trials demonstrate the efficacy and safety profile of depemokimab in severe asthma. The pivotal phase 3 SWIFT-1 and SWIFT-2 replicate trials evaluated depemokimab across broad international patient cohorts. Enrolled adolescents and adults aged 12 years and older had severe eosinophilic asthma despite receiving optimized controller therapy. Investigators randomly assigned participants to receive either depemokimab 100 mg subcutaneously or placebo at baseline and week 26. In the pre-specified pooled analysis, depemokimab achieved a statistically significant 54% reduction in annualized clinically significant exacerbations compared with placebo. More importantly, depemokimab reduced exacerbations requiring emergency department care or hospitalization by 72%. This reduction represents a crucial outcome because hospitalizations carry considerable clinical risks and drive medical expenses. Furthermore, secondary analyses revealed meaningful decreases in cumulative oral corticosteroid requirements across 52 weeks. The incidence of adverse events remained comparable between the active drug and placebo arms, confirming excellent tolerability. Thus, these findings show that biannual dosing provides potent protection against debilitating asthma attacks.
Type 2 inflammation affects the entire respiratory tract, creating substantial overlap between lower and upper airway inflammatory conditions. Specifically, chronic rhinosinusitis with nasal polyps (CRSwNP) coexists in up to 40% of patients diagnosed with severe asthma. This comorbid presentation severely impairs quality of life and increases exacerbation frequency. Fortunately, the replicate phase 3 ANCHOR-1 and ANCHOR-2 trials evaluated depemokimab in patients suffering from inadequately controlled severe CRSwNP. Both clinical trials successfully met their coprimary endpoints over 52 weeks. Patients receiving twice-yearly depemokimab achieved significant reductions in endoscopic nasal polyp scores compared to placebo. Additionally, participants demonstrated clinically meaningful improvements in subjective nasal obstruction scores. Furthermore, depemokimab treatment improved sense of smell and reduced the need for repeated sinus surgeries or rescue systemic steroids. Regulatory authorities have approved depemokimab for both severe eosinophilic asthma and severe CRSwNP. Consequently, respiratory physicians can utilize a single targeted biologic agent to manage both mucosal compartments simultaneously, offering comprehensive united-airway control.
Thoughtful patient selection ensures optimal therapeutic value when prescribing depemokimab in everyday pulmonary practice. Clinicians should primarily consider this agent for adolescents and adults who demonstrate an eosinophilic phenotype and experience frequent, severe exacerbations. Patients facing logistical challenges with clinic visits or suffering from injection anxiety represent another ideal group. Administering an injection every 26 weeks substantially lessens treatment burden compared with monthly regimens. Moreover, coordinating biologic administration with routine semiannual specialist reviews reinforces overall disease monitoring. Clinicians can evaluate inhaler technique, comorbidity control, and spirometry during the same visit. However, physicians must communicate realistic expectations regarding day-to-day symptom relief. In the SWIFT trials, depemokimab significantly reduced exacerbation rates, but improvements in quality of life scores and spirometry did not reach statistical significance over placebo. Therefore, patients whose chief objective is preventing acute hospitalizations and debilitating attacks derive the greatest value. Ultimately, depemokimab offers an effective, convenient option that simplifies severe asthma care.
Depemokimab introduces an ultra-long-acting formulation requiring administration only once every 26 weeks, establishing a convenient twice-yearly schedule. In contrast, existing anti-IL-5 monoclonal antibodies like mepolizumab and reslizumab require subcutaneous or intravenous delivery every four weeks, while benralizumab requires dosing every eight weeks. By dramatically reducing annual injection frequency, depemokimab minimizes clinical visits, lessens injection discomfort, and eases the lifestyle burden for patients managing chronic type 2 respiratory illness.
Patients aged 12 years and older with uncontrolled severe eosinophilic asthma represent the primary candidates for depemokimab therapy. Specifically, individuals experiencing repeated asthma exacerbations despite high-dose inhaled corticosteroids gain profound protection. Furthermore, depemokimab provides exceptional dual benefit for patients who also suffer from comorbid chronic rhinosinusitis with nasal polyps. Finally, patients with documented adherence challenges or severe injection fatigue benefit significantly from shifting from frequent monthly regimens to a biannual injection schedule.
Phase 3 clinical trials demonstrated that depemokimab exhibits a reassuring safety profile comparable to placebo. The overall incidence of treatment-emergent adverse events, including headaches, upper respiratory tract infections, and local injection-site discomfort, remained balanced between treatment groups. Severe adverse reactions were exceptionally rare, and investigators observed no novel toxicities. Consequently, the biannual administration of depemokimab provides sustained biological suppression of eosinophils while preserving patient safety throughout prolonged treatment intervals in diverse clinical populations.
Disclaimer: This content is for informational and educational purposes only. It is not intended as medical advice, diagnosis, or treatment. Healthcare professionals must exercise independent clinical judgment. Refer to the latest local and national guidelines for clinical practice.
References
Miralles-López JC et al. Positioning of Depemokimab in Uncontrolled Severe Asthma. J Investig Allergol Clin Immunol. 2026 Oct 19. doi: 10.18176/jiaci.1229. PMID: 42895519.
Jackson DJ, Korn S, Mathur SK, et al. Twice-Yearly Depemokimab in Severe Asthma with an Eosinophilic Phenotype. N Engl J Med. 2024;391(24):2337-2349. doi: 10.1056/NEJMoa2406673.
Bachert C, Han JK, Desrosiers MY, et al. Efficacy and safety of twice-yearly depemokimab in patients with chronic rhinosinusitis with nasal polyps: results from the ANCHOR-1 and ANCHOR-2 phase 3 randomized trials. Lancet Respir Med. 2025;13(4):315-327.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Depemokimab offers twice-yearly dosing for severe eosinophilic asthma and chronic rhinosinusitis with nasal polyps, significantly cutting exacerbations and hospital admissions.
Yesterday

A novel copper metal-organic framework hydrogel remodels the uterine microenvironment to stimulate robust endometrial regeneration, reduce intrauterine fibrosis, and restore reproductive fertility, offering a groundbreaking strategy for managing refractory endometrial damage and Asherman syndrome.
Yesterday
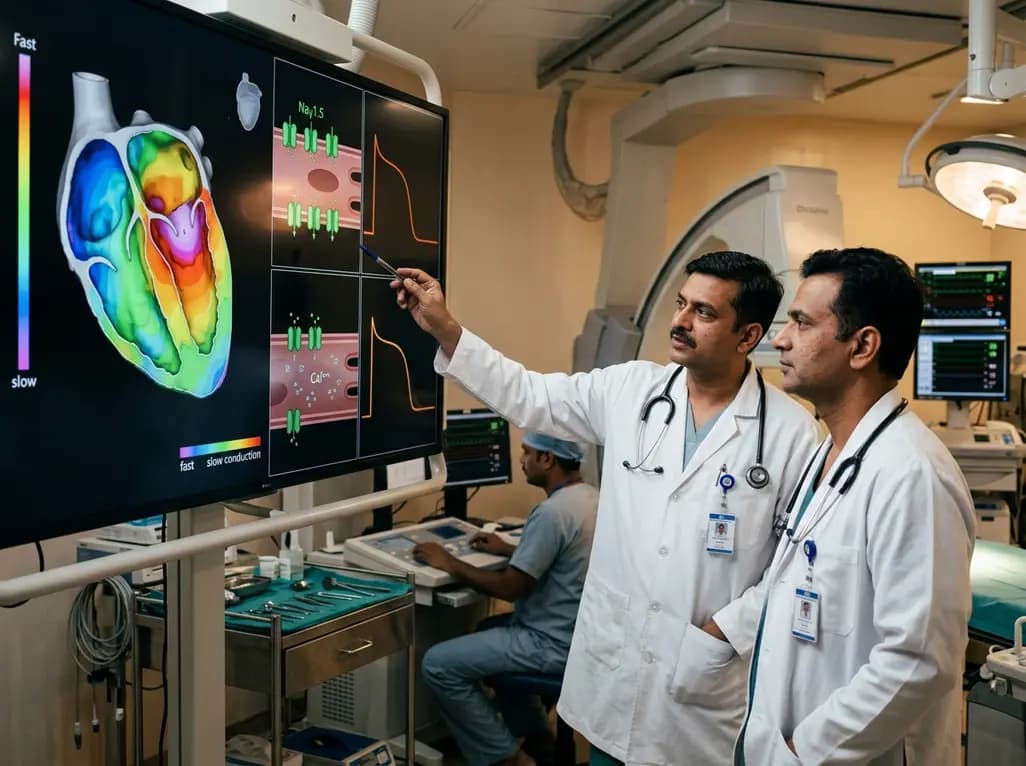
New research reveals that non-ablative radiotherapy suppresses ventricular tachycardia by increasing conduction velocity via NaV1.5 upregulation and action potential prolongation. However, sustained sodium current elevation and depressed calcium handling highlight the need for careful clinical translation.
3 days back

A single-cell transcriptomic atlas reveals how peripheral nerve injuries cause dorsal root ganglion remodeling. By evaluating proximal nerve crush and resection, researchers identify distinct glial and immune programs that resolve neuropathic pain and promote regeneration.
Yesterday

A breakthrough study demonstrates that fullerol-primed extracellular vesicles generated in a 3D SECCS bioreactor attenuate ferroptosis and restore myogenic regeneration in diabetes via the FOXO3 pathway, offering a cell-free therapeutic strategy for diabetic musculoskeletal degeneration.
Yesterday
