

Loading, please wait...
Loading, please wait...

Cognitive decline presents an escalating public health crisis worldwide. Clinicians continuously evaluate modifiable risk factors to delay or prevent neurodegenerative conditions. Compelling real-world evidence highlights the complex relationship between hearing loss and dementia. A nationwide 15-year follow-up cohort study from Taiwan provides robust longitudinal epidemiological insights into how sensory deficits directly influence cognitive vulnerability. Consequently, understanding these audiological and neurovascular intersections is critical for modern geriatric and neurological care.
Age-related sensory impairment frequently coincides with subtle neurological decline. However, epidemiologists have long debated whether auditory deficit represents an early symptom or a direct causal driver of neurodegeneration. The association between hearing loss and dementia has gained immense prominence because auditory pathways provide continuous neurosensory stimulation to cerebral networks. When peripheral auditory input diminishes, cortical reorganization occurs rapidly. Therefore, sustained sensory deprivation triggers structural changes in temporal lobe regions that govern both speech perception and declarative memory consolidation.
Furthermore, untreated auditory impairment imposes a substantial cognitive load on aging adults. Patients must allocate extensive neural resources toward basic auditory processing and acoustic decoding. As a result, fewer cognitive reserves remain accessible for working memory, attention switching, and executive function. In addition, communication barriers foster social withdrawal, emotional distress, and progressive isolation. Because social engagement acts as a potent protective factor against neurodegeneration, the social consequences of unaddressed auditory impairment substantially accelerate cognitive decline across diverse demographics.
To investigate these long-term clinical relationships, investigators utilized Taiwan's comprehensive National Health Insurance Research Database (NHIRD) between 2000 and 2015. The retrospective matched-cohort study enrolled a massive cohort of 208,570 individuals. Specifically, the researchers analyzed 41,714 patients with clinically diagnosed hearing loss against 166,856 matched controls. The investigators rigorously matched participants based on age, sex, and underlying chronic comorbidities. They followed the entire population for a mean duration of 7.82 years to trace incident neurocognitive outcomes accurately.
The study demonstrated that 18.67% of patients with hearing loss developed dementia, compared to only 14.10% in the control cohort. Furthermore, auditory deficit significantly advanced the timing of neurodegeneration. Patients in the hearing loss cohort developed dementia at a younger mean age than controls (69.95 years versus 70.31 years, p = 0.001). Moreover, the duration from baseline enrollment to initial dementia diagnosis was significantly shorter among individuals experiencing auditory loss (5.21 years versus 5.49 years, p < 0.001). These robust findings underscore the potent influence of sensory impairment on disease trajectories.
Crucially, the Taiwan cohort study revealed that middle-aged individuals face distinct vulnerability to sensory-associated neurodegeneration. Among adults aged 45 to 65 years, participants with hearing impairment exhibited a significantly higher likelihood of developing dementia than their normal-hearing peers (48.53% versus 47.94%, p = 0.03). This observation aligns closely with global evidence indicating that middle age represents the most critical window for sensory interventions. Intervening during midlife may preserve cognitive reserve before irreversible cerebral damage takes place.
Additionally, multivariate Cox proportional hazards regression models revealed elevated risks across diverse clinical dementia classifications. Patients with hearing loss exhibited significantly higher adjusted hazard ratios for Alzheimer's disease, vascular dementia, and other non-specific dementias. The sensory impairment did not merely correlate with isolated memory failure. Instead, it magnified broad-spectrum neurodegenerative vulnerability. Therefore, clinicians must recognize that peripheral auditory deficits compromise global brain resilience across multiple pathological pathways.
The study also illuminated critical vascular comorbidities that interconnect sensory impairment and cerebral deterioration. Patients diagnosed with hearing impairment displayed markedly higher rates of hyperlipidemia and ischemic stroke than matched controls. Because the microvasculature of the inner ear relies heavily on delicate labyrinthine perfusion, systemic vascular pathology frequently compromises both cochlear function and subcortical brain structures simultaneously.
Microvascular damage, endothelial dysfunction, and chronic atherosclerosis likely act as shared pathological drivers. Hypoperfusion in the stria vascularis parallels small vessel disease in subcortical white matter. Consequently, patients who develop sensory decline may already harbor silent cerebral small vessel disease. Addressing cardiovascular risk factors, managing systemic lipids, and maintaining vascular health represent essential clinical steps to protect both cochlear perfusion and long-term neurocognitive function.
These long-term findings demand a fundamental shift in routine preventive medicine. General practitioners, geriatricians, and otolaryngologists must proactively screen for auditory decline during regular health assessments, particularly for individuals entering midlife. Standardized pure-tone audiometry and validated whisper tests can identify subclinical hearing decline years before overt cognitive symptoms emerge.
Moreover, clinicians must advocate for early audiological rehabilitation. Providing timely acoustic amplification via modern digital hearing aids or cochlear implants restores peripheral input, mitigates cognitive overload, and prevents compensatory cortical reorganization. Promoting routine hearing protection, treating recurrent otological infections, and addressing coexisting hypertension or dyslipidemia will deliver synergistic neuroprotective benefits over decades of patient care.
Future research must clarify whether aggressive audiological correction directly alters neuropathological biomarkers in cerebrospinal fluid and neuroimaging. Randomized trials are currently tracking whether sensory restoration preserves hippocampal volume and reduces amyloid deposition over time. Meanwhile, health systems must integrate audiologists, neurologists, and primary care physicians into cohesive multidisciplinary teams.
Public health policies should prioritize accessible hearing health resources, subsidized amplification devices, and broad community awareness. In conclusion, untreated auditory loss is not an inevitable or benign consequence of aging. Because auditory pathways preserve vital brain integrity, early diagnosis and prompt correction of sensory impairment represent indispensable pillars of global dementia prevention.
Auditory impairment deprives the brain of vital acoustic stimuli, prompting temporal lobe atrophy and structural reorganization. Additionally, straining to decipher degraded sound signals exhausts valuable cognitive resources. This excessive cognitive load diverts neural capacity away from memory consolidation and executive functioning, while associated social isolation further accelerates neurodegeneration.
Yes, prospective evidence suggests that early audiological correction preserves long-term brain health. Using hearing aids or cochlear implants restores sensory input, reduces cognitive strain, and encourages active social engagement. Consequently, treating midlife hearing loss supports neural reserve and significantly slows the progression toward cognitive impairment.
Longitudinal cohort data confirm that auditory loss increases the hazard ratio for multiple dementia subtypes. These include Alzheimer's disease, vascular dementia, and mixed neurodegenerative conditions. The shared microvascular pathology, combined with sensory deprivation and chronic neuroinflammation, elevates systemic vulnerability across diverse cortical and subcortical structures.
Disclaimer: This content is for informational and educational purposes only. It is not intended to be a substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A nationwide 15-year follow-up cohort study of over 208,000 individuals demonstrates that hearing loss significantly increases the incidence of dementia, accelerates the age of onset, and correlates with higher vascular and neurodegenerative risks, highlighting the urgent need for early audiological screening.
2 months ago
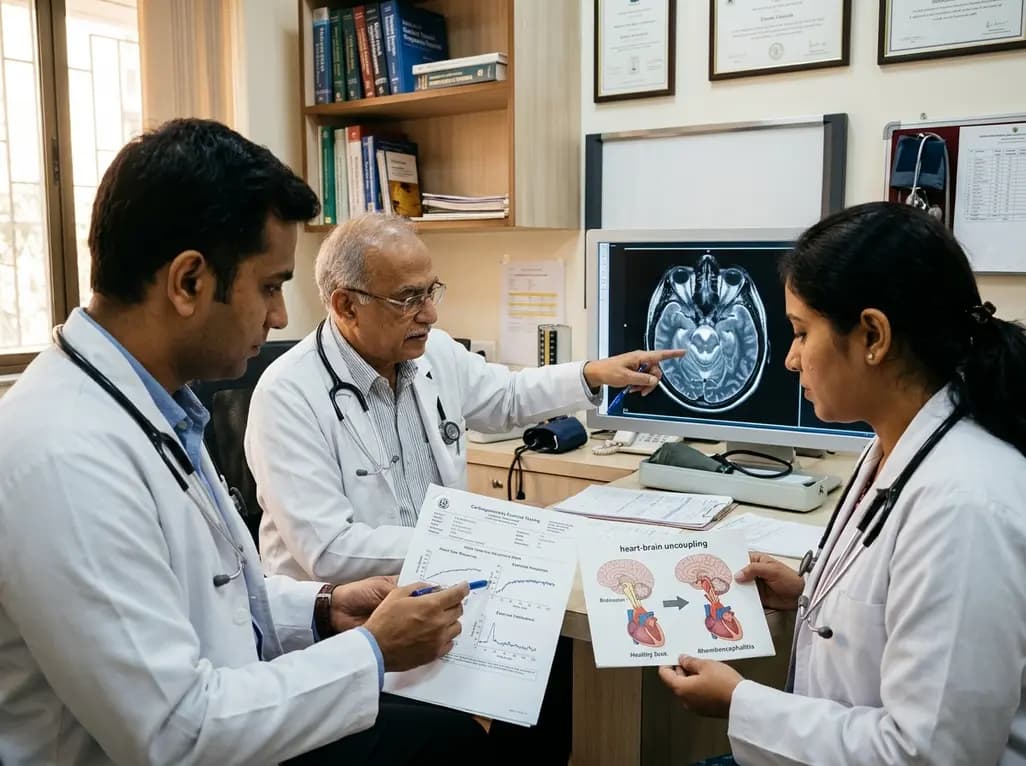
Central chronotropic incompetence is an underrecognized sequela of rhombencephalitis causing exertional dyspnea despite normal resting cardiac function. Cardiopulmonary exercise testing unmasks this heart-brain uncoupling, guiding rate-responsive pacing and targeted rehabilitation.
Today
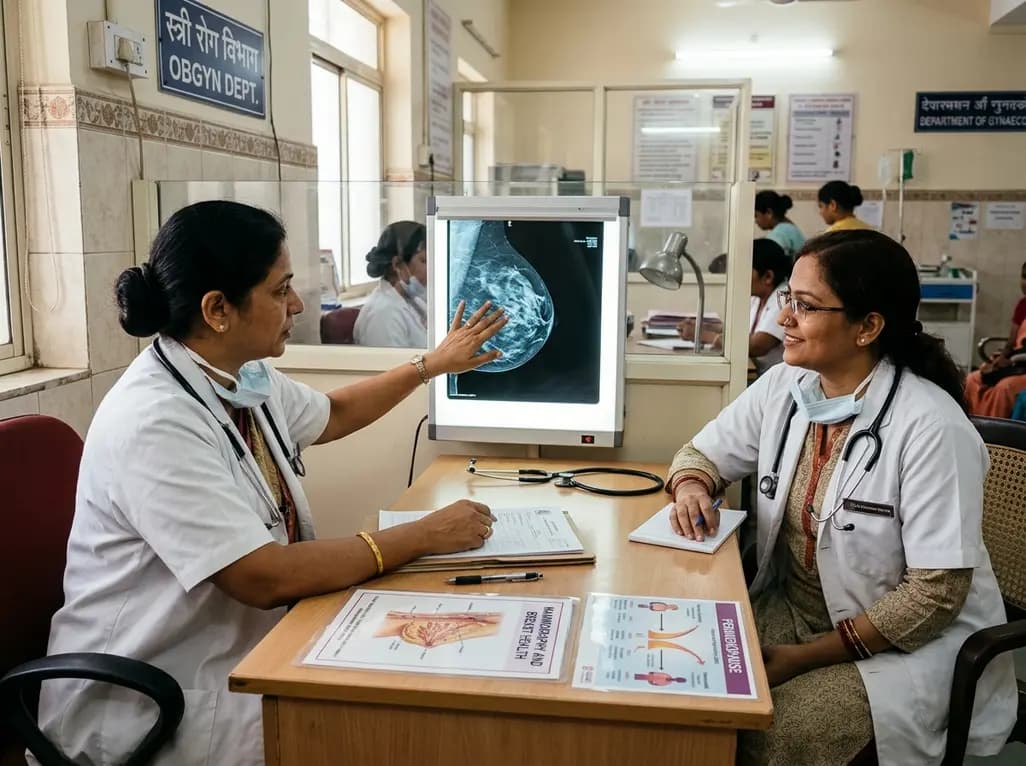
Perimenopause brings erratic hormonal surges and metabolic shifts that significantly affect breast tissue. This comprehensive clinical review examines benign breast conditions, cancer risk stratification, mammographic density challenges, and endocrine therapy transitions in midlife women.
Today
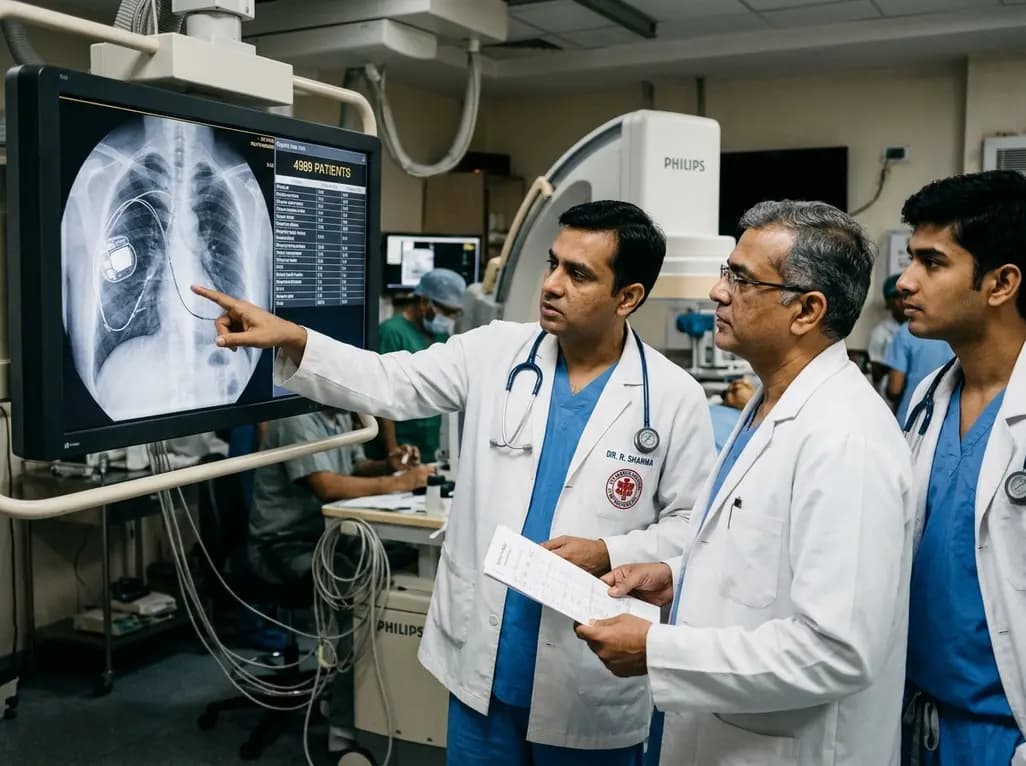
A registry study of 4,989 patients evaluates transvenous lead extraction for right-sided cardiac devices. Despite longer dwell times and older leads, right-sided extractions achieve high procedural success and comparable safety to left-sided approaches.
Today
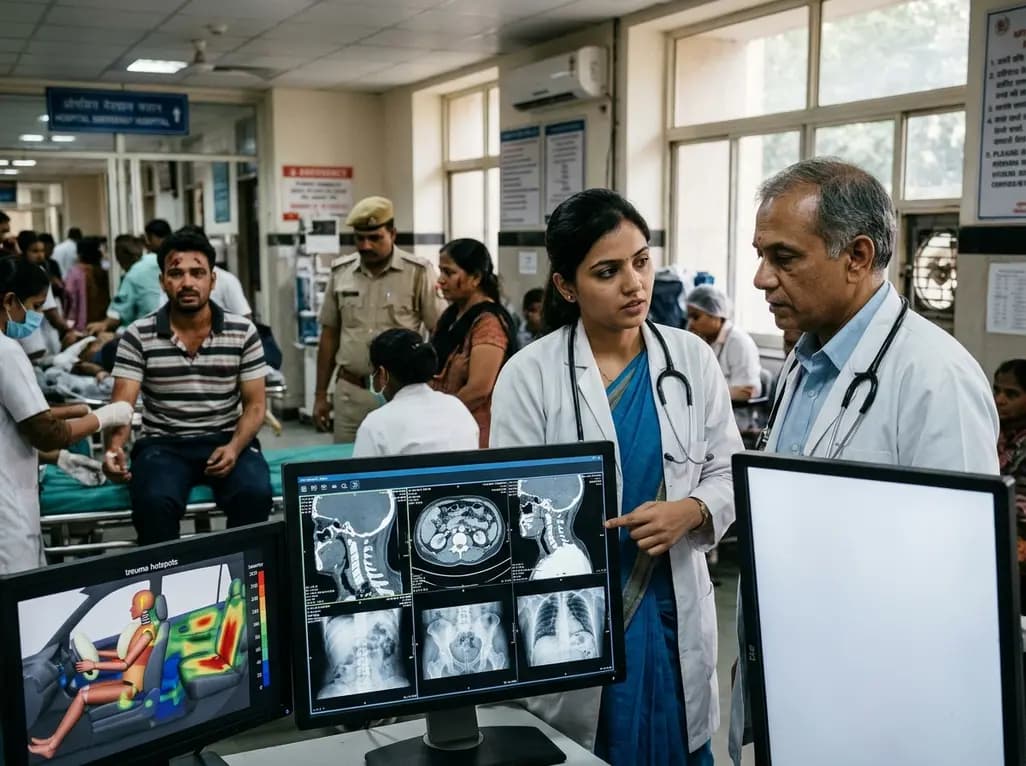
Recent crash analyses demonstrate significant variations in traffic injury severity across vehicle seating positions. Electric vehicle passengers face disproportionately higher trauma risks than drivers, particularly during airbag deployments, demanding adapted emergency assessment and clinical vigilance.
Today

Understand the causal role of Lipoprotein(a) in cardiovascular disease, why international guidelines recommend once-in-a-lifetime molar testing, and the clinical implications of recent phase 3 RNA outcome trials.
Today
