

Loading, please wait...
Loading, please wait...

Postoperative pulmonary complications represent a major source of surgical morbidity following major abdominal procedures. Clinicians frequently encounter severe respiratory compromise during minimally invasive pelvic interventions. Consequently, adopting advanced ventilatory techniques has emerged as a cornerstone of perioperative medicine. A recent breakthrough randomised clinical trial highlights the potential of EIT-guided PEEP optimisation in preventing respiratory adverse events. By offering bedside visualisation of ventilation distribution, electrical impedance tomography addresses patient-specific physiology. Therefore, this technological evolution transforms conventional intraoperative care into a tailored protective strategy for vulnerable surgical cohorts.
Laparoscopic colorectal resections inherently introduce severe biomechanical stress on respiratory mechanics. During these interventions, insufflation of carbon dioxide creates elevated intra-abdominal pressure that shifts the diaphragm cephalad. In addition, steep Trendelenburg positioning further compounds this cranial displacement by pushing heavy abdominal viscera against the thoracic cavity. Consequently, functional residual capacity drops dramatically, leading to widespread dependent atelectasis and ventilation-perfusion mismatch.
Under these altered mechanics, standard mechanical ventilation frequently delivers uneven tidal volumes. Dorsal lung regions experience progressive collapse, whereas non-dependent ventral zones sustain repetitive hyperinflation. This cyclic opening and closing of delicate alveolar units induces mechanical shearing injury, known as atelectotrauma. Concurrently, regional strain triggers a local pulmonary inflammatory response and elevates systemic biomarkers of epithelial lung injury.
Furthermore, general anaesthesia abolishes normal muscular tone, exacerbating diaphragmatic cephalad displacement. Conventional approaches typically apply arbitrary airway pressures to counteract these pathological shifts. However, standard ventilatory presets often fail because they ignore the unique anatomical and compliance profiles of individual patients. As a result, patients with pre-existing risk factors frequently suffer postoperative hypoxemia, pneumonia, and prolonged oxygen dependency.
Electrical impedance tomography functions as a dynamic, non-invasive imaging modality that captures cross-sectional variations in thoracic electrical impedance. A specialized electrode belt wraps around the chest wall, delivering imperceptible electrical currents to track breath-by-breath ventilation patterns. Accordingly, anaesthesiologists can visualise aeration changes across distinct functional lung quadrants in real time.
Applying EIT-guided PEEP optimisation allows clinicians to move beyond standardized respiratory recipes. During incremental or decremental PEEP titration maneuvers, the monitor quantifies both regional lung collapse and alveolar overdistension simultaneously. Clinicians can readily observe the precise airway pressure where dependent alveoli recruit without simultaneously causing excessive hyperdistension of non-dependent zones. Consequently, the monitoring software calculates an optimal compromise point tailored to the patient's instantaneous chest wall compliance.
Moreover, this approach minimizes regional ventilation inhomogeneity under extreme operative tilts. Unlike intermittent arterial blood gas analysis, impedance imaging responds immediately to changes in surgical retractors or abdominal desufflation. Therefore, anaesthesiologists can dynamically titrate positive end-expiratory pressure throughout prolonged laparoscopic resections. By maintaining functional lung volume without inducing hemodynamic compromise, personalised titration prevents both atelectasis and barotrauma.
The landmark clinical trial by Wang and colleagues rigorously assessed whether personalised titration improves meaningful postoperative outcomes. The trial enrolled 117 adult surgical patients undergoing elective laparoscopic colorectal procedures. Notably, researchers focused exclusively on individuals demonstrating intermediate to high respiratory risk, established using an ARISCAT score of 26 or greater.
The clinical investigators randomly allocated participants to either dynamic impedance-guided titration or conventional mechanical ventilation utilizing a fixed PEEP of 5 cm H2O. Primary outcome adjudication involved a blinded multidisciplinary committee using standardized diagnostic metrics to evaluate pulmonary complications within 30 days.
The trial revealed compelling differences in respiratory outcomes. Patients who received tailored ventilation exhibited significantly lower driving pressures, recording median levels of 16 cm H2O compared to 19 cm H2O in the control cohort. Furthermore, dynamic lung compliance improved remarkably in the titration arm without causing adverse cardiovascular instability. Most importantly, the intervention significantly reduced the 30-day incidence of composite pulmonary complications. Adjudicated rates dropped substantially among titrated patients compared to those managed with standard low end-expiratory pressure. Thus, physiological optimisation directly translated into demonstrable perioperative protection.
Reducing driving pressure represents the central physiological mechanism that explains the trial's positive clinical results. Driving pressure directly reflects the cyclical strain exerted on aerated functional lung compartments during tidal breathing. When pneumoperitoneum and surgical tilting severely diminish the functional lung volume, standard tidal volumes overstretch the small remaining aerated baby lung. Consequently, maintaining a high driving pressure causes repetitive mechanical strain and alveolar capillary disruption.
Individualised positive pressure counteracts this pathological cascade by restoring functional residual capacity. Because personalised PEEP recruits collapsed dependent lung tissue, it substantially expands the functional lung volume available for ventilation. As a result, the respiratory system accommodates identical tidal volumes under considerably lower dynamic driving pressures.
Moreover, lower driving pressures mitigate pulmonary vascular shear stress and attenuate the release of pro-inflammatory cytokines into the systemic circulation. This lung-protective effect prevents subclinical microatelectasis from progressing into clinical tracheobronchial infections or overt pneumonia. Additionally, avoiding severe cyclic alveolar collapse preserves local surfactant integrity and mucosal clearance mechanisms. Therefore, impedance-guided pressure titration maintains structural lung stability, directly shielding vulnerable patients from secondary postoperative respiratory failure.
Implementing individualised ventilation protocols holds immense clinical relevance for anaesthesiologists managing high-risk surgical candidates. Traditionally, clinical teams have relied on fixed moderate PEEP or static compliance tables to guide ventilatory settings. However, fixed empirical strategies fail to account for the substantial heterogeneity in chest wall compliance observed across different patient habitus.
In contrast, bedside impedance tracking provides immediate actionable data that eliminates guesswork during complex pelvic reconstructions. Operating room teams can rapidly conduct an intraoperative decremental PEEP titration following the establishment of pneumoperitoneum and Trendelenburg positioning. Clinicians then set the definitive end-expiratory pressure at the intersection of minimal collapse and minimal hyperdistension.
Furthermore, risk stratification tools such as the ARISCAT score allow clinicians to select patients who will derive the greatest therapeutic benefit. Resource-conscious departments can prioritize complex laparoscopic colorectal cases, geriatric individuals, and patients with pre-existing pulmonary comorbidities for advanced monitoring. In addition, multi-professional operating theatre teams can standardise recruitment protocols and titration algorithms to ensure reproducibility. Ultimately, incorporating real-time electrical impedance imaging empowers clinicians to deliver precise, proactive respiratory care throughout prolonged operative interventions.
In Indian healthcare ecosystems, minimally invasive colorectal surgery is expanding rapidly across tertiary hospitals and oncology centres. However, Indian clinicians frequently encounter unique perioperative challenges, including higher prevalences of untreated chronic respiratory illnesses and post-tubercular structural lung changes. Consequently, Indian patients presenting for prolonged laparoscopic procedures carry an elevated baseline risk for adverse respiratory complications.
Although electrical impedance tomography hardware requires a capital investment, its bedside utility offers substantial downstream economic savings. Preventing severe postoperative respiratory events significantly decreases intensive care unit admissions, supplemental oxygen dependence, and prolonged hospital stays. Therefore, implementing targeted impedance monitoring in high-volume tertiary referral hospitals aligns well with hospital quality improvement and enhanced recovery initiatives.
Nevertheless, widespread adoption across district and secondary healthcare centres requires structured simulation training and interdisciplinary protocols. Anaesthesia societies in India can play a pivotal role by incorporating dynamic lung imaging into postgraduate curricula and clinical practice guidelines. Looking forward, future multicentric studies will likely investigate simplified automated algorithms and assess cost-effectiveness across diverse operative disciplines. Embracing individualized respiratory mechanics ensures that cutting-edge perioperative medicine reaches diverse surgical populations safely.
Conventional intraoperative ventilation typically applies an empirical, fixed positive end-expiratory pressure, often set at 5 cm H2O for every patient. In contrast, EIT-guided PEEP optimisation utilizes real-time thoracic bioimpedance imaging to evaluate breath-by-breath regional ventilation. This dynamic bedside assessment identifies the unique pressure level that simultaneously minimizes dependent alveolar collapse and non-dependent hyperdistension, tailoring ventilation specifically to individual lung mechanics and surgical positioning.
Patients undergoing major laparoscopic or robotic procedures involving steep Trendelenburg positioning gain the greatest benefit from personalised titration. Furthermore, individuals with intermediate to high pulmonary risk scores, such as an ARISCAT score of 26 or greater, experience substantial risk reduction. Elderly patients, individuals with obesity, and patients suffering from underlying chronic obstructive pulmonary disease or previous pulmonary infections derive significant protection from tailored respiratory mechanics.
Yes, driving pressure serves as an exceptionally sensitive metric of cyclic mechanical lung strain during general anaesthesia. It represents the ratio between delivered tidal volume and functional respiratory compliance. Lower driving pressures indicate that tidal ventilation distributes evenly across recruited lung units without causing excessive alveolar stretch. Consequently, reducing intraoperative driving pressure directly correlates with decreased inflammatory biomarker release and lower rates of postoperative pulmonary complications.
Disclaimer: This content is for informational and educational purposes only. It is not intended to substitute for professional medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition or treatment. Refer to the latest local and national guidelines for clinical practice.
References
Wang TH et al. Effect of electrical impedance tomography-guided positive end-expiratory pressure optimisation on postoperative pulmonary complications in laparoscopic colorectal surgery: a randomised controlled trial. Br J Anaesth. 2026 Oct 20. doi: undefined. PMID: 42901858.
Young CC, Harris EM, Palmer C, et al. Lung-protective ventilation in the operating room: a review of physiology and practice. Anesth Analg. 2019;129(4):1029-1041.
Blankman P, Hasan D, van Mourik MS, Gommers D. Electrical impedance tomography for the assessment of positive end-expiratory pressure. J Clin Monit Comput. 2016;30(6):753-764.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A randomised controlled trial demonstrates that EIT-guided PEEP optimisation significantly lowers driving pressure and reduces 30-day postoperative pulmonary complications in intermediate-to-high-risk patients undergoing laparoscopic colorectal surgery under steep Trendelenburg positioning.
Today

As millions adopt GLP-1 receptor agonists, patients frequently combine unverified dietary supplements to mitigate gastrointestinal side effects. Clinicians must understand delayed gastric absorption, supplement quality risks, and evidence-based nutrition strategies to protect patient outcomes during medical weight loss.
Today

A novel high-permeation vesicle-in-gel platform enhances transdermal fulvestrant delivery, achieving sustained release, robust intradermal retention, and superior antitumor efficacy in breast cancer models while circumventing the drawbacks of painful intramuscular depot injections.
Today

A landmark ten-year WHO report reveals how socioeconomic status, geography, and gender disparities profoundly aggravate chronic disease risks, diagnosis delays, and therapeutic outcomes globally. Discover actionable primary care strategies to bridge screening divides and optimize vulnerable patient management.
Today
A recent single-institution analysis identifies advanced patient age and progressive systemic disease as primary negative prognostic factors for five-year survival in chondrosarcoma, underscoring the urgent necessity of precise risk stratification, clear surgical margins, and dedicated oncologic follow-up.
Today
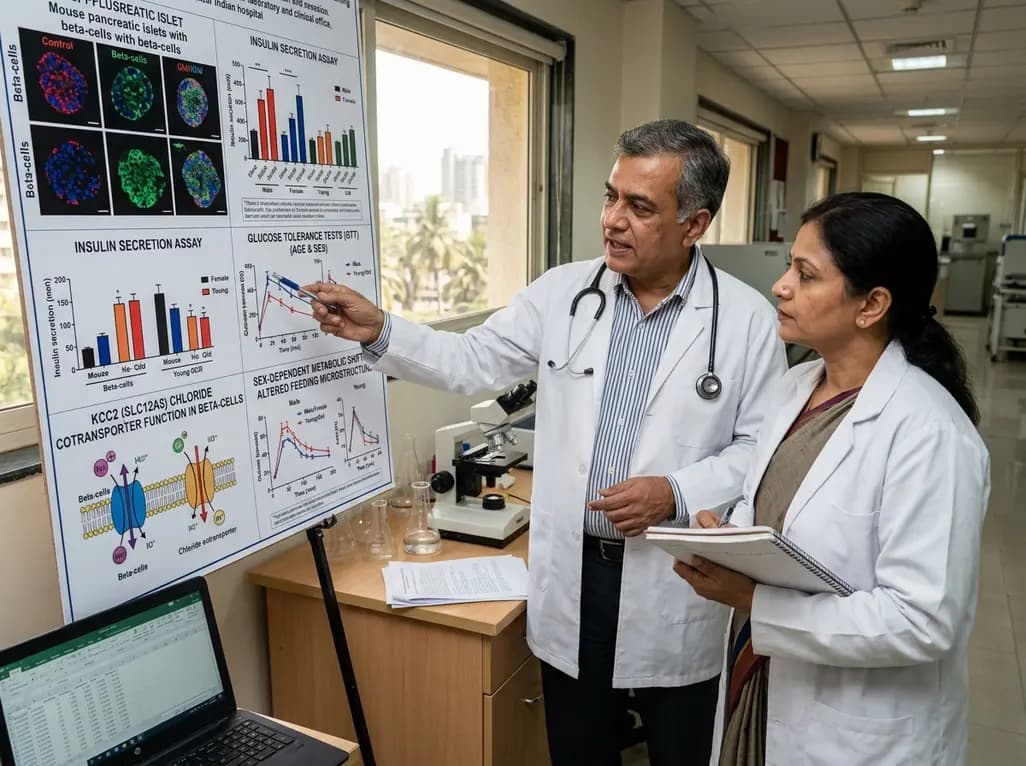
Targeted deletion of the chloride cotransporter Kcc2 (Slc12a5) in pancreatic beta-cells triggers distinct sex- and age-dependent metabolic shifts, including altered feeding microstructure, enhanced insulin release in young mice, and modified glucose tolerance, highlighting chloride's role in islet biology.
Today
