

Loading, please wait...
Loading, please wait...
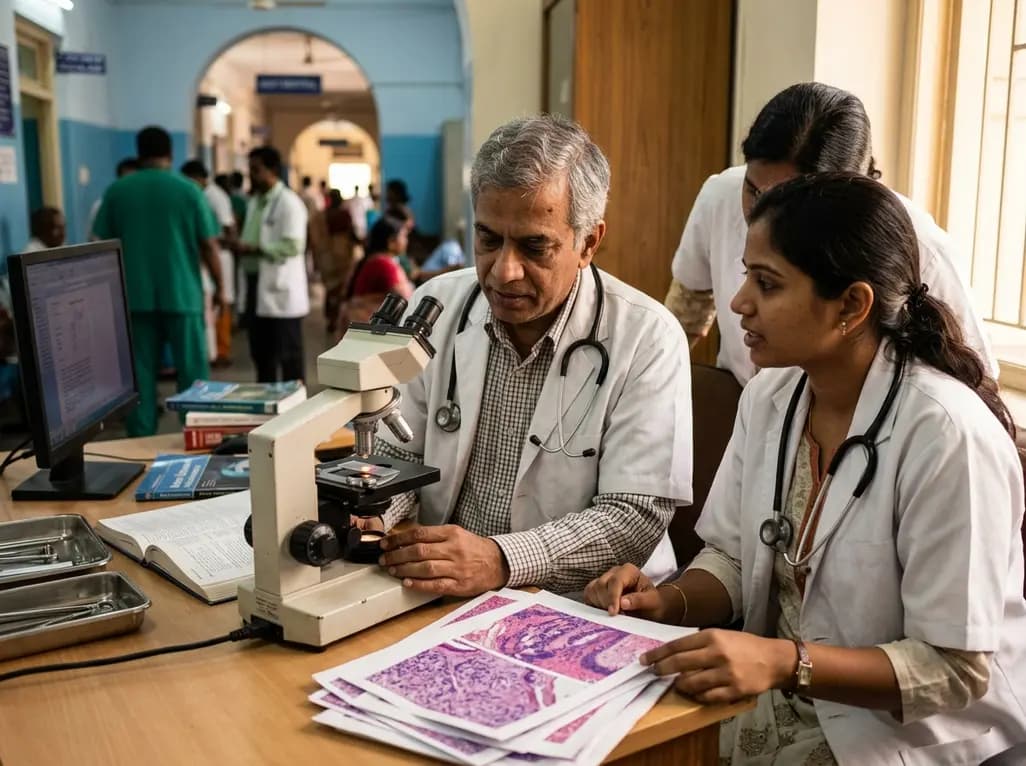
Oculoplastic surgeons regularly utilize conjunctivomüllerectomy ptosis surgery to correct mild-to-moderate aponeurotic blepharoptosis. This posterior approach offers predictable cosmetic elevation and avoids cutaneous scars. However, clinicians still debate the exact mechanical pathways that drive postoperative eyelid elevation. Recent histopathological investigations have provided clarity regarding these underlying physiological processes. Specifically, new histological analyses reveal surprising discrepancies between resected tissues and clinical success. Understanding these tissue characteristics empowers surgeons to refine techniques, anticipate clinical responses, and optimize patient outcomes.
Historically, surgeons believed that conjunctivomüllerectomy ptosis surgery elevated the eyelid primarily by shortening Müller's muscle. In 1975, Putterman introduced this posterior approach as a tarsus-sparing modification of previous techniques. The procedure specifically targets patients who demonstrate preserved levator function and positive phenylephrine testing. During the standard intervention, the surgeon clamps and excises conjunctival and muscular tissue above the superior tarsus. Consequently, the superior tarsal border advances toward the Whitnall ligament complex.
However, recent clinical evidence challenges the classical assumption that muscular resection alone dictates clinical success. Investigators prospectively evaluated fifteen eyes from fourteen consecutive patients with involutional ptosis. Following a modified Putterman intervention, the surgical team measured clinical elevation using margin reflex distance 1. Before surgery, patients presented with a mean distance of 1.05 millimeters. Postoperatively, the mean margin reflex distance increased significantly to 3.77 millimeters. Therefore, the procedure reliably restored functional eyelid height and achieved excellent symmetry. Nevertheless, comprehensive histopathological evaluation of excised tissue specimens showed profound variations that contradicted traditional surgical teaching.
To analyze tissue composition accurately, researchers stained surgical specimens with smooth muscle actin, desmin, and h-caldesmon. Surprisingly, pathologists identified no Müller's muscle fibres in thirty-three percent of excised specimens. Furthermore, in specimens containing identifiable smooth muscle, the mean muscle proportion reached only twenty-nine percent. These unexpected findings demonstrate that substantial muscular resection is not mandatory for successful elevation.
Moreover, the total amount of resected smooth muscle did not correlate with postoperative margin reflex distance improvements. Patients without detectable muscle tissue attained eyelid elevations comparable to those with abundant smooth muscle. Consequently, mechanical shortening of the posterior lamella appears to provide the primary lifting vector. When the surgeon plicates the conjunctival and subconjunctival tissues, the posterior layer shortens directly. Therefore, posterior lamellar tightening transmits mechanical tension to the tarsal plate independently of active muscular resection. In addition, the surgical clamp may induce mechanical plication of deeper levator structures without requiring direct anatomical excision. These histological revelations provide a compelling mechanistic explanation for surgical success in patients lacking resected muscle.
In addition to muscular evaluation, investigators analyzed inflammatory markers within resected conjunctival tissues. Pathologists assessed chronic inflammation by counting CD138 and CD38 positive plasma cells per high-power field. Notably, eighty-seven percent of the surgical specimens exhibited distinct chronic inflammatory infiltrates. This high prevalence suggests that chronic subclinical inflammation represents a fundamental feature of the involutional eyelid environment.
Furthermore, chronic inflammation may actively facilitate surgical tightening and long-term structural stabilization. When surgical manipulation traumatizes inflamed posterior tissues, a vigorous fibroblastic wound healing cascade begins. Subsequently, myofibroblastic activation and collagen deposition induce contracture within the posterior lamella. Therefore, postoperative cicatricial shortening might reinforce vertical advancement of the eyelid margin over time. However, excessive inflammation could theoretically increase the risk of conjunctival irritation. Fortunately, none of the study participants developed restrictive cicatricial complications or persistent discomfort during follow-up. Accordingly, surgeons should recognize that preexisting chronic inflammation may contribute constructively to mechanical stability after posterior resection. This finding underscores the complex interplay between histological tissue properties and surgical biomechanics.
A critical safety concern during posterior approach ptosis repair involves accidental damage to adjacent anterior structures. Specifically, surgeons seek to avoid inadvertent resection of the levator aponeurosis or superior rectus muscle fibres. In this prospective histological series, pathologists detected neither levator aponeurotic tissue nor skeletal muscle fibres in any surgical specimen. Consequently, these findings confirm the exceptional anatomical precision and safety profile of the modified Putterman clamp technique.
Moreover, preserving the integrity of the levator aponeurosis prevents postoperative eyelid lag and irregular lid contour. Because the aponeurosis remains uninjured, the primary dynamic retractor retains its native contractile capacity. In contrast, anterior approach ptosis repairs require extensive dissection across the orbicularis muscle and orbital septum. Such anterior dissections often introduce contour abnormalities, asymmetric eyelid creases, or dynamic lagophthalmos. Therefore, posterior conjunctival resection provides a much safer alternative for patients who respond favourably to preoperative adrenergic stimulation. Furthermore, isolating surgical trauma strictly to the conjunctiva and Müller's muscle preserves normal eyelid architecture. Ultimately, these structural observations reassure oculoplastic surgeons regarding the anatomical safety of posterior resection.
These clinical and histological insights offer substantial practical benefits for ophthalmic surgeons managing eyelid ptosis. First, clinicians must recognize that a successful outcome does not depend on capturing dense smooth muscle bundles within the surgical clamp. Therefore, surgeons should adhere strictly to standardized nomograms rather than attempting aggressive posterior tissue dissection. Overzealous dissection risks damage to the accessory lacrimal glands of Wolfring or Krause, potentially exacerbating ocular surface disease.
Second, the study reinforces the predictive reliability of the preoperative phenylephrine test. Although phenylephrine stimulates sympathetic alpha-1 receptors on Müller's muscle, clinical response reflects posterior lamellar responsiveness as a whole. Consequently, an affirmative test confirms that posterior shortening will achieve therapeutic eyelid elevation. In addition, the predictable outcome of conjunctivomüllerectomy minimizes surgical revision rates compared to traditional external levator advancement. Postoperative recovery remains rapid, and patients experience minimal ecchymosis and virtually no visible external scars. Accordingly, surgeons can confidently recommend this posterior approach for mild-to-moderate aponeurotic ptosis in elderly populations. By integrating these scientific insights, clinicians improve patient selection, optimize operative precision, and ensure reproducible cosmetic outcomes.
The procedure elevates the eyelid primarily through mechanical posterior lamellar shortening and indirect plication of the levator aponeurosis. Even when excised specimens contain little or no smooth muscle, clamping and suturing the conjunctiva creates structural tension. Furthermore, postoperative wound healing and myofibroblast contracture tighten the posterior tissues. Consequently, the shortened posterior layer pulls the superior tarsus upward, restoring appropriate eyelid height independently of direct muscle excision.
The phenylephrine test evaluates the dynamic reserve and responsiveness of the upper eyelid retractor complex. When phenylephrine eyedrops stimulate sympathetic alpha-adrenergic receptors, the eyelid elevates into a desirable aesthetic position. Consequently, this pharmacological response confirms that posterior lamellar manipulation will achieve satisfactory cosmetic elevation. Furthermore, the test helps surgeons calculate the precise resection height required, ensuring reproducible surgical outcomes and minimizing the risk of postoperative undercorrection.
Chronic subclinical inflammation is highly prevalent in ptotic eyelids, appearing in most surgical specimens. Following conjunctivomüllerectomy, this preexisting inflammatory state stimulates active fibroblast proliferation and robust collagen deposition. Subsequently, organized tissue contraction reinforces mechanical tightening of the posterior lamella over time. Therefore, chronic inflammation contributes constructively to lasting eyelid elevation without causing symptomatic cicatricial complications, provided the surgeon adheres strictly to careful tissue-sparing surgical techniques.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A prospective study evaluates conjunctivomüllerectomy ptosis surgery, demonstrating that significant eyelid elevation occurs independently of consistent Müller muscle resection. Histopathology shows chronic inflammation and absence of levator aponeurosis, clarifying functional anatomical mechanisms.
Today

A longitudinal PATH study analysis evaluates flavored e-cigarette abstinence across youth, young adults, and older adults, demonstrating the predominance of sweet flavors and revealing age-stratified quitting outcomes with vital implications for clinical counseling and regulatory policy.
Today
A nationwide review reveals that gastrointestinal and urological tract injuries occur in 233 per 100,000 cesarean deliveries, causing elevated ICU admission and maternal mortality. Prior cesarean delivery triples urological risk, underscoring the critical consulting role of general surgeons.
Today

A nationwide Swedish registry study evaluating insulin degludec versus glargine reveals equivalent MACE in trial-eligible patients, yet shows significantly lower all-cause mortality across both trial-eligible and routine practice populations, along with reduced cardiovascular events in real-world cohorts.
Today

A systematic review and meta-analysis of 8 RCTs evaluated bipolar versus monopolar electrocautery in primary total hip and knee arthroplasty. Pooled data revealed no significant differences in haemoglobin drop, blood loss, or length of stay, concluding that routine bipolar electrocautery is not supported.
Today

A critical review evaluates whether starch-polyphenol complexes meet structural and metabolic criteria to qualify as type 5 resistant starch. The proposed tiered evidence framework distinguishes true inclusion complexes from simple mixtures, clarifying mechanisms for glycemic modulation and gut fermentation.
Today
