

Loading, please wait...
Loading, please wait...
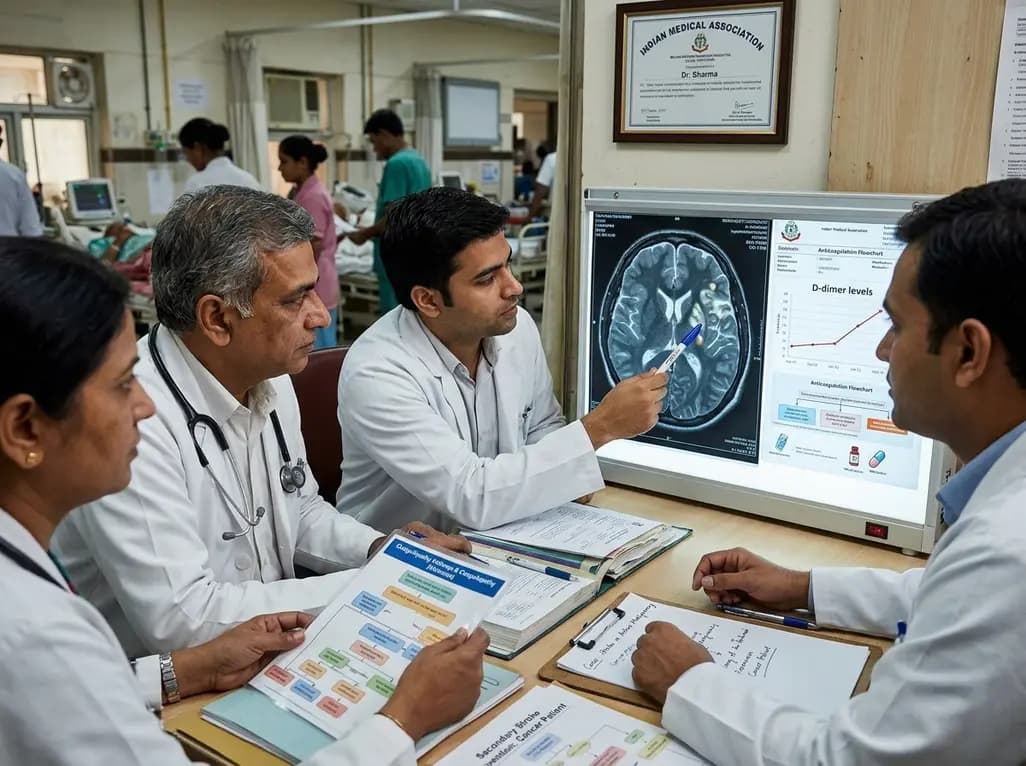
Stroke represents the second most common neurological complication among patients with cancer, trailing only direct central nervous system metastases. Clinicians frequently encounter embolic cerebral infarctions in oncological settings, yet traditional vascular risk factors often fail to explain these acute events. Emerging clinical evidence identifies cancer-associated coagulopathy stroke as a distinct and aggressive clinical entity. This systemic prothrombotic state directly drives recurrent thrombosis, contributing to high disability and mortality. A comprehensive systematic review published in the Journal of Neurology synthesized evidence from 82 clinical studies to characterize this syndrome. Understanding its biological mechanisms, neuroimaging signatures, and antithrombotic dilemmas is essential for modern medical practice.
Active malignancy complicates approximately 5% to 10% of all acute ischemic stroke presentations. Furthermore, cancer prevalence rises substantially among patients presenting with embolic stroke of undetermined source. In nearly 5% of these cryptogenic cases, the ischemic event precedes the formal cancer diagnosis by several months. Therefore, an unexplained ischemic infarct can serve as the earliest clinical harbinger of an occult malignancy.
Among cancer patients who suffer cerebral ischemia, hypercoagulability accounts for nearly 40% of all documented cases. Traditional vascular mechanisms, including large-artery atherosclerosis and cardioembolism from atrial fibrillation, occur far less frequently in this specific cohort. Additionally, the temporal pattern of thromboembolism shows a predictable vulnerability window. Patients face the highest risk of stroke within the initial six months following their cancer diagnosis.
Consequently, advanced tumor stage strongly correlates with thromboembolic complications. Metastatic disease appears in the majority of affected patients, reflecting high systemic tumor burden. Histologically, adenocarcinomas demonstrate the strongest association with coagulopathy-related stroke, particularly primary malignancies of the lung and pancreas. Recognizing these epidemiological patterns enables clinicians to suspect malignancy promptly during acute stroke workups.
The pathophysiology of malignancy-associated thrombosis extends beyond conventional stasis or endothelial injury. Instead, tumor cells actively induce a profound prothrombotic state through multifaceted molecular pathways. Specifically, neoplastic cells synthesize and release active tissue factor into circulation via procoagulant extracellular vesicles. These microvesicles trigger the extrinsic coagulation cascade, generating excessive thrombin and downstream fibrin deposition.
Moreover, mucin-producing adenocarcinomas shed circulating mucins that interact directly with selectins on host platelets and leukocytes. This abnormal interaction prompts rapid platelet activation and widespread microvascular aggregation. Concurrently, systemic inflammation activates host neutrophils, triggering the formation of neutrophil extracellular traps. These web-like chromatin structures provide an intravascular scaffold that accelerates thrombin generation and binds platelets securely.
As a result, thrombi formed under cancer-associated coagulopathy differ fundamentally from ordinary atherothrombotic clots. Histological analyses confirm that these emboli are markedly platelet-rich and contain sparse erythrocytes. Furthermore, nonbacterial thrombotic endocarditis, or marantic endocarditis, frequently deposits sterile vegetations onto cardiac valves. These fragile vegetations easily fragment under systemic arterial pressures. Consequently, platelet-fibrin microemboli shower the cerebral circulation, precipitating sudden multi-vessel occlusive events.
Brain imaging plays a pivotal diagnostic role in identifying cancer-related hypercoagulability. Diffusion-weighted magnetic resonance imaging frequently reveals multiple acute ischemic lesions scattered across multiple independent vascular territories. In fact, microembolic dispersion appears in up to 78% of these patients, and silent prior infarctions occur in nearly half.
Most importantly, the radiographic hallmark of this condition is the classic three territories sign. This neuroimaging pattern features simultaneous acute ischemic infarctions distributed across both anterior circulations and the posterior circulation. In the absence of acute infective endocarditis, this sign exhibits remarkable specificity for cancer-mediated thromboembolism. Indeed, approximately 75% of patients exhibiting cryptogenic three-territory infarctions harbor an underlying active malignancy.
Furthermore, these ischemic lesions show a distinct anatomical predilection for cortical and subcortical border-zone territories. Cerebellar hemispheres and the corpus callosum also frequently sustain ischemic injury. Because these thrombi fragment easily, endovascular thrombectomy operators often observe multiple distal branch occlusions during interventional procedures. Rapid identification of these diffuse multi-territory lesions should prompt clinicians to pursue an immediate oncological and coagulopathy workup.
Laboratory biomarkers provide essential clues for diagnosing cancer-induced coagulopathy and evaluating patient prognosis. Among available serum assays, D-dimer stands out as the most reliable and clinically informative biomarker. Markedly elevated D-dimer levels consistently correlate with stroke recurrence, overall tumor burden, and short-term mortality. Moreover, persistently elevated D-dimer titers following the initiation of anticoagulation strongly predict early neurological deterioration.
In addition to D-dimer, other inflammatory and coagulation biomarkers offer supportive diagnostic value. Markedly elevated C-reactive protein levels above 20 mg/L and plasma fibrinogen levels surpassing 600 mg/dL strongly suggest an occult malignancy in cryptogenic stroke. Similarly, elevated cancer antigen 125 and a neutrophil-to-lymphocyte ratio exceeding 15 reflect severe systemic thromboinflammation.
Nevertheless, clinicians must recognize that nonspecific inflammatory markers cannot confirm coagulopathy alone. For example, transcranial Doppler ultrasonography frequently detects circulating microembolic signals in nearly half of tested patients. While these signals confirm ongoing intravascular embolization, their presence lacks histological specificity. Clinicians should therefore integrate elevated D-dimer levels, comprehensive echocardiography to exclude nonbacterial endocarditis, and validated scoring tools during initial assessments.
Secondary stroke prevention in cancer-associated coagulopathy presents exceptional therapeutic complexity. Clinicians must balance severe recurrent thrombotic risks against substantial systemic bleeding tendencies. Currently, low-molecular-weight heparin and direct oral anticoagulants serve as the primary therapeutic options for secondary prevention. Historically, low-molecular-weight heparin remained the preferred agent due to its predictable pharmacokinetics and proven ability to suppress tissue factor activity.
However, recent real-world data demonstrate growing reliance on direct oral anticoagulants because of their oral administration and improved patient adherence. Despite these advantages, clinical trials indicate that direct oral anticoagulants may carry higher gastrointestinal bleeding risks in patients with mucosal gastrointestinal tumors. Furthermore, some patients continue to experience recurrent ischemic strokes while receiving direct oral anticoagulants, necessitating transition back to parenteral heparin formulations.
Regardless of the chosen regimen, the overall prognosis for these patients remains concerningly poor. Thirty-day mortality rates range between 25% and 50%, driven jointly by aggressive malignancy progression and recurrent multi-organ thromboembolism. Additionally, stroke recurrence occurs early and frequently in this vulnerable cohort. Consequently, multidisciplinary collaboration between neurologists, hematologists, and oncologists is essential to tailor anticoagulation, monitor biomarker trajectories, and optimize patient outcomes.
The three territories sign is an MRI finding characterized by simultaneous acute ischemic infarcts involving three separate vascular territories across both anterior and posterior cerebral circulations. Excluding infective endocarditis, this pattern strongly indicates cancer-associated hypercoagulability, with roughly 75% of unexplained cases linked to an underlying malignant neoplasm.
D-dimer is the most consistent biomarker predicting stroke recurrence, tumor burden, and mortality in cancer-associated coagulopathy. Persistently elevated or increasing D-dimer levels despite therapeutic anticoagulation indicate ongoing intravascular clot formation. Monitoring these levels helps clinicians assess antithrombotic efficacy and make timely therapeutic adjustments to prevent recurrent thromboembolic events.
Both low-molecular-weight heparin and direct oral anticoagulants effectively prevent recurrent thrombosis in cancer patients. Low-molecular-weight heparin provides rapid reversibility and suppresses tumor procoagulant mechanisms effectively. Conversely, direct oral anticoagulants offer oral convenience but may increase gastrointestinal bleeding risks in luminal malignancies, requiring individualized antithrombotic therapy selection.
Disclaimer: This content is for informational and educational purposes only and does not substitute for professional medical advice, diagnosis, or treatment. Always consult a qualified healthcare provider for specific clinical decisions. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A systematic review examines stroke secondary to cancer-associated coagulopathy, highlighting unique imaging features like the three territories sign, elevated D-dimer dynamics, and complex anticoagulation strategies in patients with active malignancy.
last month

A pioneering clinical trial across 200 general practices in England evaluates cutting-edge blood tests to detect vague abdominal malignancies earlier. By combining artificial intelligence with protein biomarker profiling, clinicians aim to triage high-risk patients rapidly and improve long-term survival.
Today

A preclinical study reveals that cinnamic acid counters D-galactose-induced premature ovarian failure in mice. By enhancing total antioxidant capacity and upregulating protective genes like Nrf2 and Foxo3a, cinnamic acid improved estrous cyclicity and follicular reserve, offering new insights into ovarian health.
Today

A systematic review of 18 studies reveals very low certainty evidence for cardiac autonomic modulation following intermittent normobaric hypoxia, showing insufficient data to confirm reproducible changes in heart rate variability or baroreflex sensitivity.
Today

An 8-week functional restoration program provides sustained psychological benefits at six-month follow-up for workers' compensation patients. The multidisciplinary intervention significantly improved pain self-efficacy, reduced anxiety and depression, and progressively resolved chronic insomnia severity.
Today

A multinational study of 2,573 medullary thyroid cancer patients refines AJCC TNM-8 staging, proposing N1c for level VII nodes and a new I-IVB schema for better survival stratification.
Today
