

Loading, please wait...
Loading, please wait...

Managing urolithiasis requires robust strategies to prevent secondary stone episodes. Consequently, clinicians constantly seek effective modalities to curb urinary stone recurrence in ambulatory practice. Nephrolithiasis presents a substantial global healthcare burden with five-year recurrence rates approaching fifty percent. Traditionally, healthcare practitioners provided empirical lifestyle recommendations to every patient after stone passage. These standard measures included liberal hydration and general dietary moderations. However, routine empirical measures frequently fail in aggressive stone disease. Recent evidence highlights the clinical rationale for bespoke metabolic assessment. Through individualized screening, practitioners identify specific biochemical anomalies driving crystal supersaturation. Therefore, tailored treatment targets individual pathophysiology rather than offering generic advice. In addition, selective evaluation categorizes patients by recurrence risk profile. Low-risk formers often do well with conservative dietary counseling alone. In contrast, complex patients require deeper diagnostic scrutiny. Thus, identifying underlying metabolic derangements allows clinicians to initiate precise corrective therapies early. International guidelines consistently advocate for this stratified strategy to optimize clinical resources. Ultimately, personalized investigation aims to replace broad generalizations with actionable, patient-specific data. Furthermore, baseline stone analysis and serum chemistry profiles supply essential initial insights.
Comprehensive metabolic screening typically involves twenty-four-hour urine collections alongside corresponding serum biochemistries. Clinicians measure volume, calcium, oxalate, citrate, uric acid, sodium, and creatinine excretion. Moreover, analyzing urine supersaturation indices reveals specific crystallization tendencies. Bespoke metabolic investigation allows urologists to pinpoint exact physicochemical abnormalities. For instance, discovering severe hypocitraturia directs treatment toward urinary alkalinization rather than unnecessary dietary restrictions. Similarly, detecting unmasked primary hyperparathyroidism prompts surgical endocrine referral instead of prolonged medical surveillance. Research confirms that selective therapy guided by twenty-four-hour urine results significantly reduces stone-related events in high-risk cohorts. However, evidence remains limited regarding its superiority over empirical therapy in unselected, first-time stone formers. As a result, major urological bodies restrict comprehensive twenty-four-hour collections to recurrent or complicated cases. Pediatric stone formers, solitary kidney patients, and those with systemic comorbidities clearly warrant this bespoke diagnostic pathway. Furthermore, nephrolithiasis associated with nephrocalcinosis or gastrointestinal malabsorption requires meticulous metabolic tracking. Therefore, bespoke diagnostic protocols yield high clinical value when physicians apply them selectively to well-defined high-risk populations. Additionally, repeat collections help confirm baseline accuracy before establishing lifelong therapy. Consequently, targeted evaluation optimizes therapeutic choices.
Dietary interventions represent the foundational cornerstone of stone prevention across all risk tiers. Foremost, abundant fluid consumption directly lowers urinary solute concentration. Clinical trials demonstrate that increasing daily water intake to achieve over two liters of urine output halves recurrence rates. Specifically, high fluid intake reduces relative recurrence risk to between 0.45 and 0.55. In addition, dietary composition profoundly impacts urinary lithogenicity. Historical practices wrongly advised calcium restriction for hypercalciuric calcium-oxalate stone formers. However, modern evidence confirms that dietary calcium restriction paradoxically increases intestinal oxalate absorption and enhances stone formation. In contrast, maintaining normal calcium intake while restricting dietary sodium and animal protein achieves substantial protective benefit. This balanced dietary regimen reduces recurrence risk to approximately 0.49 in hypercalciuric individuals. Excessive dietary sodium promotes renal calcium excretion, which directly aggravates urinary calcium loads. Similarly, animal protein catabolism generates an acid load that reduces urinary citrate excretion and raises uric acid output. Therefore, limiting sodium intake and moderating animal flesh consumption preserves urinary inhibitors and dampens promoter activity. Ultimately, bespoke nutritional counseling provides sustained protection against crystal nucleation without compromising bone mineral density.
When dietary modifications prove insufficient, targeted pharmacotherapy addresses specific persistent metabolic abnormalities. For example, potassium citrate significantly alkalinizes urine and corrects hypocitraturia, slashing stone recurrence risk markedly to approximately 0.25. Likewise, allopurinol effectively lowers hyperuricosuria, reducing relative recurrence risk to roughly 0.59 among recurrent calcium oxalate formers. Thiazide diuretics have historically served as the primary medical intervention for idiopathic hypercalciuria. Systematic reviews previously demonstrated a favorable relative risk of 0.52 with thiazide therapy. However, the landmark double-blind NOSTONE randomized controlled trial challenged this conventional paradigm. Investigators evaluated hydrochlorothiazide at various doses against placebo in recurrent calcium stone formers. Surprisingly, hydrochlorothiazide demonstrated no significant superiority over placebo in preventing composite symptomatic or radiological stone recurrence. Furthermore, adverse metabolic events occurred more frequently in the thiazide arms, including hypokalemia and new-onset diabetes. In response, experts note that high dietary sodium intake in trial participants might have blunted the hypocalciuric effect of thiazides. Consequently, clinicians should not abandon thiazides entirely but must reserve them for patients with confirmed hypercalciuria who adhere strictly to sodium restriction. Thus, bespoke pharmacology requires thoughtful patient selection and regular monitoring.
Urological surgical interventions like shockwave lithotripsy and percutaneous nephrolithotomy achieve clearance but do not cure underlying metabolic lithogenesis. In fact, residual stone fragments frequently remain after intervention, creating niduses for rapid secondary encrustation. Fortunately, targeted medical therapy effectively reduces de novo stone formation and retards residual fragment regrowth. Therefore, completing metabolic evaluation following surgical stone removal protects technical investments and preserves renal function. Beyond clinical outcomes, recurrent nephrolithiasis severely diminishes disease-specific health-related quality of life. Patients endure unpredictable agonizing pain, frequent emergency admissions, missed workdays, and repeated surgical procedures. Moreover, nephrolithiasis imposes profound economic and environmental costs through hospitalizations, consumables, and operative theater utilization. Because preventative interventions substantially reduce acute hospital attendance and repeated surgeries, bespoke metabolic management proves highly cost-saving over time. Successful long-term prevention, however, requires sustained patient compliance. Clinicians must confirm therapeutic response and patient adherence through scheduled repeat twenty-four-hour urine collections. Ultimately, closing the loop with repeat testing ensures treatment effectiveness while minimizing financial waste. Additionally, empowering patients through structured education enhances concordance, optimizing clinical success across long-term follow-up care. Thus, structured prevention ensures lasting protection.
Bespoke metabolic evaluations provide the greatest clinical benefit in recurrent stone formers, pediatric patients, and individuals with solitary functioning kidneys. In addition, patients presenting with bilateral nephrolithiasis, systemic comorbidities like bowel disease, or substantial residual fragments after surgical clearance require comprehensive testing. In contrast, unselected first-time formers generally do well with basic screening and standard dietary advice alone. Therefore, reserving twenty-four-hour urine analysis for high-risk cohorts maximizes clinical efficacy and optimizes healthcare resource allocation.
The NOSTONE trial evaluated hydrochlorothiazide against placebo in recurrent calcium stone formers and found no statistically significant difference in clinical or radiological stone recurrence across three dosage arms. Furthermore, participants experienced increased metabolic adverse events like hypokalemia and hyperglycemia. However, trial participants consumed excessive dietary sodium, which physiologically counteracts the hypocalciuric effect of thiazides. Consequently, clinicians must ensure strict dietary sodium restriction and document persistent hypercalciuria before prescribing thiazide diuretics to stone formers.
Clinicians should schedule a repeat twenty-four-hour urine collection eight to twelve weeks after initiating dietary or medical modifications. This repeat investigation confirms whether targeted biochemical derangements have normalized and assesses patient adherence to hydration and dietary restrictions. Furthermore, ongoing annual or biennial urine testing helps identify metabolic escape or declining compliance over time. Therefore, systematic follow-up testing ensures pharmacological safety, sustains recurrence reduction, and allows clinicians to adjust treatment regimens according to dynamic metabolic responses.
Disclaimer: This content is for informational and educational purposes only... Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





A comprehensive review examines whether bespoke metabolic investigations and tailored therapies curb urinary stone recurrence. Evidence shows significant reductions in stone episodes and fragment regrowth among high-risk patients, whereas low-risk individuals benefit primarily from general preventative measures.
Today

A novel high-permeation vesicle-in-gel platform enhances transdermal fulvestrant delivery, achieving sustained release, robust intradermal retention, and superior antitumor efficacy in breast cancer models while circumventing the drawbacks of painful intramuscular depot injections.
Today

A landmark ten-year WHO report reveals how socioeconomic status, geography, and gender disparities profoundly aggravate chronic disease risks, diagnosis delays, and therapeutic outcomes globally. Discover actionable primary care strategies to bridge screening divides and optimize vulnerable patient management.
Today
A recent single-institution analysis identifies advanced patient age and progressive systemic disease as primary negative prognostic factors for five-year survival in chondrosarcoma, underscoring the urgent necessity of precise risk stratification, clear surgical margins, and dedicated oncologic follow-up.
Today
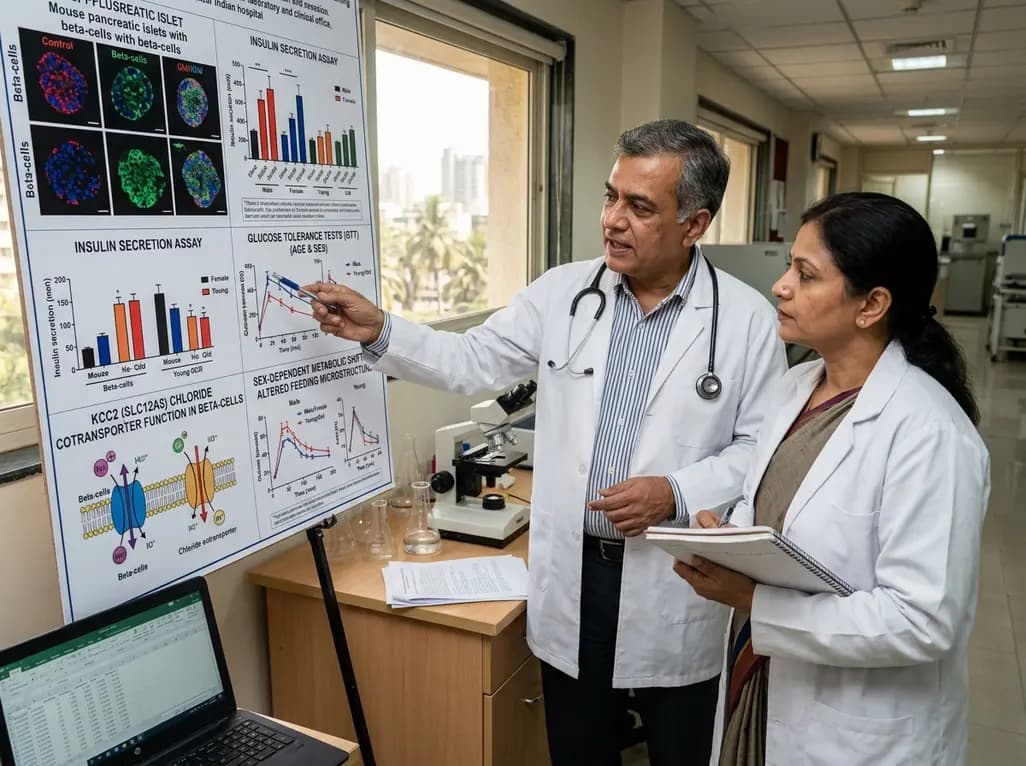
Targeted deletion of the chloride cotransporter Kcc2 (Slc12a5) in pancreatic beta-cells triggers distinct sex- and age-dependent metabolic shifts, including altered feeding microstructure, enhanced insulin release in young mice, and modified glucose tolerance, highlighting chloride's role in islet biology.
Today
