

Loading, please wait...
Loading, please wait...

Managing type 1 diabetes (T1D) has evolved with continuous glucose monitoring (CGM), yet clinicians frequently encounter GMI and HbA1c discordance. While the glucose management indicator (GMI) provides a snapshot of recent glycemic control based on mean glucose, the laboratory hemoglobin A1c (HbA1c) reflects longer-term glycation. Recent evidence suggests that these two markers often diverge significantly. A large-scale study now identifies specific glucose excursion patterns as the primary drivers of this discrepancy.
Researchers analyzed data from over 600 adults using the glucose rate increase detector (GRID) algorithm to quantify glycemic spikes. They found that high-amplitude excursions—defined as peaks reaching 250 mg/dL or higher—and prolonged excursions lasting at least 90 minutes were strongly associated with higher GMI values relative to measured HbA1c. Consequently, patients with frequent, long-lasting glucose spikes might show a GMI that appears much higher than their actual laboratory HbA1c result.
The study highlights that variability is not just about the average glucose but the shape and duration of the excursions. Furthermore, the association between prolonged excursions and discordance remained significant even after adjusting for age, sex, and kidney function. This finding suggests that rapid and sustained elevations in glucose levels may influence GMI calculations differently than they affect the biochemical process of hemoglobin glycation. Therefore, when a clinician notices a gap between these two metrics, they should look specifically at the frequency of high-peak excursions on the patient's CGM report.
Additionally, the research indicates that traditional variability metrics, like the coefficient of variation (CV), may not fully capture the nuances of these excursions. Because GMI relies on mean sensor glucose, it may be more sensitive to transient but severe hyperglycemia than the glycation process that forms HbA1c. Thus, identifying these patterns helps healthcare providers offer more personalized counseling and treatment adjustments.
Recognizing the reasons for GMI and HbA1c discordance is crucial for avoiding unnecessary treatment intensification. If a high GMI is driven by a few prolonged excursions rather than overall poor control, the clinical approach may differ. For instance, focusing on postprandial bolus timing or insulin-to-carb ratios might be more effective than simply increasing the basal dose. Moreover, understanding these patterns helps set more realistic expectations for patients who feel frustrated by the "mismatch" in their numbers.
This discordance often occurs because GMI is highly sensitive to high-amplitude glucose excursions. If you experience frequent glucose peaks above 250 mg/dL that last more than 90 minutes, your GMI may appear significantly higher than your HbA1c, which measures glycation over a longer period.
Clinicians should evaluate the CGM traces for specific patterns of hyperglycemia using metrics like Time Above Range (TAR). If prolonged excursions are present, focusing therapy on reducing these specific spikes may help align the metrics and improve overall glycemic stability.
Disclaimer: This content is for informational and educational purposes only and does not constitute medical advice. Always seek the advice of a physician or other qualified health provider with any questions regarding a medical condition. Refer to the latest local and national guidelines for clinical practice.
References
Park S et al. High-Amplitude and Prolonged Glucose Excursions as a Key Determinant of Discordance Between Glucose Management Indicator and Glycated Hemoglobin in Type 1 Diabetes. Diabetes Care. 2026 May 04. doi: undefined. PMID: 42081254.
Gomez-Peralta F et al. Understanding the clinical implications of differences between glucose management indicator and glycated haemoglobin. Diabetes Obes Metab. 2022;24(4):599-608. doi: 10.1111/dom.14634.
Bergenstal RM et al. Glucose Management Indicator (GMI): A New Term for Estimating A1C From Continuous Glucose Monitoring. Diabetes Care. 2018;41(11):2275-2280. doi: 10.2337/dc18-1581.

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





New research shows that high-amplitude, prolonged glucose excursions are key factors causing discrepancies between GMI and HbA1c in type 1 diabetes patients...
5 months ago

Review how tailored exercise programs benefit frail older patients with heart failure. Explore pathophysiological mechanisms, individualized training prescriptions, and strategies to overcome adherence barriers in clinical practice.
Today

Leucine Rich Bio has introduced South Asia's first comprehensive vaginal microbiome test, BugSpeaks. By profiling microbial dysbiosis, pathogens, and antimicrobial resistance, this next-generation diagnostic platform provides clinicians with deeper insights into recurrent infections, fertility, and reproductive health.
Today
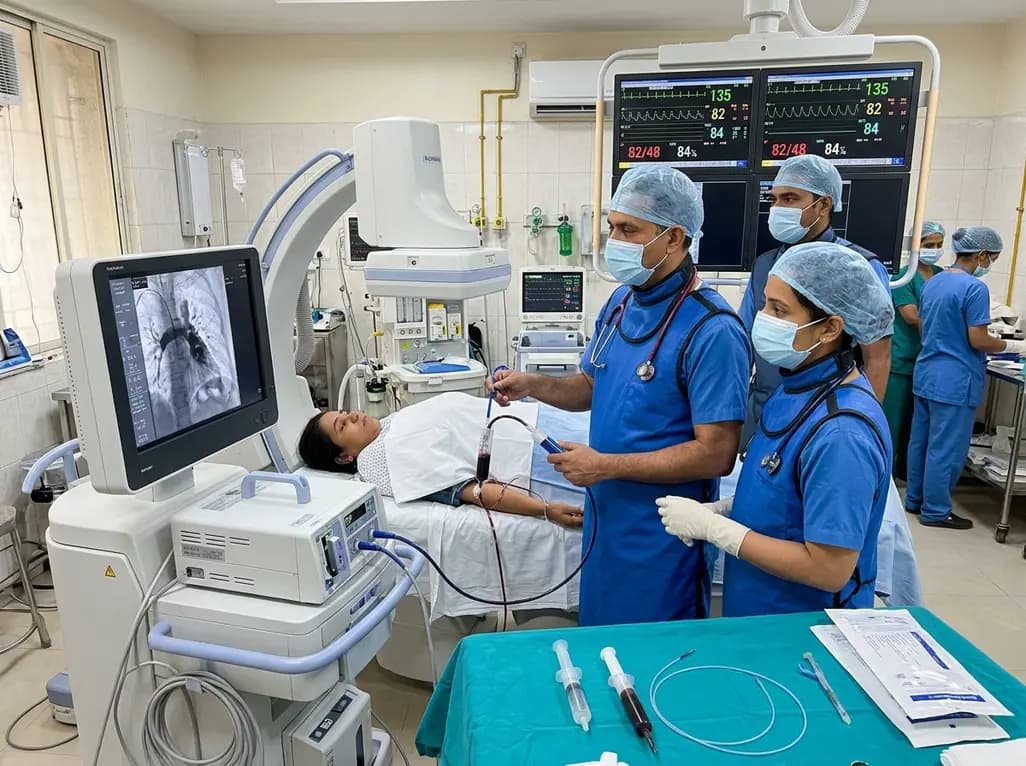
In high-risk pulmonary embolism complicated by severe anemia and active uterine bleeding, systemic thrombolysis is contraindicated. Large-bore aspiration thrombectomy provides rapid hemodynamic rescue without fibrinolysis, supported by inferior vena cava filter placement and multidisciplinary critical care.
Today
This comparative study evaluates posterior labral tears with and without glenohumeral instability, highlighting distinct demographic patterns, MRI underestimation in stable shoulders, and successful arthroscopic repair outcomes.
Today

A clinical study demonstrates that early intervention with tocilizumab, either as monotherapy or bridged with corticosteroids, achieves significant proptosis reduction and resolves active inflammation in treatment-naive thyroid eye disease.
Today
