

Loading, please wait...
Loading, please wait...

Quantitative neuromuscular assessment serves as a cornerstone for tracking functional recovery in neurological conditions. Clinicians and neuroscientists frequently utilize electromyography data to understand how the central nervous system coordinates complex movements. In modern neurorehabilitation research, motor module analysis provides critical insights into muscle synergies, isolating modular coordination primitives from multi-channel recordings. However, conventional computational approaches often present mathematical fragility that complicates longitudinal clinical interpretation. Recent advances now demonstrate that single-layer artificial neural networks can resolve these historical limitations, providing reproducible and physiologically meaningful representations of impaired motor control.
Human locomotion and upper-extremity reaching demand precise coordination among dozens of skeletal muscles. Consequently, the central nervous system simplifies this redundant control problem by activating groups of co-contracting muscles, commonly termed motor modules or muscle synergies. Rather than regulating each muscle independently, descending neural drives recruit fixed weightings of synergistic muscle sets. Following central nervous system insults such as cerebrovascular accidents, these modular structures undergo profound alterations. Stroke survivors often exhibit abnormal modular merging, where discrete synergies coalesce into clumsy, stereotypical mass patterns that impair functional independence. Therefore, tracking synergy preservation or fragmentation allows clinicians to evaluate corticospinal integrity objectively. Quantitative motor profiling separates true neurological recovery from secondary behavioral compensation. Because therapeutic neuroplasticity alters muscle activation timing and structural recruitment, clinicians need robust computational tools to decode electromyographic changes reliably during rehabilitation regimens.
For decades, non-negative matrix factorization served as the default mathematical framework for decomposing surface electromyographic signals into spatial modules and temporal coefficients. Despite its widespread adoption, non-negative matrix factorization harbors substantial methodological constraints that hinder clinical translation. Most notably, the mathematical output displays acute sensitivity to the predetermined number of modules selected by the researcher. When an investigator alters the target module count, the spatial weightings of previously extracted modules frequently shift or split arbitrarily. Furthermore, scientific consensus regarding the optimal stopping criteria remains elusive, as different laboratories apply conflicting statistical thresholds. This variability makes direct comparison between published cohorts exceedingly difficult. In addition, metrics such as the variance accounted for by extracting a single module offer limited biomechanical interpretability, obscuring genuine physiological insight behind abstract statistical constructs.
To overcome these structural vulnerabilities, researchers developed an innovative machine learning framework utilizing a single-layer autoencoder. This neural network architecture effectively learns compact latent representations by reconstructing high-dimensional electromyographic inputs across hidden bottlenecks. Unlike conventional factorization, autoencoder-driven motor module analysis demonstrates superior structural stability across varying module counts. When investigators instruct the network to extract additional latent dimensions, the algorithm naturally preserves existing modular architectures. Instead of splitting established muscle synergies into uninterpretable fragments, the autoencoder appends distinct, complementary layers of physiological information. Furthermore, this machine learning framework reliably handles biological noise inherent to surface electromyography. As a result, the extracted synergy patterns maintain robust mathematical fidelity, providing translational researchers and clinical teams with a stable foundation for longitudinal neuromuscular monitoring.
A primary clinical critique of advanced computational modeling involves the frequent lack of direct functional relevance. Fortunately, autoencoder-computed modules demonstrate immediate, transparent biomechanical interpretability, especially at low dimensional counts. In recent experimental evaluations spanning able-bodied controls and stroke survivors, autoencoder representations mapped cleanly to defined joint moments and propulsion phases. In contrast to standard factorization methods, the autoencoder isolates fundamental functional primitives, such as limb loading, propulsion, and swing initiation, without creating mathematically artificial hybrid synergies. Moreover, the autoencoder redefines the clinical interpretation of single-module variance metrics. Rather than reflecting mathematical noise or widespread global co-contraction, a single extracted autoencoder module isolates the primary mechanical axis of movement. Consequently, clinicians can track whether therapeutic interventions systematically normalize abnormal joint torque coupling or reduce pathological extensor synergy patterns.
In post-stroke cohorts, the autoencoder pipeline successfully corroborates established neurobiological principles while eliminating algorithmic artifacts. Clinicians have long observed that paretic limbs require fewer motor modules to describe overall muscle activity, reflecting impaired motor cortical output and reduced modular complexity. Autoencoder models reproduce this characteristic reduction with superior mathematical consistency across mild, moderate, and severe hemiparesis. Additionally, because the extracted modules remain stable regardless of dimension choices, physical therapists and rehabilitation teams can confidently interpret subtle electromyographic shifts over serial evaluations. Clinicians can determine whether a patient is regaining modular independence or merely adjusting compensatory trunk movements. By bridging modern machine learning with applied neurophysiology, this computational methodology supports personalized motor therapy, targeted robotic gait training, and precise neuromuscular monitoring throughout the subacute and chronic recovery phases.
While non-negative matrix factorization decomposes electromyography data through linear matrix approximation, an autoencoder uses an artificial neural network with a bottleneck latent layer. Consequently, the autoencoder preserves existing synergy weightings when adding modules. This architecture prevents arbitrary module splitting and yields superior structural stability compared to non-negative matrix factorization.
A higher variance accounted for by a single module typically indicates reduced motor complexity. Following a stroke, damaged descending pathways often force diverse muscle groups into unified mass flexor or extensor synergies. Thus, a single dominant module explains a disproportionately high percentage of total muscle activity across movements.
Yes, rehabilitation facilities can readily integrate autoencoder algorithms into existing surface electromyography workflows. Because the methodology does not require extensive computational clusters, clinics can analyze walking or reaching trials rapidly. This timely feedback enables physical therapists to adjust robotic assistance, functional electrical stimulation, or motor tasks dynamically.
Disclaimer: This content is for informational and educational purposes only. It is not intended to provide medical advice, diagnosis, or treatment. Always seek the advice of your physician or other qualified health provider with any questions you may have regarding a medical condition. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





Explore how single-layer autoencoders overcome traditional NMF limitations in motor module analysis. This novel computational framework enhances structural stability, biomechanical interpretability, and post-stroke neuromuscular assessment for targeted rehabilitation.
last month

The ASAS core set defines mandatory domains and instruments for axial spondyloarthritis across routine and extended clinic visits, optimizing outpatient care and aligning treatment monitoring with international guidelines.
Today

A Belgian study highlights maternal desires and healthcare provider perspectives on breastfeeding in women living with HIV. While viral suppression reduces transmission risk below 1%, significant clinical training and policy gaps remain, highlighting the urgent need for multidisciplinary counseling protocols.
Today
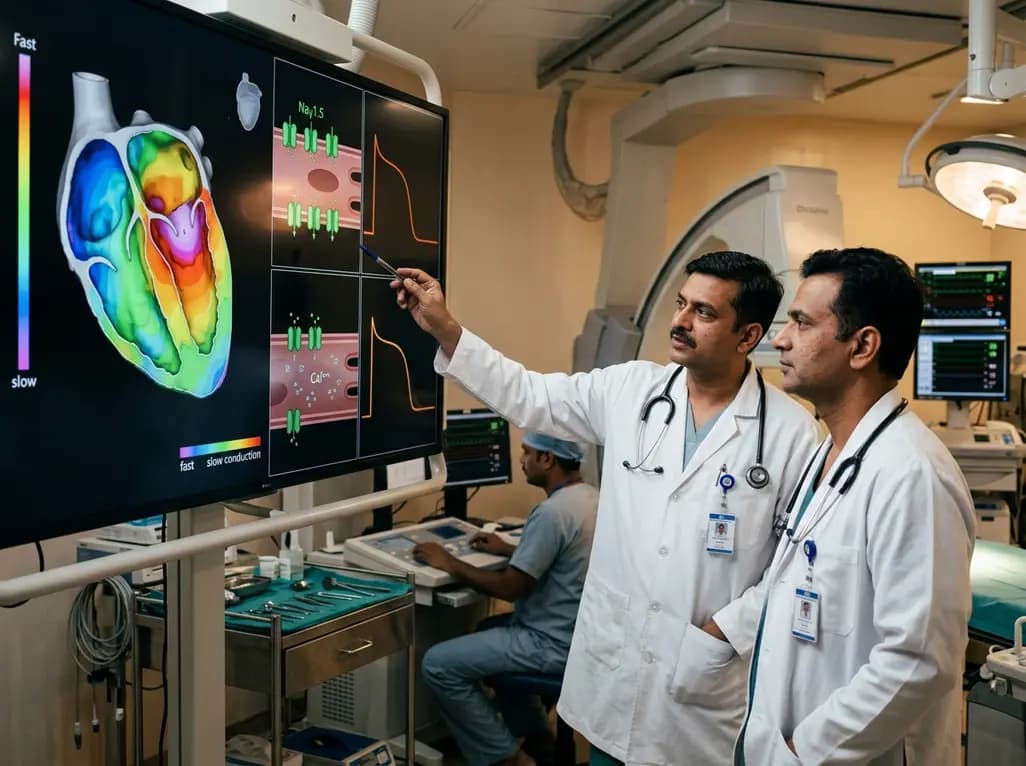
New research reveals that non-ablative radiotherapy suppresses ventricular tachycardia by increasing conduction velocity via NaV1.5 upregulation and action potential prolongation. However, sustained sodium current elevation and depressed calcium handling highlight the need for careful clinical translation.
Today

Diagnostic data shows that nearly one in four spine investigations now involve patients younger than 40 years. This comprehensive overview explores the drivers behind this demographic trend, evaluates ergonomic hazards, clarifies red-flag signs, and highlights clinical indications for judicious diagnostic imaging.
Yesterday

A landmark randomized clinical trial demonstrates that real-time continuous glucose monitoring significantly reduces HbA1c and enhances time in range for individuals with type 2 diabetes who do not take insulin, paving the way for broader clinical adoption and personalized metabolic therapy in primary care.
Today
