

Loading, please wait...
Loading, please wait...
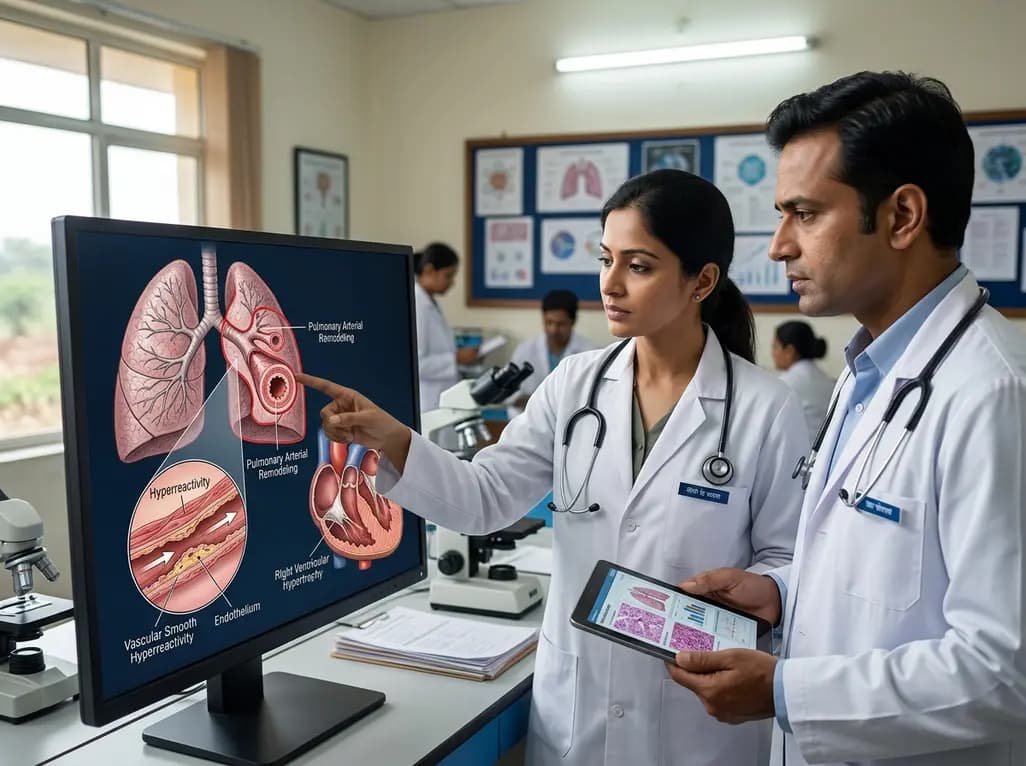
Chronic allergic airway disease frequently extends beyond the bronchial tree to compromise the adjacent pulmonary circulation. Clinicians increasingly recognize that persistent asthma can precipitate secondary pulmonary vascular dysfunction, yet the underlying functional and structural alterations remain poorly characterized. During chronic inflammation, sustained exposure to airborne allergens provokes substantial immune cell recruitment, cytokine cascades, and airway remodeling. Consequently, these inflammatory mediators cross the alveolar-capillary barrier and initiate vascular remodeling. In addition, repetitive mechanical strain from elevated airway pressures alters local hemodynamics. Therefore, chronic airway disorders can gradually shift from localized bronchial inflammation to pervasive pulmonary vascular pathology. Identifying these microvascular changes early provides vital diagnostic value for preventing irreversible cardiopulmonary deterioration.
To examine the vascular consequences of persistent allergic disease, researchers developed a four-week chronic mixed-allergen (MA) murine model. Wild-type mice received intranasal challenges with either the mixed allergen cocktail or phosphate-buffered saline controls. Subsequently, investigators utilized the flexiVent platform to evaluate respiratory mechanics with precise physiological measurements. Chronic allergen exposure provoked pronounced airway hyperresponsiveness across the challenged cohorts. Specifically, the challenged mice exhibited marked increases in total respiratory system resistance (Rrs) and elastance (Ers). Conversely, respiratory system compliance (Crs) showed significant reduction compared to control animals. These comprehensive physiological findings confirmed robust, established allergic asthma in the animal model. Furthermore, this stable model enabled investigators to conduct direct structural and functional profiling of the pulmonary vasculature.
Beyond airway hyperreactivity, histological examinations revealed striking architectural alterations within the pulmonary arterial network. Chronic allergen challenge induced marked pulmonary artery medial wall thickening along with extensive smooth muscle hyperplasia. Under homeostatic conditions, distal pulmonary arterioles possess delicate, thin muscular walls that maintain low resistance to flow. However, chronic inflammatory signaling stimulates vascular smooth muscle proliferation and extracellular matrix deposition. Therefore, the medial layer undergoes muscularization, narrowing the vessel lumen and increasing pulmonary vascular resistance. In addition, persistent cellular stress promotes phenotypic switching of vascular smooth muscle cells into a proliferative state. Thus, chronic mixed-allergen exposure structurally reprograms the pulmonary vascular bed, creating persistent anatomical changes that mirror chronic human pulmonary vascular disorders.
To characterize vessel reactivity, researchers conducted wire myography on isolated pulmonary arterial rings. The functional assays demonstrated pronounced vasoconstrictive hyperreactivity to serotonin (5-HT) in allergen-exposed mice compared to controls. Furthermore, myography experiments uncovered severe endothelial impairment within the remodeled pulmonary vasculature. Challenged arterial rings exhibited blunted endothelium-dependent relaxation during acetylcholine (ACh) administration. Conversely, endothelium-independent relaxation remained fully preserved in response to the nitric oxide donor sodium nitroprusside (SNP). This preservation confirms that intrinsic smooth muscle sensitivity to nitric oxide remained intact. Consequently, the observed impairment stems directly from damaged endothelial signaling pathways and impaired endogenous nitric oxide bioavailability. Therefore, chronic allergic inflammation simultaneously impairs vasodilation and amplifies vasoconstrictive responses.
The structural remodeling and elevated vascular tone culminated in measurable hemodynamic consequences for the right heart. Investigators assessed right ventricular hypertrophy using the Fulton index, calculated as the ratio of right ventricular weight to left ventricle plus septum weight. Challenged mice demonstrated significant right ventricular hypertrophy, reflecting increased afterload from pulmonary arterial resistance. In clinical practice, secondary pulmonary vascular dysfunction and cor pulmonale represent underappreciated complications in patients suffering from severe, uncontrolled asthma. Chronic hypoxemia and persistent inflammatory signaling gradually elevate pulmonary arterial pressure. Therefore, pulmonologists and cardiologists must maintain high vigilance for subclinical right heart strain in patients with severe airway disease. Integrating early echocardiographic surveillance may improve therapeutic management and patient outcomes.
Chronic allergen exposure stimulates persistent inflammatory cell infiltration and cytokine release across the lung parenchyma. These biochemical signals traverse the vascular adventitia and activate local smooth muscle cells and fibroblasts. Consequently, pulmonary vascular smooth muscle cells undergo rapid hyperplasia and matrix deposition. This proliferative response thickens the medial arterial wall, progressively narrows vessel diameter, and increases pulmonary vascular resistance over time.
Endothelial dysfunction denotes the functional loss of normal endothelial vasodilatory signaling, demonstrated by impaired vessel relaxation to acetylcholine despite preserved responsiveness to sodium nitroprusside. In contrast, smooth muscle hyperplasia represents a structural alteration characterized by cellular proliferation and thickening of the arterial tunica media. Both pathological processes combine to restrict blood flow and elevate pulmonary arterial pressure.
Right ventricular hypertrophy indicates sustained hemodynamic overload driven by increased pulmonary vascular resistance. When chronic allergic inflammation stiffens pulmonary arteries, the right ventricle must generate higher pressures to maintain adequate lung perfusion. Consequently, progressive ventricular remodeling occurs, potentially predisposing vulnerable asthma patients to right-sided heart failure and adverse long-term cardiovascular outcomes if left unmanaged.
Disclaimer: This content is for informational and educational purposes only and is not intended to serve as medical advice, diagnosis, or treatment. Healthcare professionals must exercise independent clinical judgment. Refer to the latest local and national guidelines for clinical practice.
References

Read summarized clinical updates, watch expert medical content, and earn CME certifications right from your smartphone.
Open your smartphone camera to scan and install.





New experimental evidence shows that chronic mixed-allergen exposure triggers severe pulmonary arterial remodeling, endothelial dysfunction, smooth muscle hyperreactivity, and right ventricular hypertrophy, uncovering key cardiopulmonary links in chronic asthma.
last month

The ASAS core set defines mandatory domains and instruments for axial spondyloarthritis across routine and extended clinic visits, optimizing outpatient care and aligning treatment monitoring with international guidelines.
Today

A Belgian study highlights maternal desires and healthcare provider perspectives on breastfeeding in women living with HIV. While viral suppression reduces transmission risk below 1%, significant clinical training and policy gaps remain, highlighting the urgent need for multidisciplinary counseling protocols.
Today
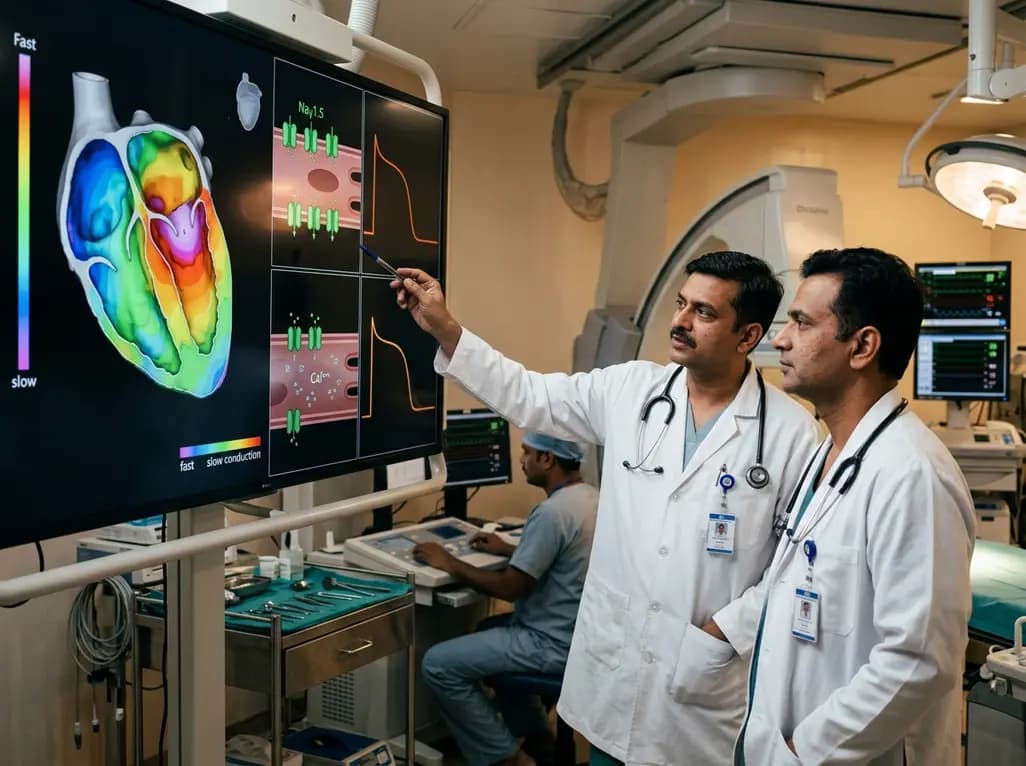
New research reveals that non-ablative radiotherapy suppresses ventricular tachycardia by increasing conduction velocity via NaV1.5 upregulation and action potential prolongation. However, sustained sodium current elevation and depressed calcium handling highlight the need for careful clinical translation.
Today

Diagnostic data shows that nearly one in four spine investigations now involve patients younger than 40 years. This comprehensive overview explores the drivers behind this demographic trend, evaluates ergonomic hazards, clarifies red-flag signs, and highlights clinical indications for judicious diagnostic imaging.
Yesterday

A landmark randomized clinical trial demonstrates that real-time continuous glucose monitoring significantly reduces HbA1c and enhances time in range for individuals with type 2 diabetes who do not take insulin, paving the way for broader clinical adoption and personalized metabolic therapy in primary care.
Today
